Total knee replacement (TKA): an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Total knee replacement in one minute
What it is: surgery to replace the worn surfaces of the knee joint with metal and plastic parts.
Who it is for: people with severe knee arthritis causing pain and stiffness despite other treatments.
Main risks: infection, blood clots, stiffness, ongoing pain, loosening or wear over time.
Usually: under spinal or general anaesthetic, 1–2 hours, home in 1–3 days.
On this page: What is a total knee replacement? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
What is a total knee replacement?
In a healthy knee, smooth cartilage covers the ends of the thigh bone (femur) and shin bone (tibia). In arthritis this wears away, causing pain and stiffness.
In a total knee replacement (TKA, also called TKR) the surgeon:
- removes the damaged surfaces with precise cutting guides and a saw
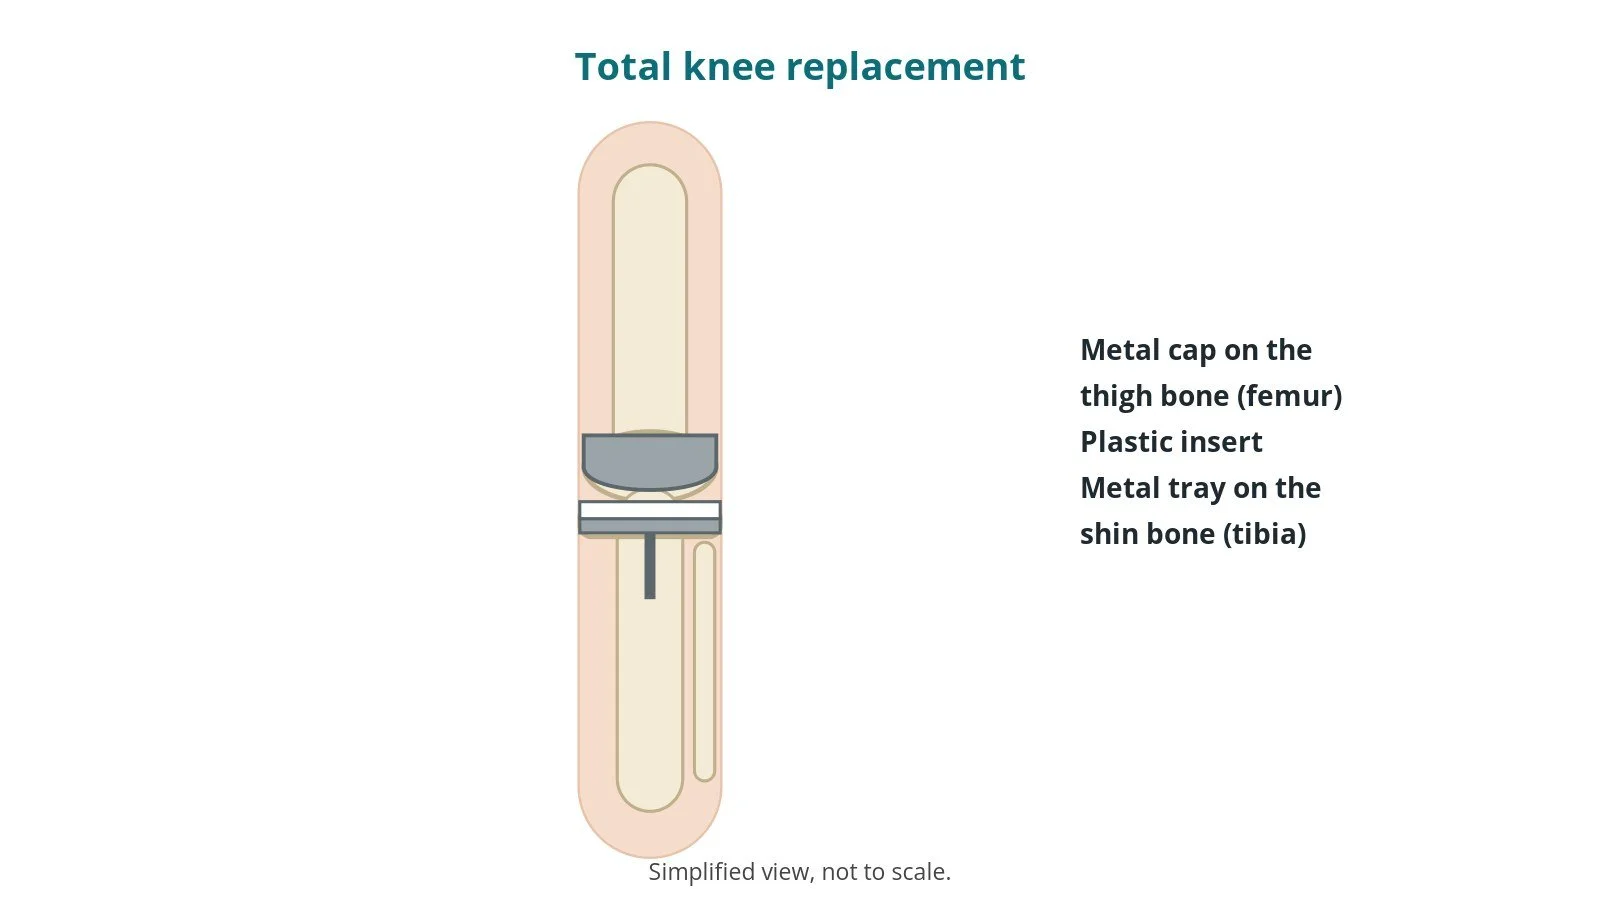
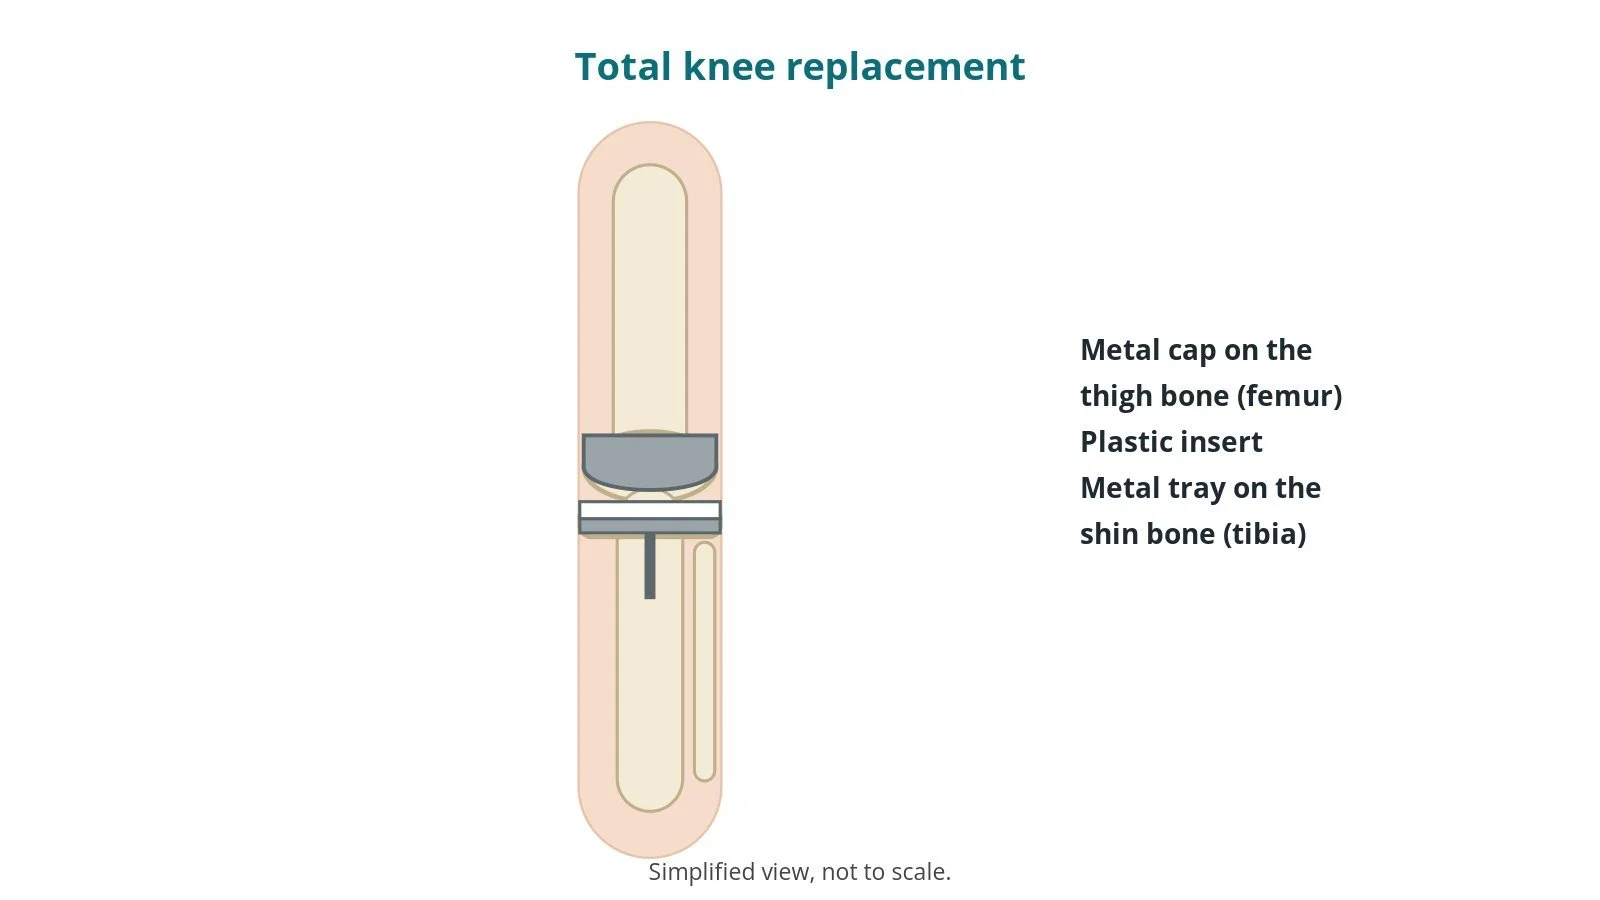
- fits a metal cap on the femur and a metal tray on the tibia, with a plastic insert between them
- sometimes resurfaces the back of the kneecap, per surgeon
Implants are fixed with bone cement or press-fit, per device and operator. A partial (unicompartmental) replacement is an option for some people.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- severe knee arthritis (osteoarthritis or inflammatory arthritis)
- pain affecting sleep, walking and daily life despite medicines, physiotherapy and weight management
- knee deformity from arthritis
The decision is made by your surgical team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
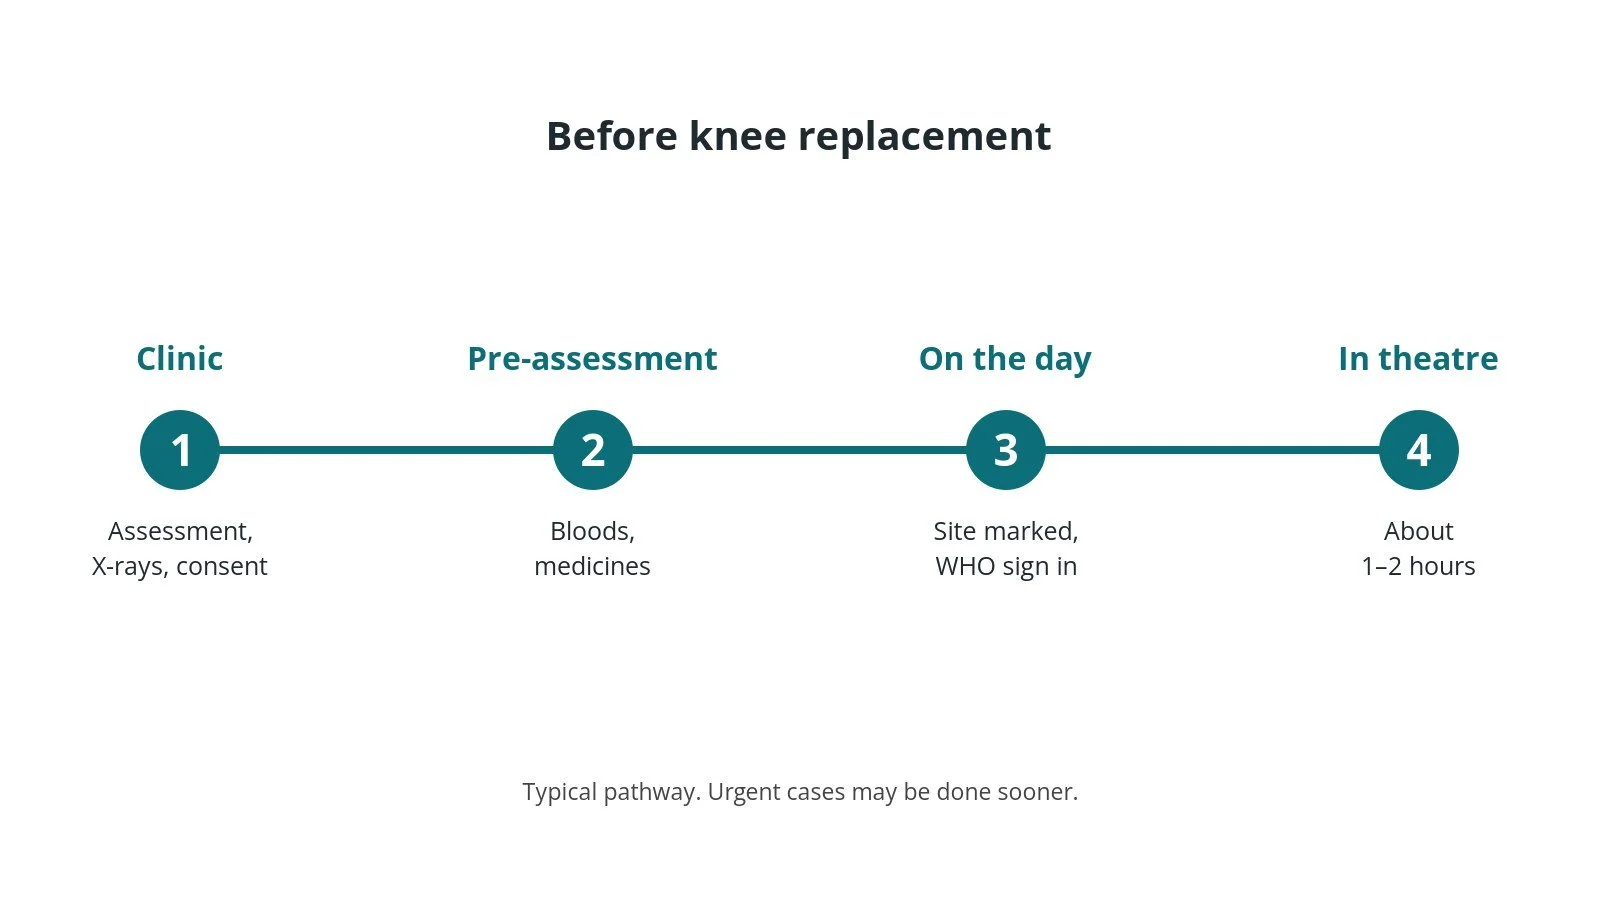
Most operations are planned; some are urgent. Before it, you usually have:
- an examination and X-rays, and sometimes a CT or MRI scan
- blood tests and, for bigger operations, an ECG
- a review of your medicines, especially blood thinners, as per centre protocol
- fasting instructions
- a chance to ask questions and give consent
Step by step
1. Getting ready
Team brief and WHO checklist first, including the implant check and confirming the site and side marking. The anaesthetic team and ODP give the anaesthetic (usually spinal with sedation, or general, often with a nerve block, as per centre protocol); antibiotics and blood-clot prevention are given as per centre protocol. The circulating practitioner checks positioning and pressure areas, the diathermy plate, warming, the tourniquet, and radiation protection if X-ray is used. The scrub practitioner checks implant and instrument trays are complete and sterile, and does the first count. Theatre traffic is kept to a minimum, especially in laminar-flow theatres.
2. Access
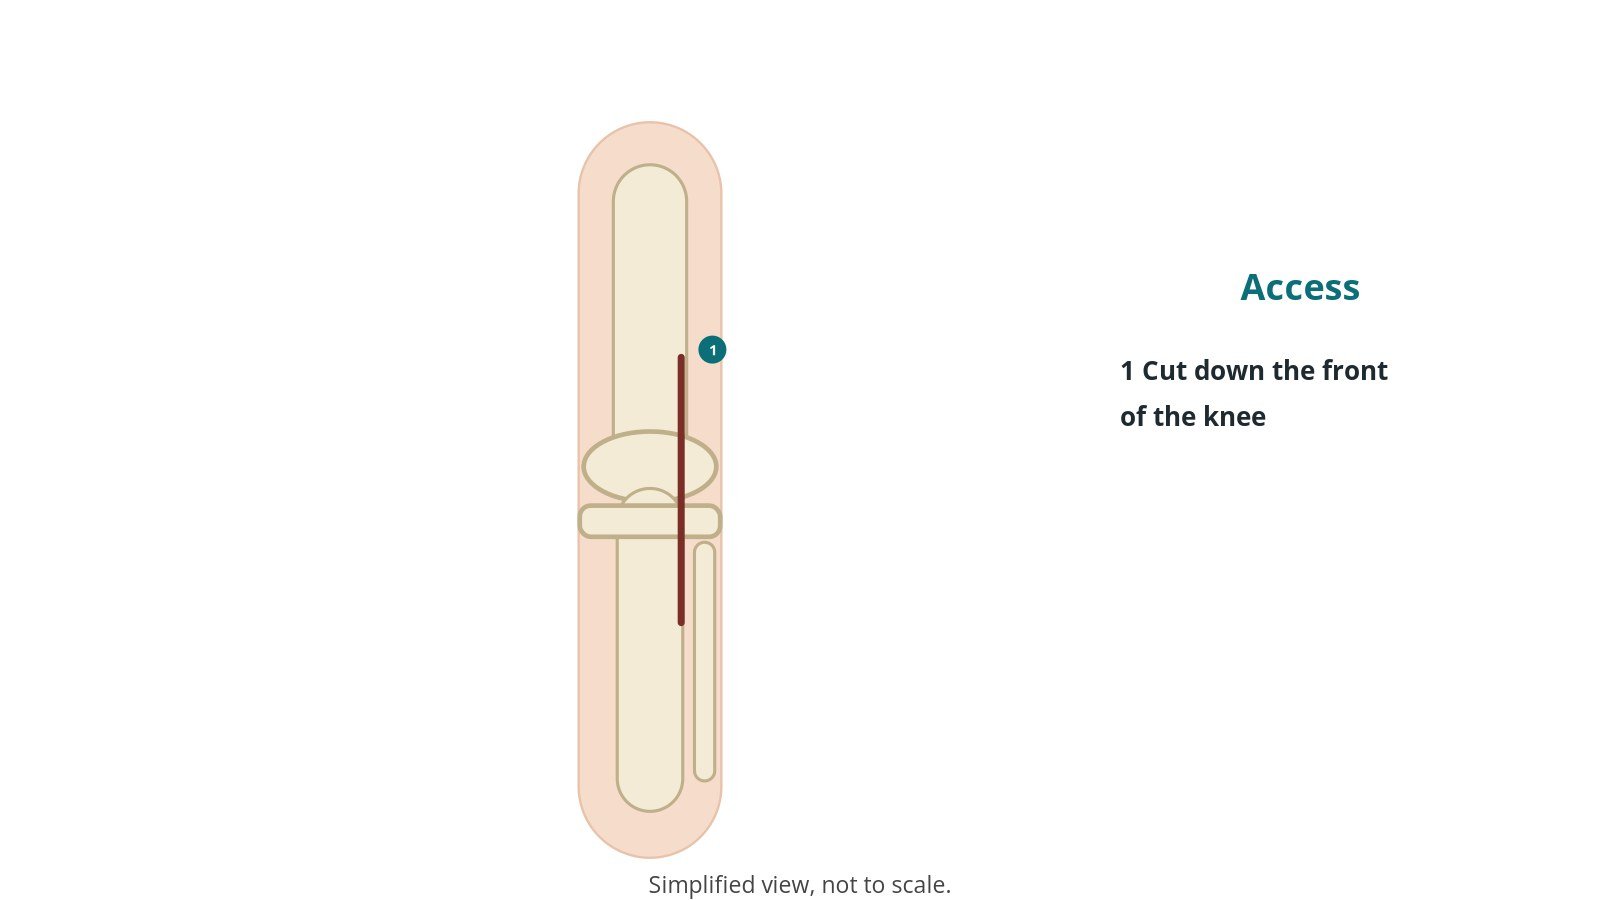
The patient lies on their back with a tourniquet on the thigh, per surgeon. A cut is made down the front of the knee and the joint is opened beside the kneecap.
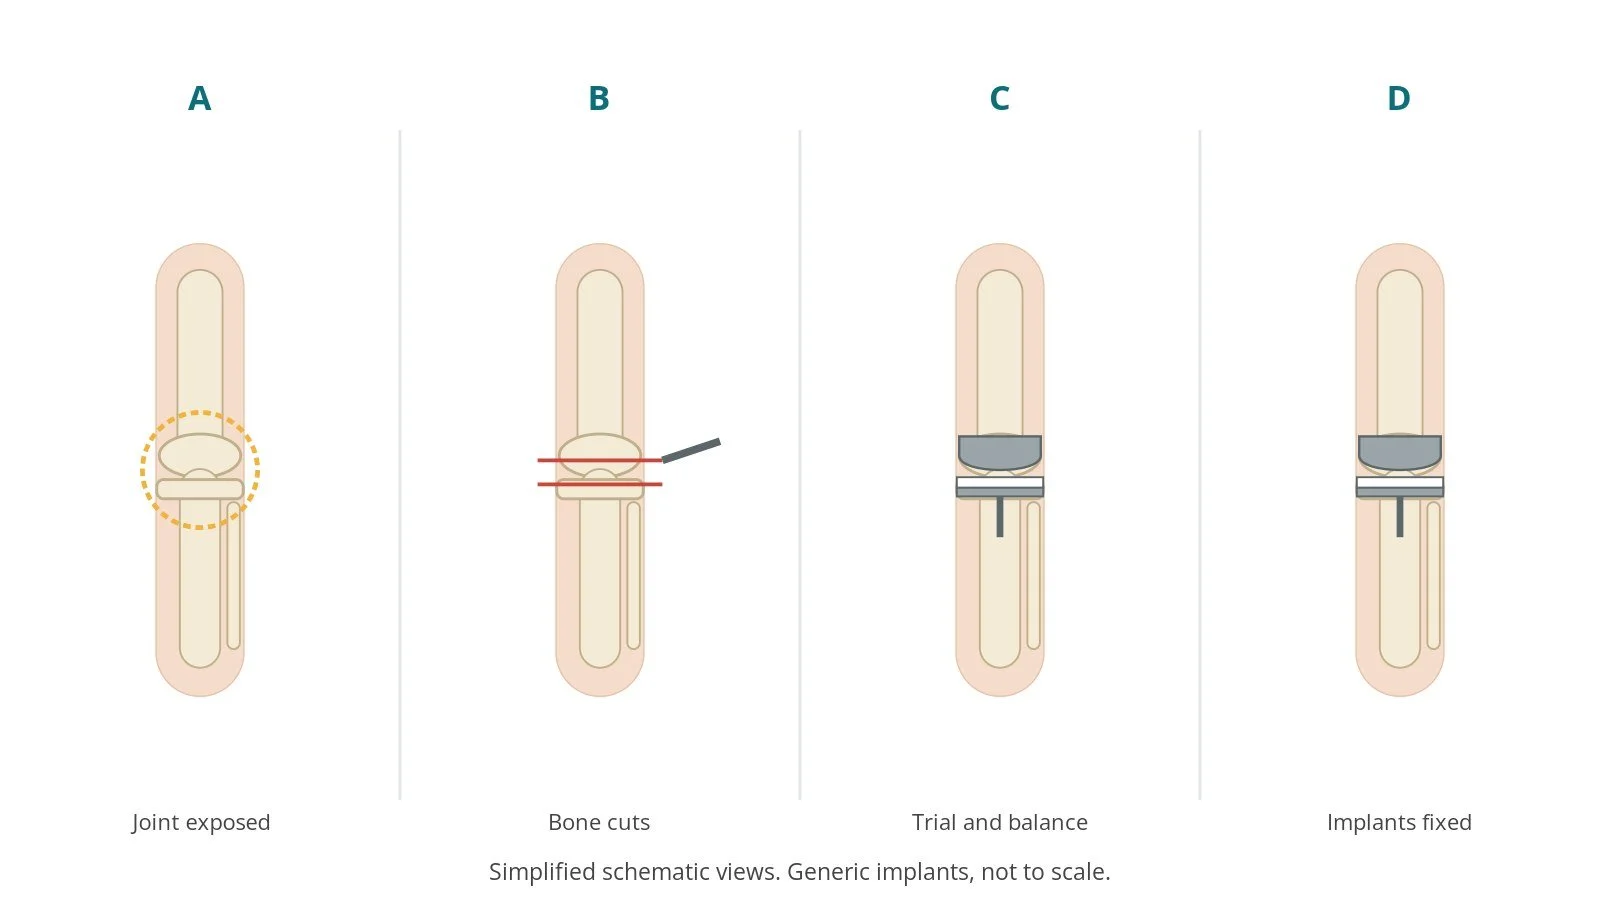
3. Replacing the knee
- A. Joint exposed. The knee is opened and the kneecap moved aside.
- B. Bone cuts. Guides are fixed and the worn ends of the femur and tibia are cut with a saw.
- C. Trial and balance. Trial parts are fitted and the knee is tested for movement and stability.
- D. Implants fixed. The final parts are cemented or press-fitted, size per device and operator, and the plastic insert placed.
Before the final implants are opened, the team reads back the side, type and sizes.
4. Finishing
The joint is washed and closed in layers; local anaesthetic may be injected around the knee. A dressing and sometimes a compression bandage are applied. Final counts are confirmed, implant details recorded, and the patient goes to recovery with a full handover, including limb checks (circulation and nerves), as per centre protocol.
Recovery and aftercare
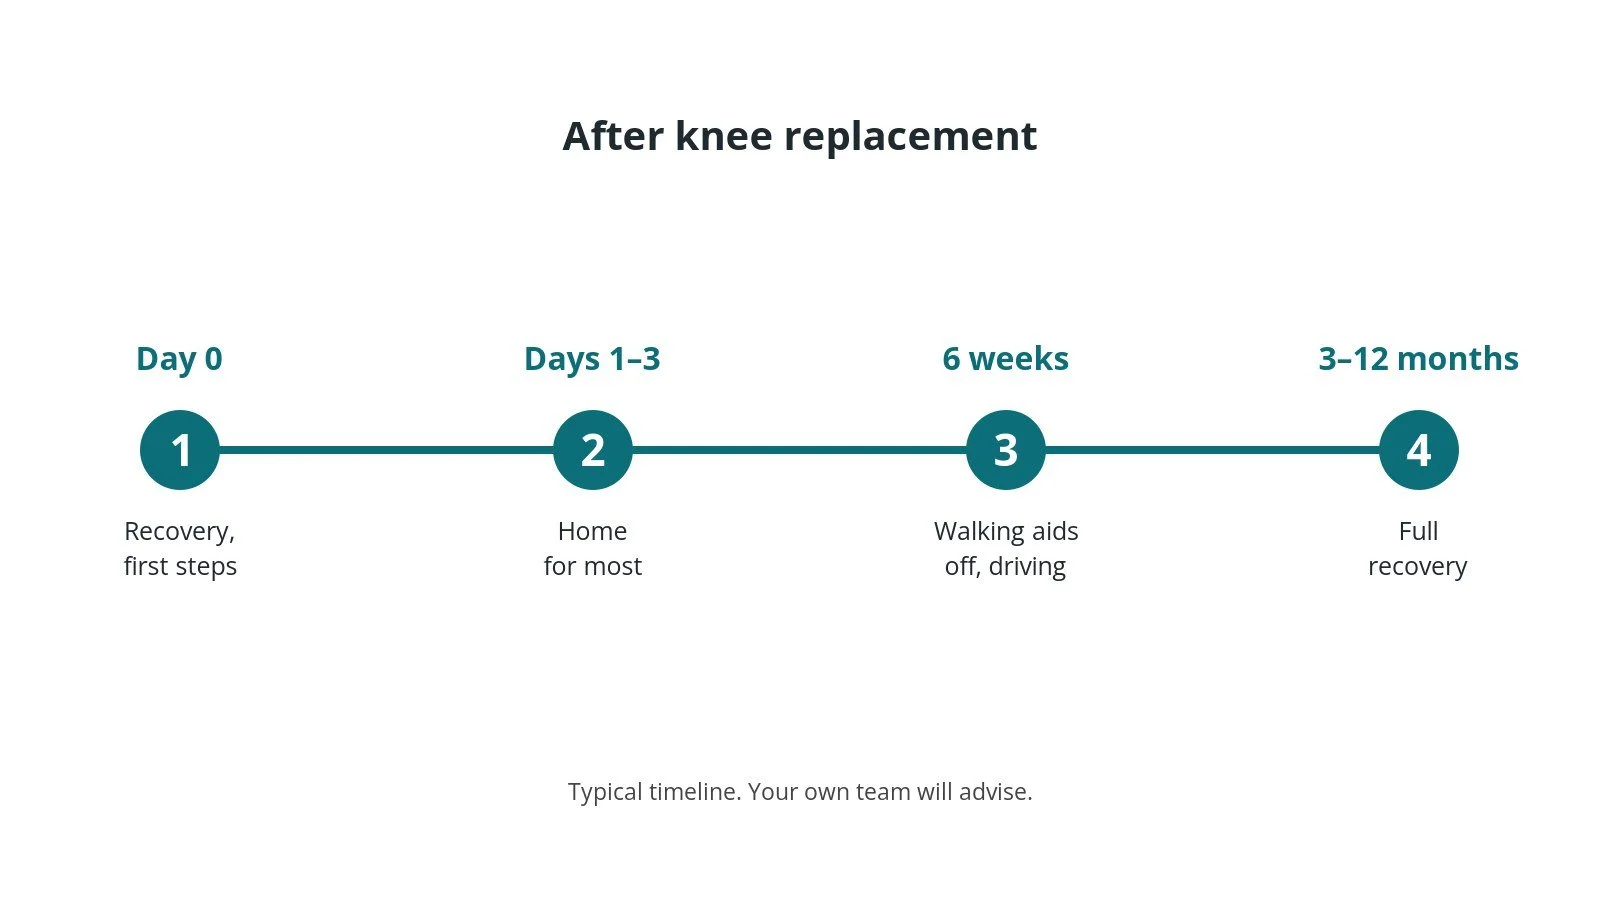
- First hours: in recovery, then a ward; pain relief, anti-sickness medicine and limb checks.
- Getting up: physiotherapists help you walk, often on the day of surgery or the next day (enhanced recovery).
- Going home: often 1–3 days after surgery.
- Exercises: do your physiotherapy exercises every day; they matter as much as the operation.
- Clot prevention: injections, tablets or stockings, as per centre protocol.
- Walking aids: crutches or a frame for a few weeks.
- Driving: usually not for about 6 weeks; ask your team.
- Follow-up: wound check and clinic review, as per centre protocol.
Call 999 if you have chest pain or sudden breathlessness. Contact your team if you have increasing pain, a cold, numb or very swollen limb, calf pain, fever, or a wound that becomes red, hot or leaky.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- wound infection, or deep infection of the joint (uncommon but serious)
- blood clots in the legs or lungs
- stiffness or ongoing pain
- bleeding or wound problems
- nerve or blood vessel injury (rare)
- loosening or wear needing further surgery in the future
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
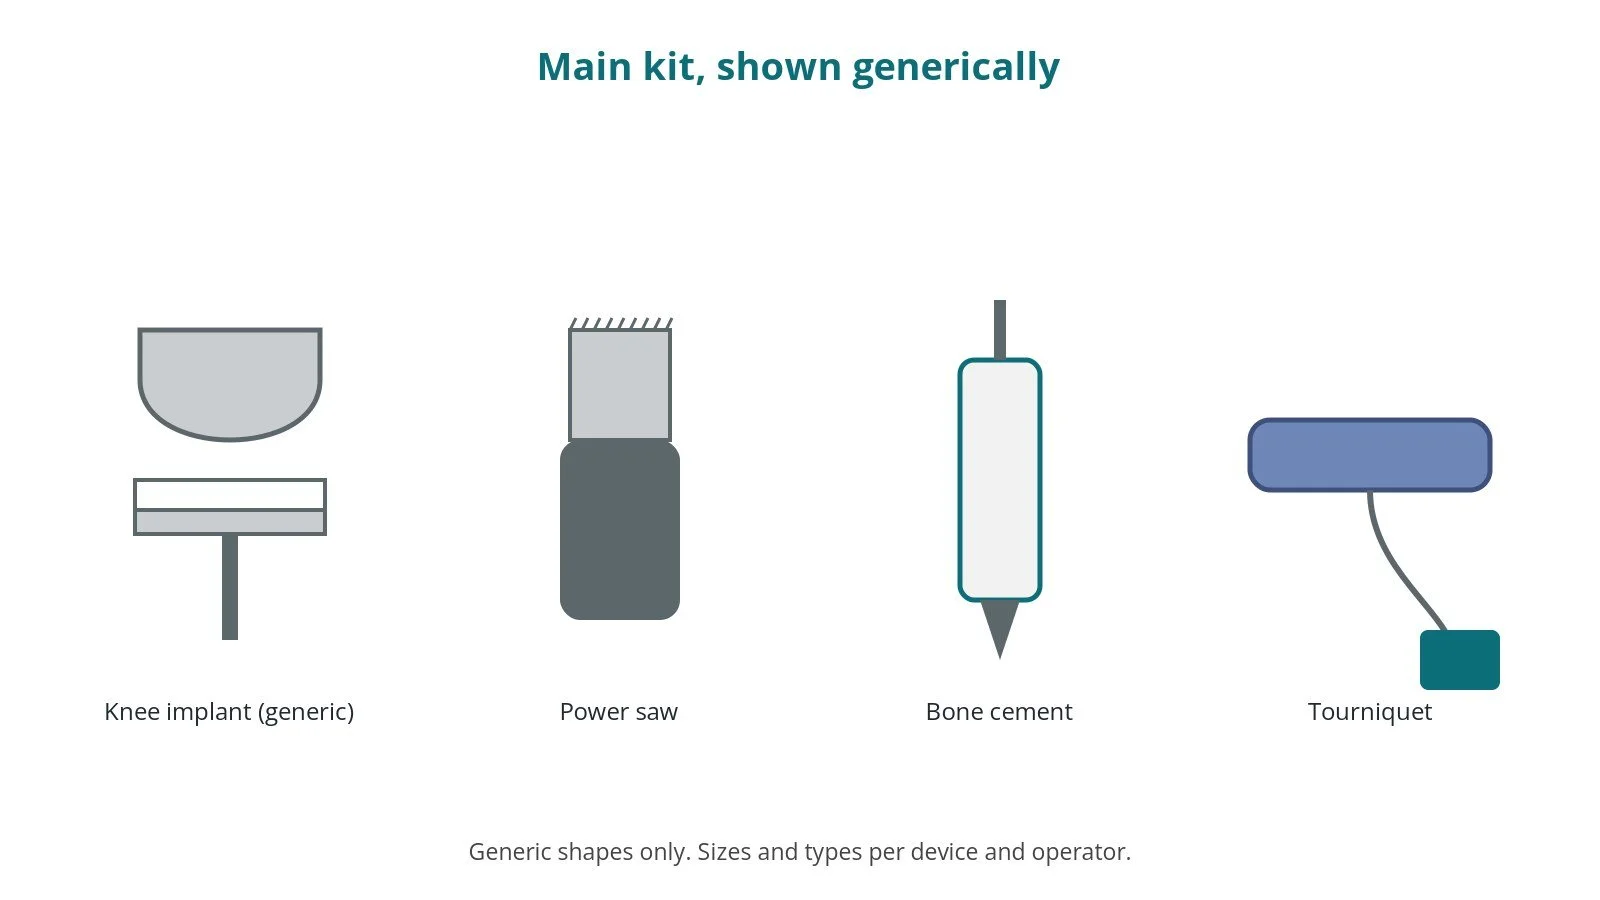
- knee replacement instrument trays and cutting guides
- implants: femoral, tibial and insert, sizes per device and operator; trial components
- power saw and drill with blades
- bone cement and mixing system, per device and operator
- tourniquet and cuff
- pulsed lavage
- local anaesthetic infiltration, as per centre protocol
- closure sutures or clips and dressings
Procedural steps
- Team brief, WHO sign in; side marked; implant check; anaesthesia
- Supine; leg holder; tourniquet; prep and drape; count
- Incision; joint exposed
- Bone cuts with guides
- Trials; balance; final implant check; cementing or press-fit
- Washout; closure; counts; implant log; sign out and handover
First time in theatre?
💡 First-time tip
- Implant check. Read back the implant type, side and size before opening, and record it in the implant log.
- Site and side. Check the marking at sign in and again before the cut.
- Counts matter. Swabs, needles, instruments and small implant parts are counted; speak up if one is missing.
- Tourniquet time. Note when the tourniquet goes up and call out times as per centre protocol.
- Cement timing. Know the cement timings and call them out if asked.
FAQ
How long does a knee replacement last?
Many last for many years; your surgeon will discuss what to expect.
Will I set off metal detectors?
Sometimes. Carry your implant information.
When can I kneel?
Kneeling may be uncomfortable; ask your team.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Knee replacement. nhs.uk/conditions/knee-replacement
- NICE. Joint replacement (primary): hip, knee and shoulder (NG157). nice.org.uk/guidance/ng157
- StatPearls (NCBI Bookshelf), search: total knee arthroplasty. ncbi.nlm.nih.gov/books
- National Joint Registry. njrcentre.org.uk
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.