Breast reconstruction: an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Breast reconstruction in one minute
What it is: surgery to rebuild a breast shape after mastectomy, using an implant, the patient's own tissue (flap), or both.
Who it is for: people having or who have had a mastectomy and who choose reconstruction.
Main risks: bleeding, infection, implant problems, flap failure, wound problems at the donor site.
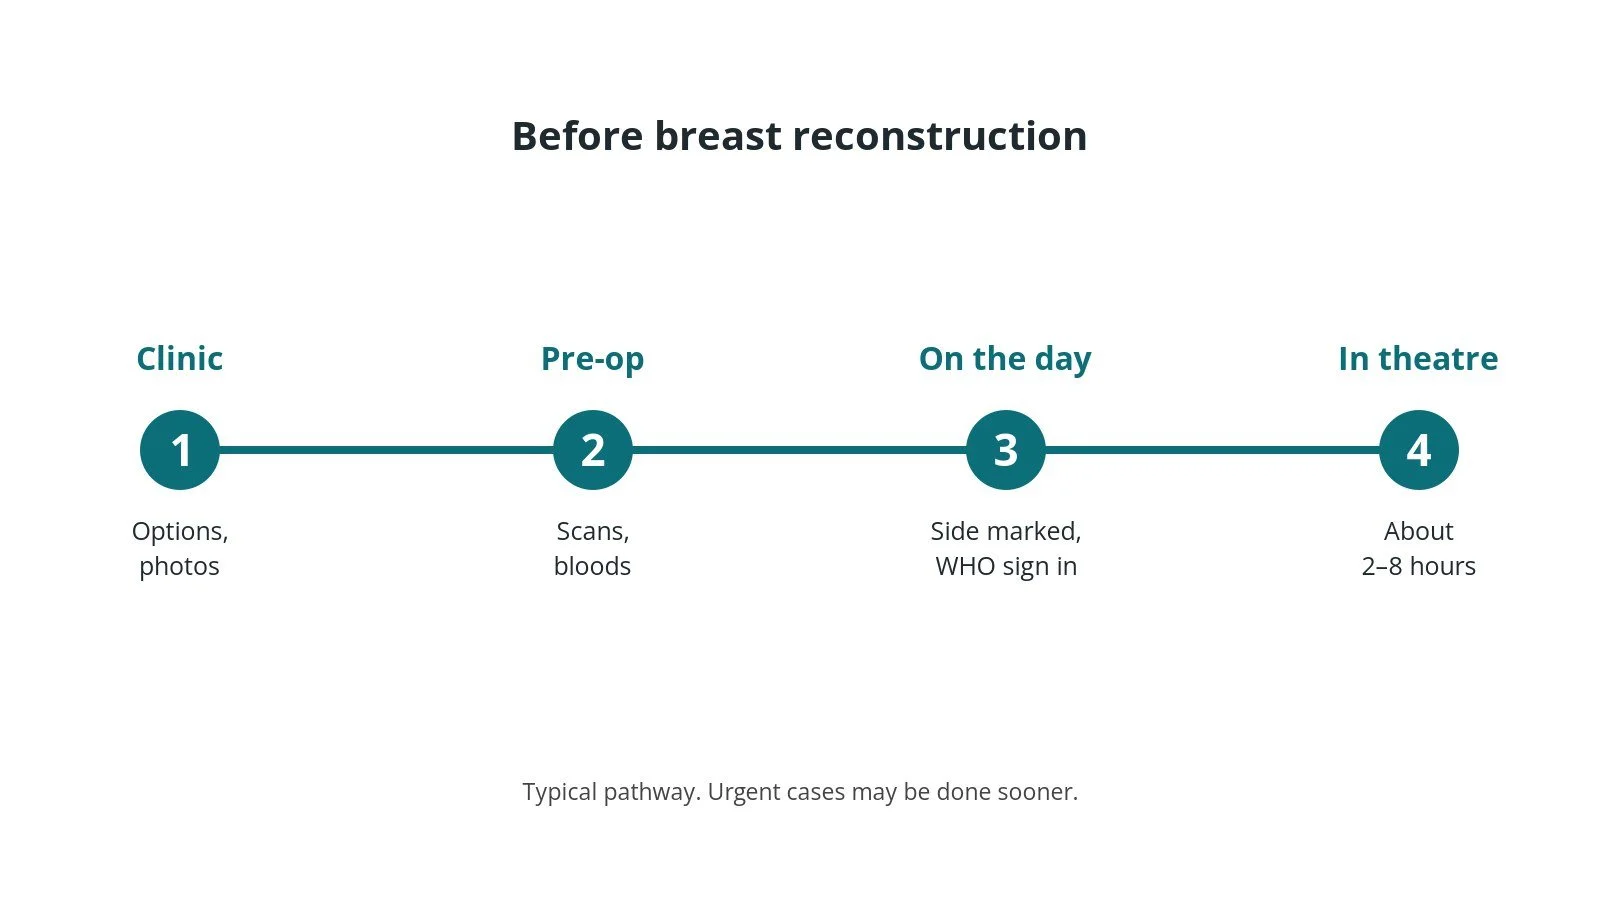
Usually: under general anaesthetic, 2–8 hours depending on type, 1–7 days in hospital.
On this page: What is breast reconstruction? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
What is breast reconstruction?
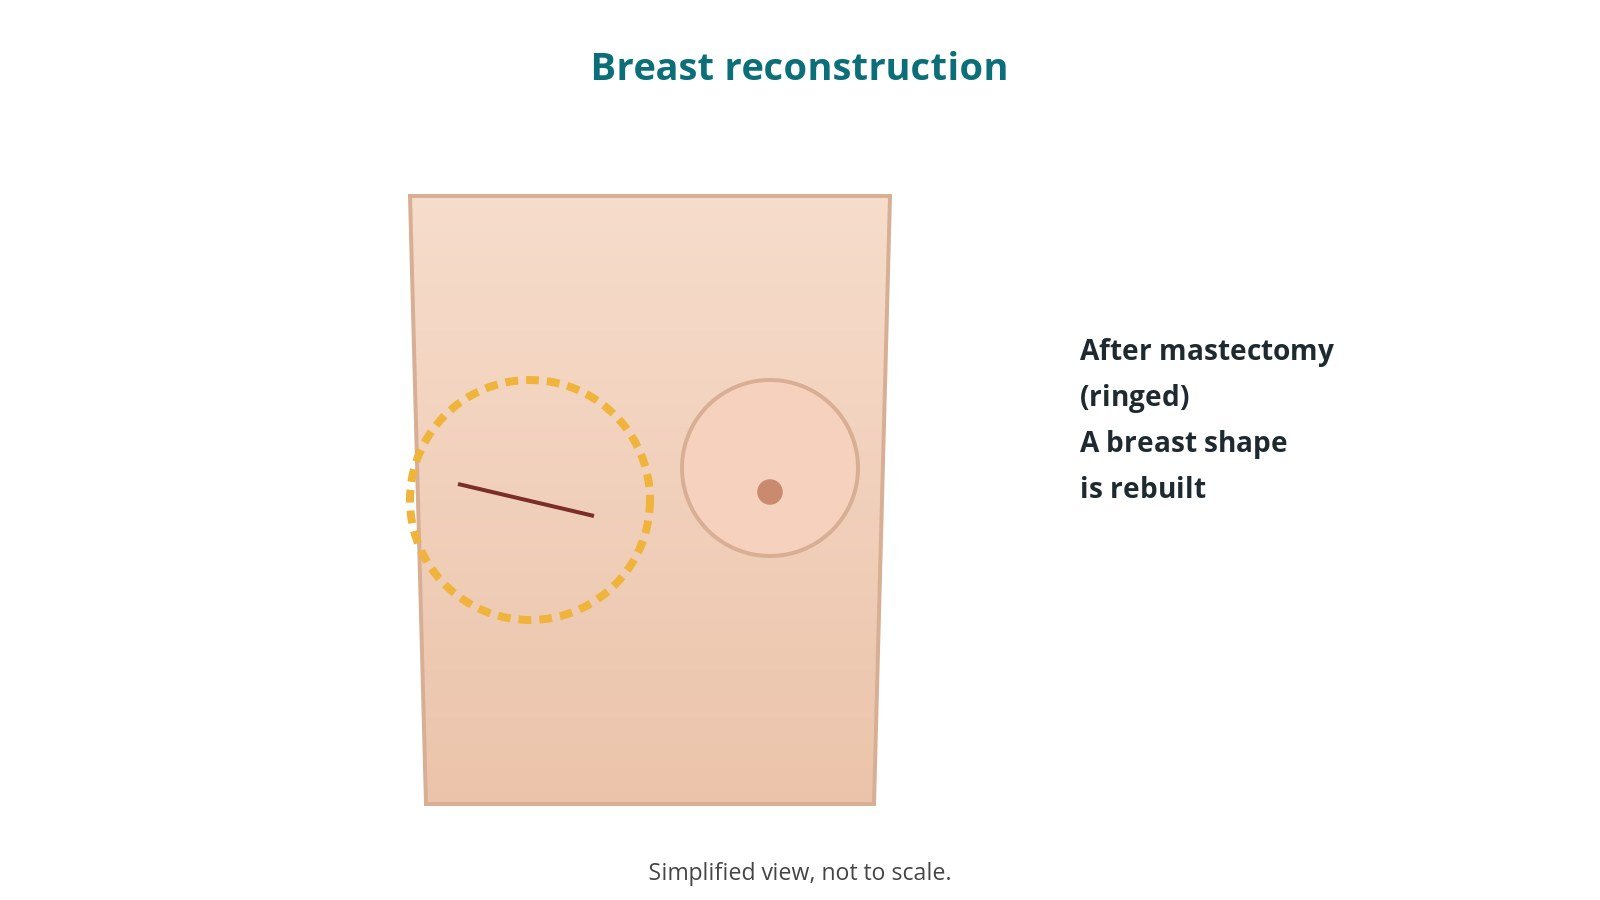
Breast reconstruction can be done at the same time as a mastectomy (immediate) or later (delayed).
- Implant-based: a breast implant or a tissue expander (gradually filled) is placed, sometimes with a mesh or tissue sheet, per surgeon.
- Own tissue (flap): skin and fat are moved from another area, often the lower abdomen or back. Free flaps are reconnected to blood vessels in the chest under a microscope.
Later operations may shape the other breast or make a nipple.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- people having a mastectomy for cancer or risk reduction
- people who have had a mastectomy in the past
The decision is made with your breast and plastic surgery team, who will talk through the options, timing, alternatives (including no reconstruction or an external prosthesis) and risks with you.
When is it done?
Most operations are planned; some are urgent. Before it, you usually have:
- an assessment and photographs (with consent)
- sometimes a scan of the abdominal blood vessels for a flap
- blood tests and an ECG
- advice to stop smoking
- a chance to ask questions and give consent
Step by step
1. Getting ready
Team brief and WHO checklist first, including the site and side marking and pre-op markings. The anaesthetic team and ODP give the anaesthetic (general, as per centre protocol); antibiotics and blood-clot prevention are given as per centre protocol. The circulating practitioner checks positioning, pressure areas, the diathermy plate and warming. The scrub practitioner sets up the instrument trolley and does the first count. The implant or expander check is done before opening; for flap surgery the microscope and flap monitoring equipment are checked and warming is maintained throughout.
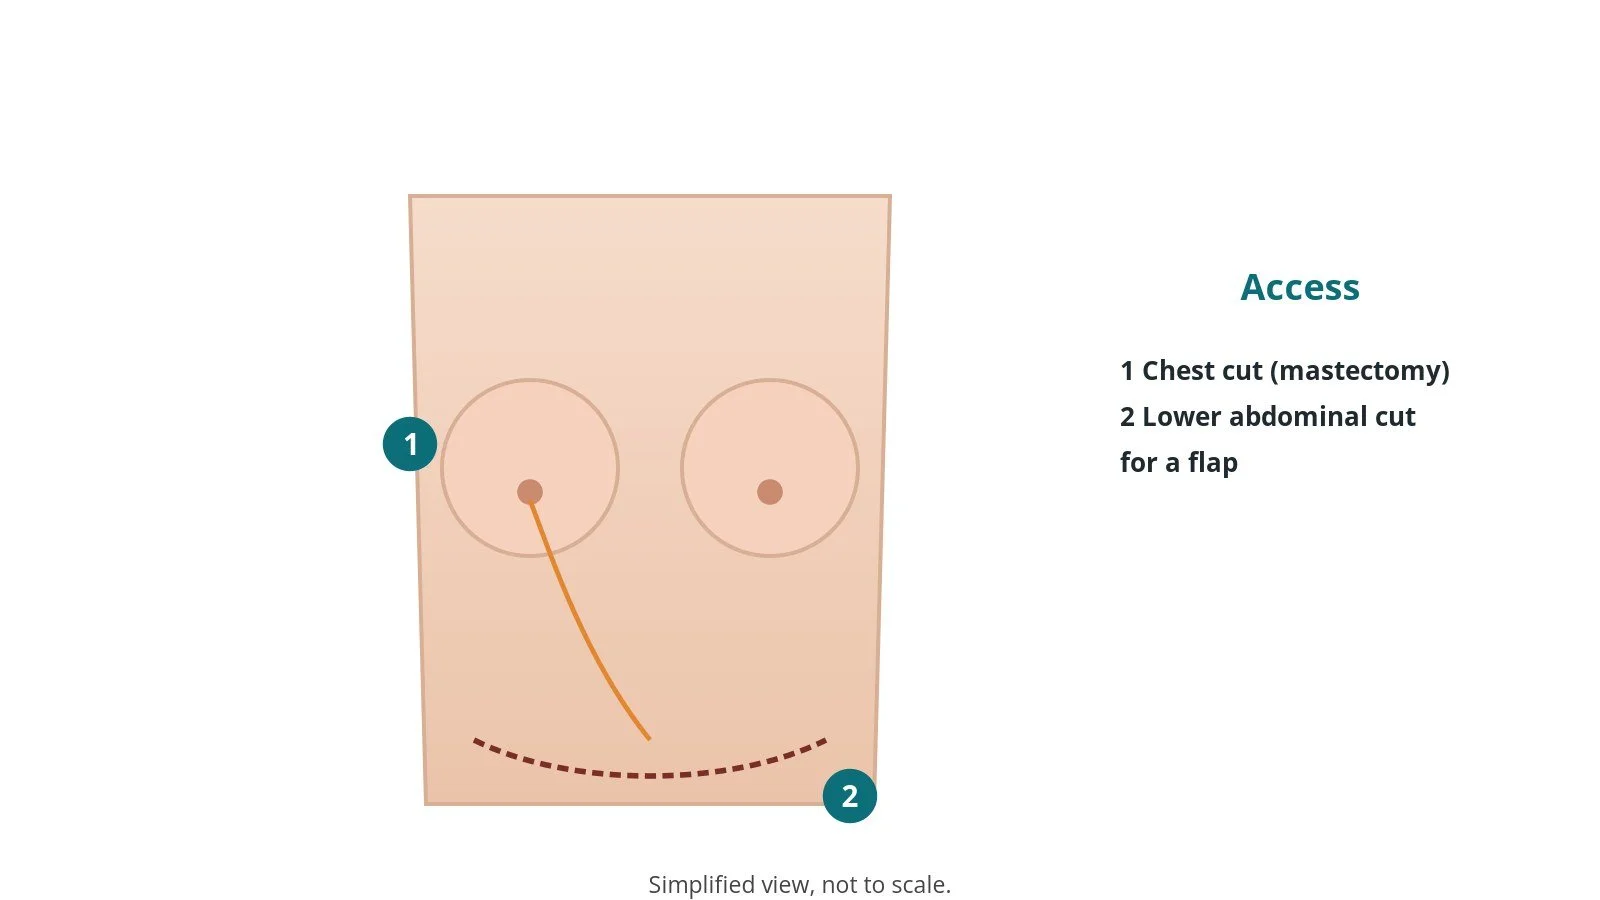
2. Access
Cuts follow the mastectomy markings on the chest; for a flap, a second cut on the lower abdomen.
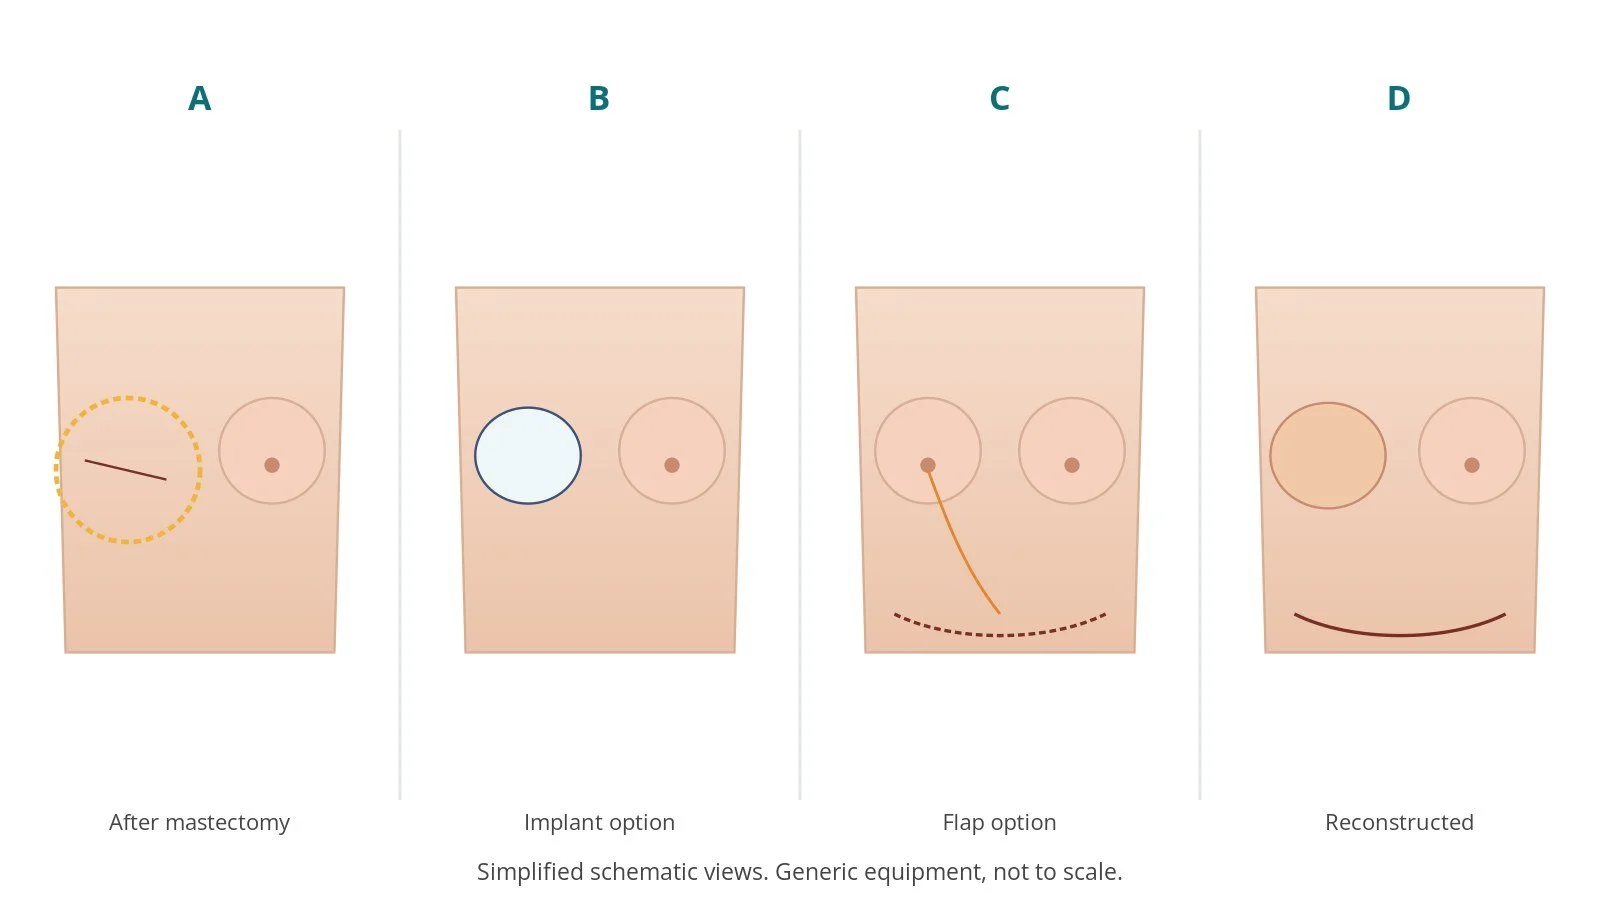
3. Rebuilding the breast
- A. After mastectomy. The breast tissue has been removed.
- B. Implant option. An implant or expander is placed under the skin or muscle.
- C. Flap option. Tissue is moved from the abdomen to the chest.
- D. Reconstructed. The new breast is shaped and closed.
For a free flap, the microscope join is the critical step; keep the patient warm and the theatre calm.
4. Finishing
Drains are placed, per surgeon, and the wounds closed and dressed. Final counts are confirmed, implant details recorded, and the patient goes to recovery with a full handover including flap checks.
Recovery and aftercare
- First days: for a flap, regular checks of colour and warmth.
- Going home: 1–2 days for implants; often 4–7 days for flaps.
- Drains: removed when output is low.
- Activity: avoid heavy lifting for about 6 weeks.
- Expanders: filled at clinic over weeks.
- Further surgery: may be planned for shape or nipple.
Call 999 if you have chest pain or sudden breathlessness. Contact your team if a wound becomes red, hot, swollen or leaky, a flap or graft changes colour, or you have a fever.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- bleeding or haematoma
- infection
- implant problems: infection, removal, capsule tightening
- flap failure (uncommon) needing return to theatre
- abdominal weakness or hernia after an abdominal flap
- wound healing problems
- asymmetry
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
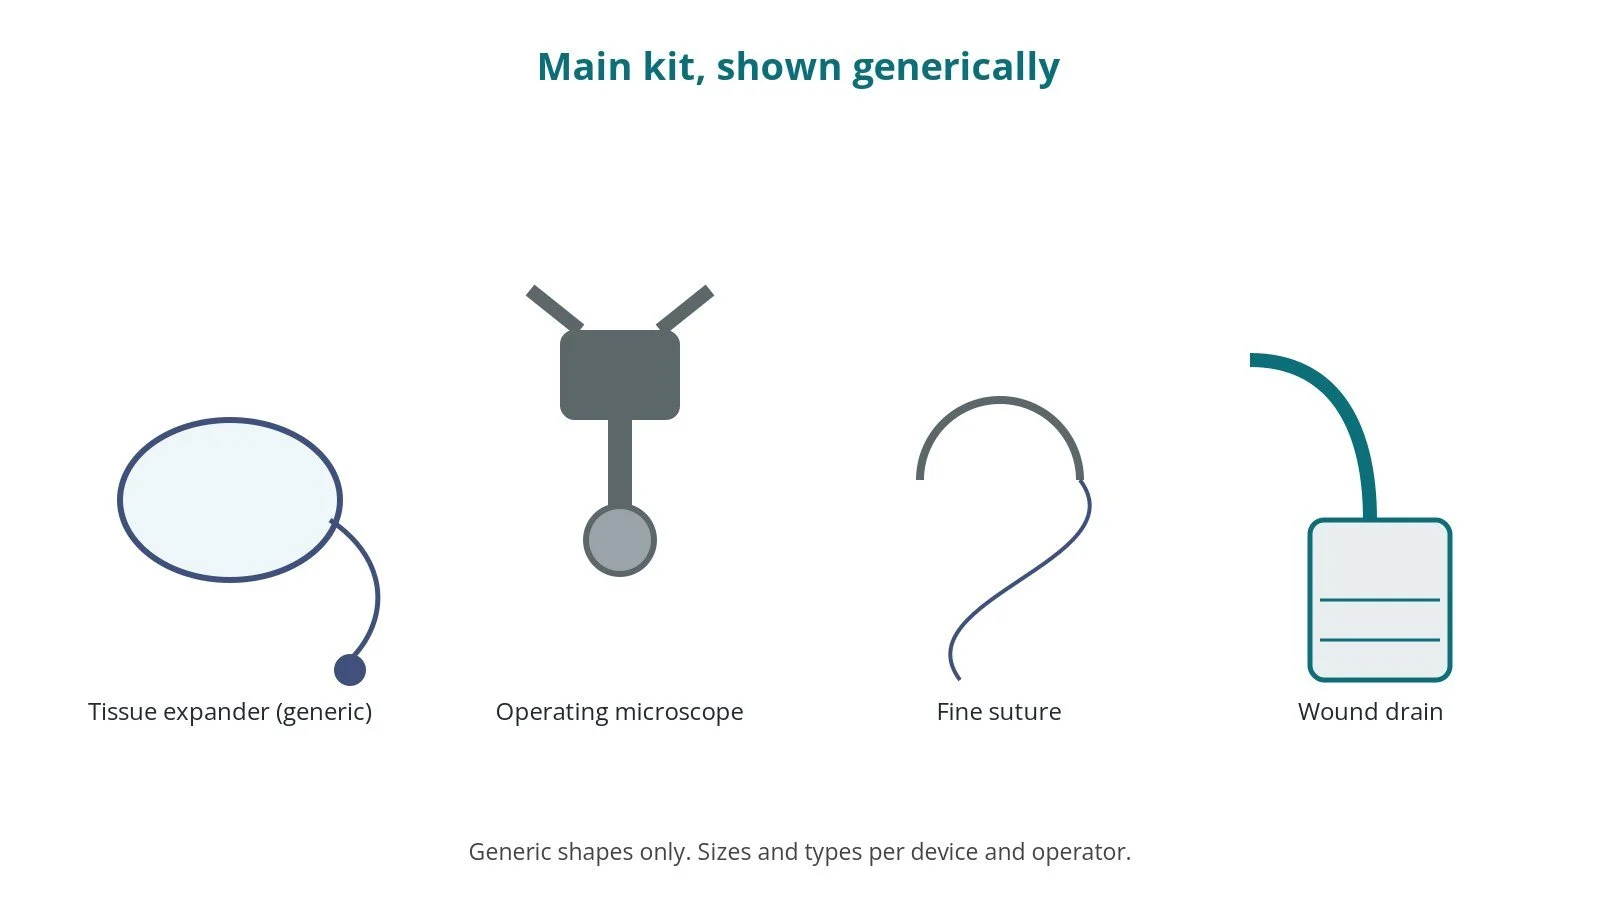
- plastic surgery instrument set
- implant or tissue expander, type and size per device and operator
- implant sizers and mesh or tissue sheet, per surgeon
- operating microscope and microvascular instruments for free flaps
- flap monitoring equipment, per centre
- drains and closure sutures
- support bra and dressings
Procedural steps
- Team brief, WHO sign in; side marked; implant check; anaesthesia
- Positioning; warming; prep; count
- Mastectomy or chest opened
- Implant placed, or flap raised and joined under microscope
- Shape checked; haemostasis
- Drains; closure; counts; implant log; sign out and handover with flap checks

First time in theatre?
💡 First-time tip
- Know your role. Scrub, circulating, anaesthetic and ODP each have their own checks; ask at the team brief.
- Counts matter. Swabs, needles and instruments are counted before, during and at closure; speak up if one is missing.
- Markings. Pre-op markings guide the whole operation; take care not to wipe them off during prep.
- Implant handling. Open implants at the last moment and limit handling, as per centre protocol.
- Microscope. Drape the operating microscope sterile and balance it before the case.
FAQ
Can it be done with my mastectomy?
Often, yes; your team will advise.
Implant or own tissue?
Each has pros and cons; discuss with your team.
Will it feel like my breast?
It looks like a breast but sensation is usually reduced.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Mastectomy. nhs.uk/conditions/mastectomy
- NICE. Early and locally advanced breast cancer: diagnosis and management (NG101). nice.org.uk/guidance/ng101
- StatPearls (NCBI Bookshelf), search: breast reconstruction. ncbi.nlm.nih.gov/books
- British Association of Plastic, Reconstructive and Aesthetic Surgeons. www.bapras.org.uk
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.