FESS and septoplasty: an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
FESS and septoplasty in one minute
What it is: FESS opens blocked sinuses with a camera through the nose; septoplasty straightens the septum (the wall between the nostrils).
Who it is for: people with long-term sinusitis or nasal polyps not helped by medicines, or a blocked nose from a bent septum.
Main risks: bleeding, infection, adhesions, change in smell, injury to the eye or brain covering (rare).
Usually: under general anaesthetic, 1–2 hours, often a day case.
On this page: What are FESS and septoplasty? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
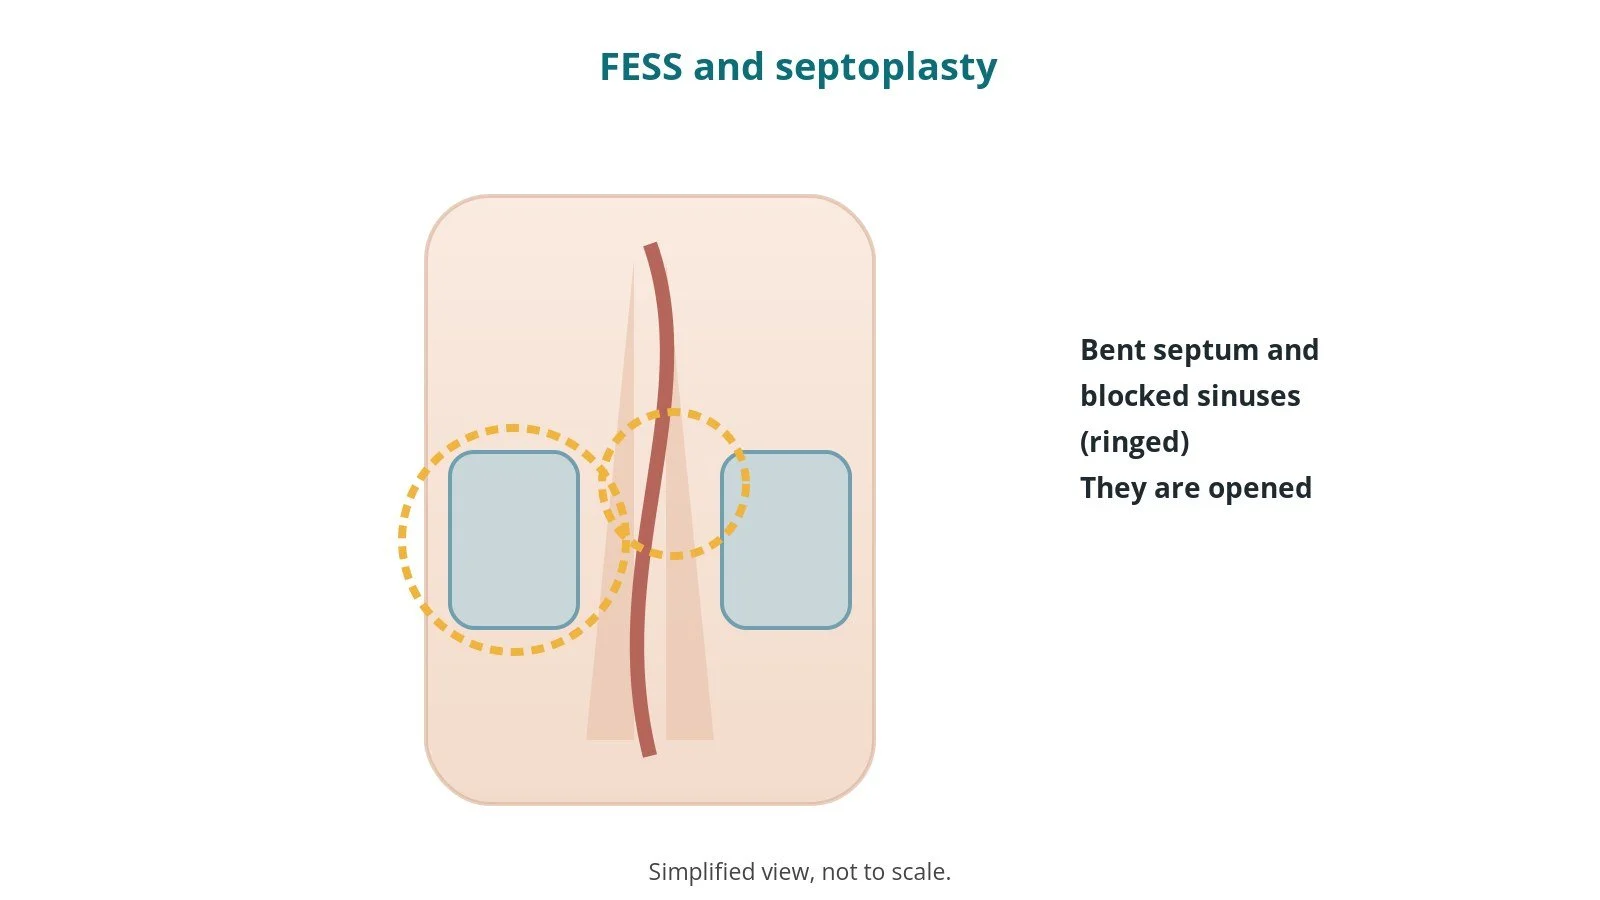
What are FESS and septoplasty?
The sinuses are air spaces around the nose. Long-term inflammation (chronic rhinosinusitis) or polyps can block them.
- FESS (functional endoscopic sinus surgery): the surgeon uses a thin endoscope in the nose to widen the natural drainage openings and remove polyps, sometimes with image guidance.
- Septoplasty: the surgeon lifts the lining of the septum and straightens or removes the bent cartilage and bone.
They are often done together. There are no cuts on the face.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- chronic sinusitis or polyps not helped by medicines
- a blocked nose from a bent septum
- sometimes to give access for other nose surgery
The decision is made by your ENT team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
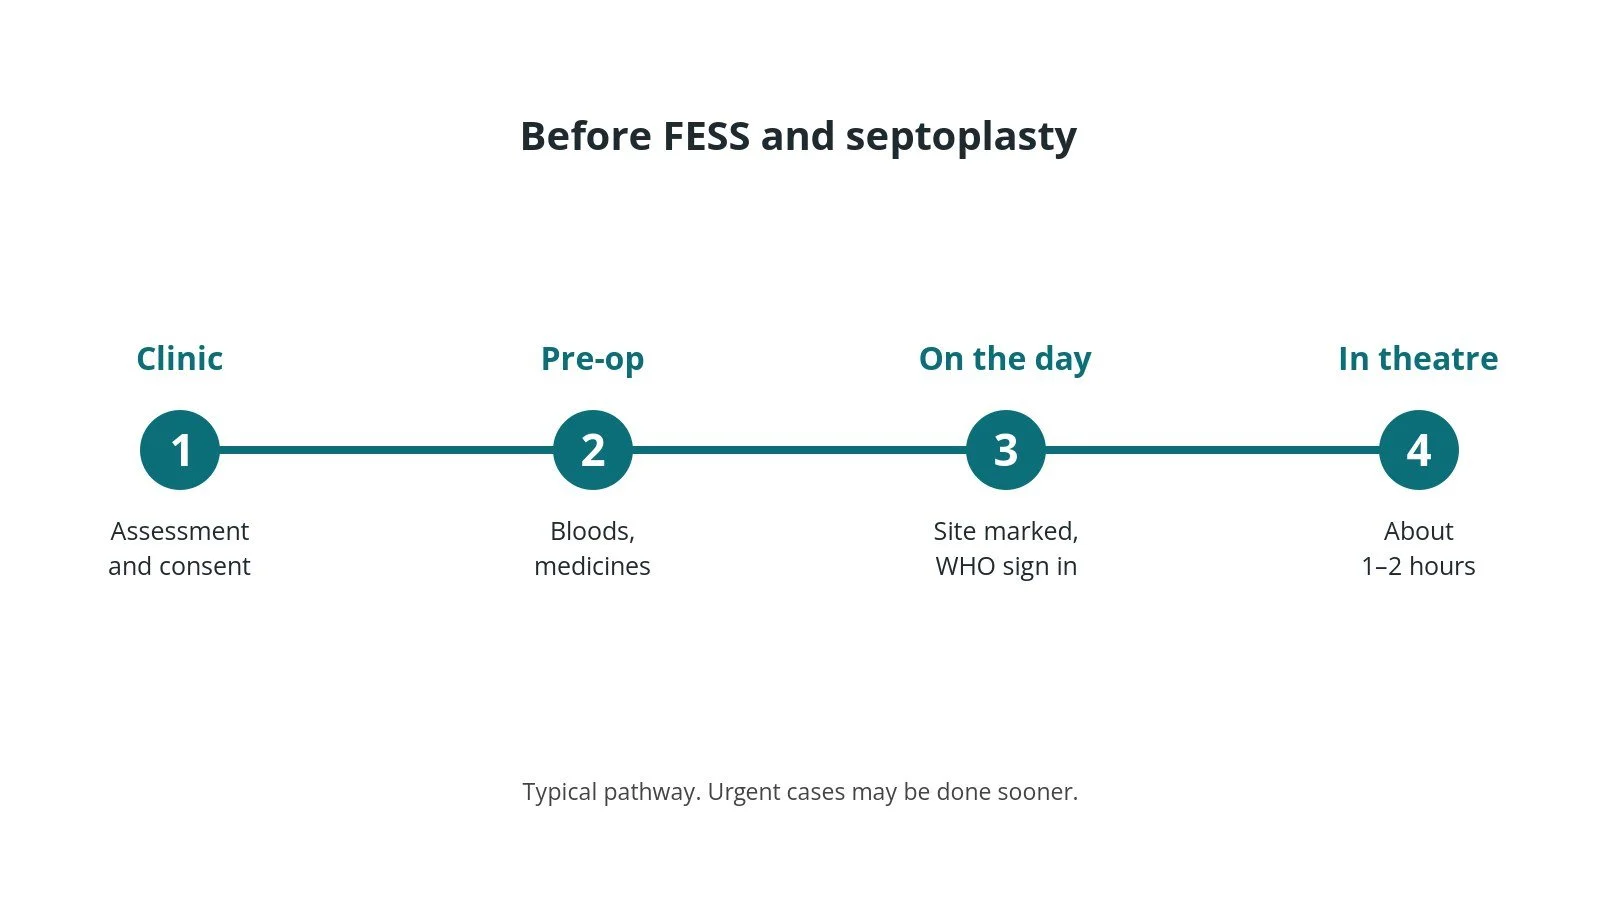
Most operations are planned; some are urgent. Before it, you usually have:
- a CT scan of the sinuses
- a trial of nasal sprays and medicines
- a review of medicines, especially blood thinners, as per centre protocol
- a chance to ask questions and give consent
Step by step
1. Getting ready
Team brief and WHO checklist first, including the side and site, and the scan on display. The anaesthetic team and ODP give the anaesthetic (general, often with lower blood pressure to reduce bleeding, as per centre protocol); medicines are given as per centre protocol. The circulating practitioner checks positioning, pressure areas, the diathermy plate and warming. The scrub practitioner sets up the instrument trolley and does the first count. The endoscopy stack and image guidance (if used) are checked; the eyes are taped but left visible to the team, per centre protocol.
2. Access
No skin cuts: the endoscope and instruments pass through the nostrils.
3. Opening the sinuses
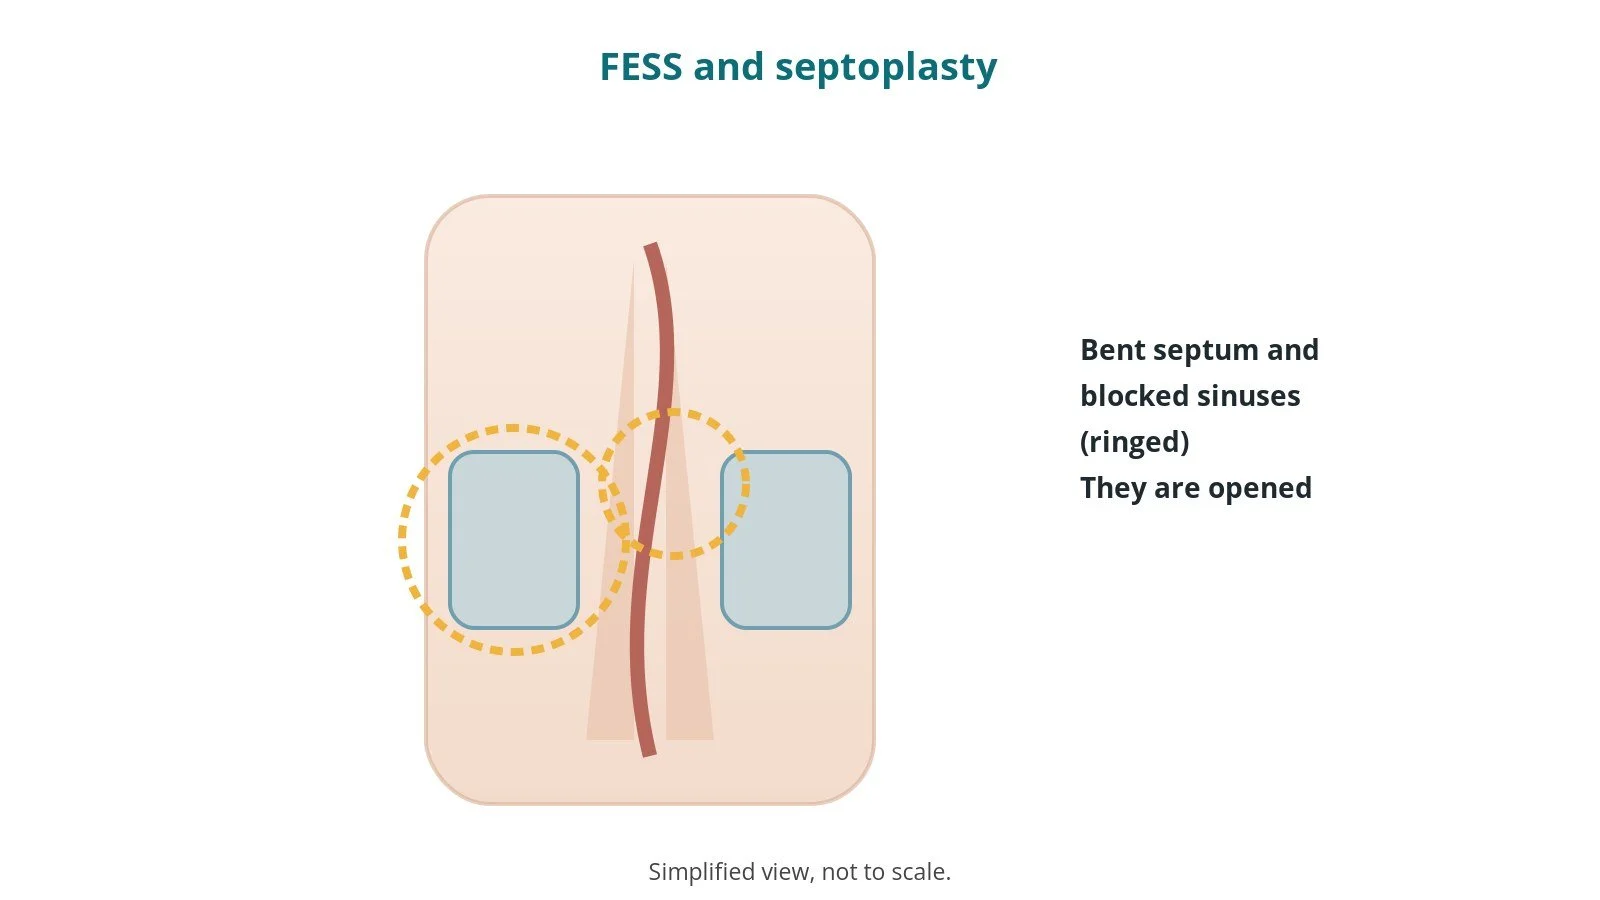
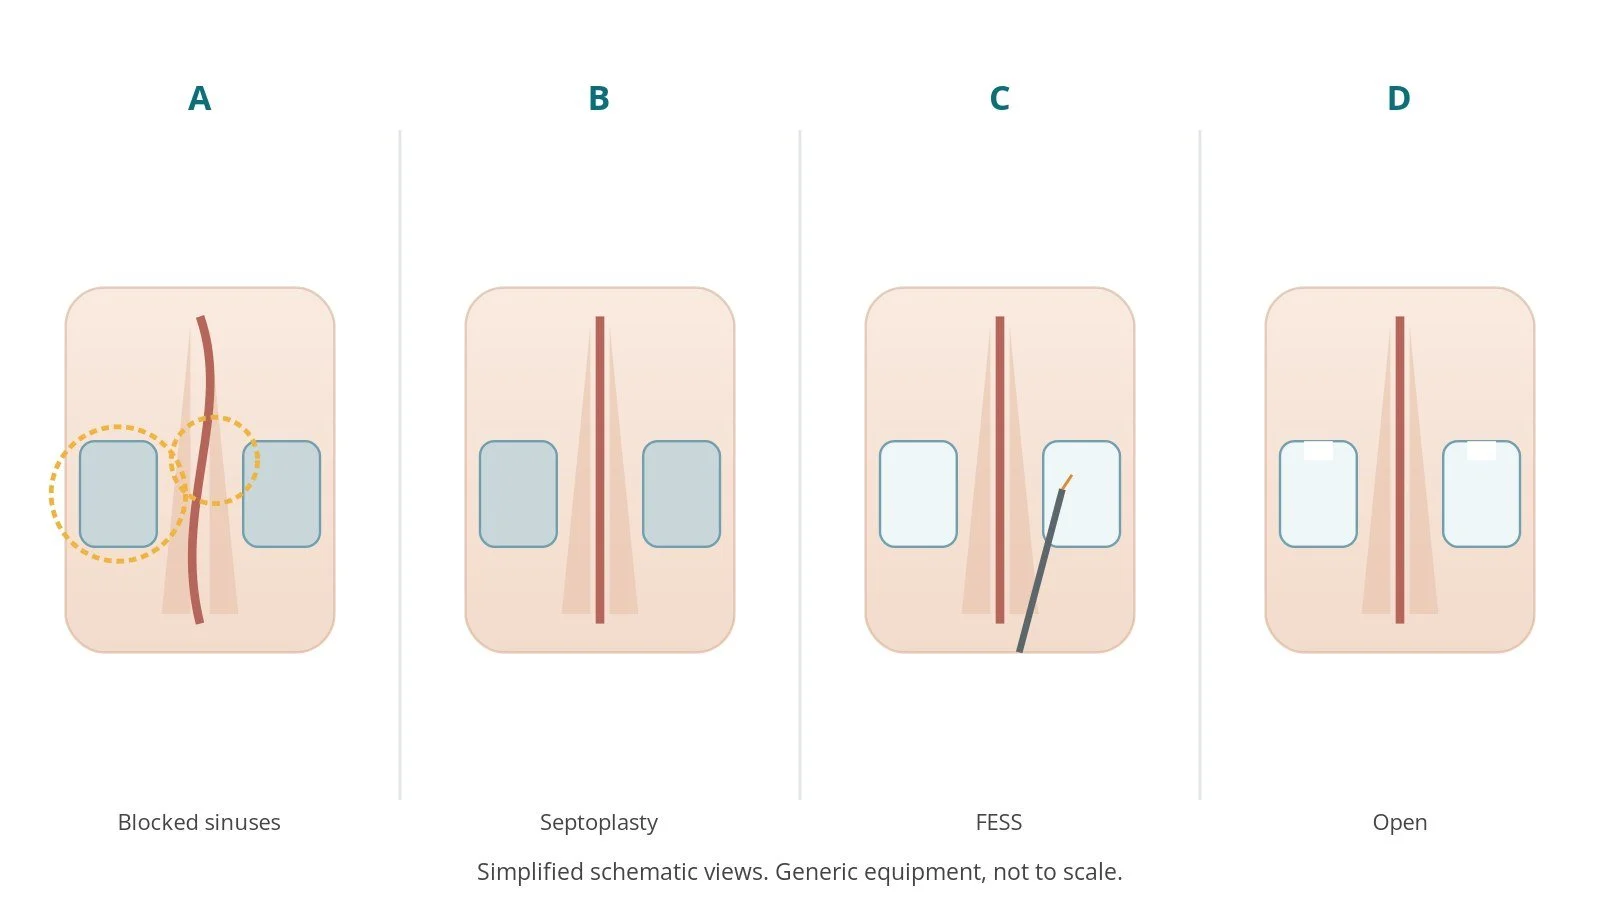
- A. Blocked sinuses. The bent septum and blocked sinuses are seen.
- B. Septoplasty. The septum is straightened.
- C. FESS. The sinus openings are widened with the endoscope.
- D. Open. The sinuses drain freely; packs or splints are placed if needed.
The team watches the eyes during sinus work, and the scan stays on screen for the surgeon.
4. Finishing
Bleeding is controlled; nasal splints or dissolvable packs may be placed, per surgeon. Final counts (including any throat pack) are confirmed, specimens labelled, and the patient goes to recovery with a full handover.
Recovery and aftercare
- Same day: usually home the same day.
- Blocked nose: for 1–2 weeks; this is normal.
- Saline rinses: as advised to clear crusts.
- Avoid: nose blowing, heavy lifting and flying for a short time, as advised.
- Splints: removed at clinic if used.
- Follow-up: clinic review.
Call 999 if you are coughing or vomiting a lot of blood or have difficulty breathing. Contact your team if you have bleeding, a high temperature, increasing pain or are unable to eat or drink.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- bleeding
- infection
- adhesions (scar bands) in the nose
- change in sense of smell
- hole in the septum (rare)
- eye injury or leak of brain fluid (rare)
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
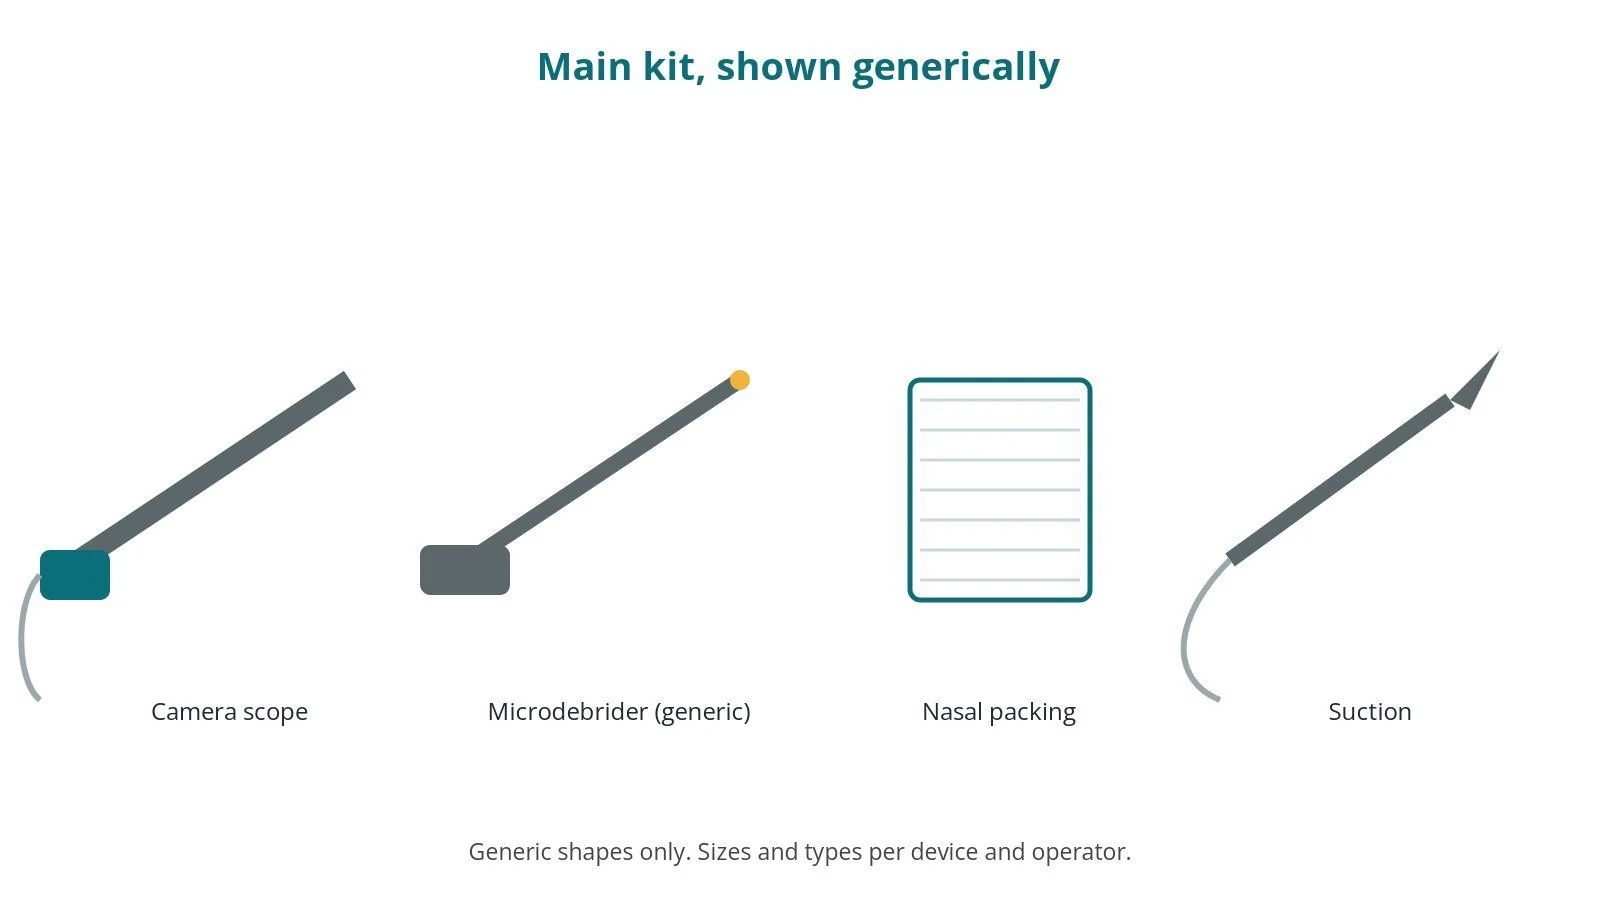
- endoscopy stack: camera, light source, monitor
- rigid endoscopes, angles per surgeon
- sinus instruments and microdebrider, per surgeon
- image-guidance system, per centre
- topical vasoconstrictor, as per centre protocol
- nasal splints or dissolvable packs, per surgeon
- throat pack, as per centre protocol
Procedural steps
- Team brief, WHO sign in; scan displayed; anaesthesia
- Head-up position; eyes protected; prep; count
- Nose prepared with topical medicine
- Septoplasty
- FESS: sinus openings widened
- Packs or splints; counts; throat pack out; sign out and handover

First time in theatre?
💡 First-time tip
- Know your role. Scrub, circulating, anaesthetic and ODP each have their own checks; ask at the team brief.
- Counts matter. Swabs, needles and instruments are counted before, during and at closure; speak up if one is missing.
- Scan on screen. Keep the CT scan displayed for the surgeon throughout.
- Eyes. Do not cover the eyes completely; the team needs to see them.
- Throat pack. If a throat pack is used, it is recorded and its removal confirmed, as per centre protocol.
FAQ
Will my face be bruised?
Usually not; there are no cuts on the face.
When can I breathe through my nose?
It improves as swelling settles over weeks.
Will polyps come back?
They can; sprays help keep them down.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Sinusitis (sinus infection). nhs.uk/conditions/sinusitis-sinus-infection
- StatPearls (NCBI Bookshelf), search: functional endoscopic sinus surgery. ncbi.nlm.nih.gov/books
- StatPearls (NCBI Bookshelf), search: septoplasty. ncbi.nlm.nih.gov/books
- ENT UK. www.entuk.org
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.