Transcaval TAVI (caval-aortic access): a Cath Lab 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Transcaval TAVI in one minute
What it is: TAVI replaces a narrowed aortic valve using a catheter. In transcaval TAVI, the team goes up the femoral vein to the main vein in the abdomen (the inferior vena cava, IVC), makes a small controlled passage across into the aorta next to it, delivers the valve through it, and then closes the passage with a plug.
Who it is for: people with severe aortic stenosis chosen for TAVI by a heart team, whose leg arteries are too small or diseased for the femoral artery route, and whose CT shows a safe crossing point.
Main risks: bleeding into the back of the abdomen (retroperitoneum), a persistent connection between the aorta and IVC, the plug moving, and the usual TAVI risks. Your team will explain your own risk.
Usually: under general anaesthetic or sedation, about 2 to 3 hours, often home after a few nights.
On this page: What is transcaval TAVI? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in the lab? · FAQ
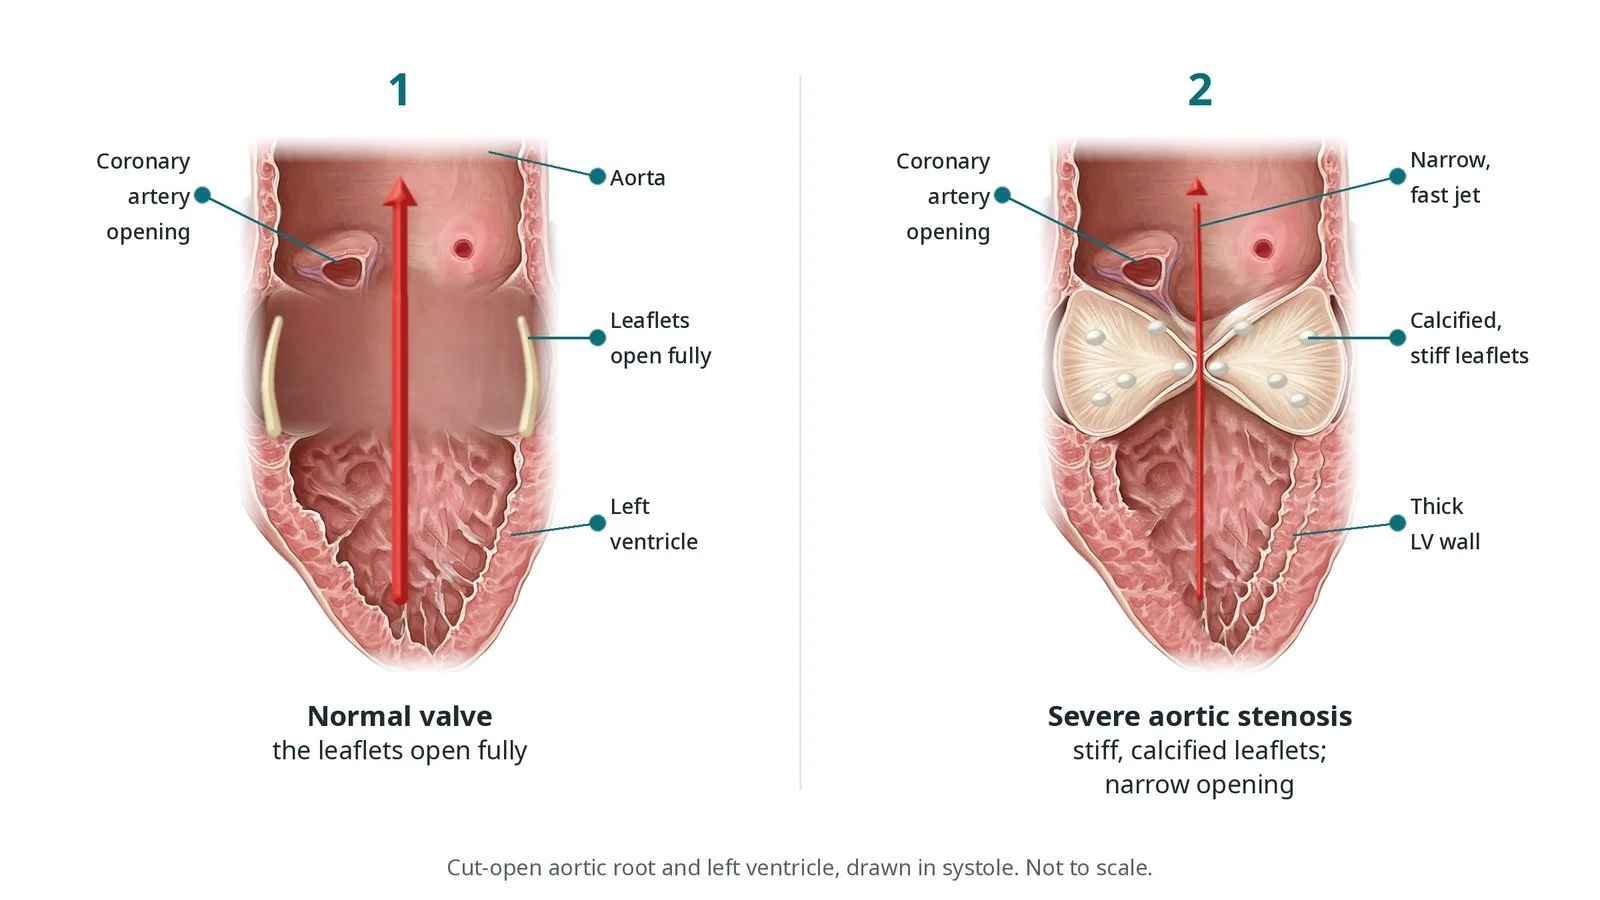
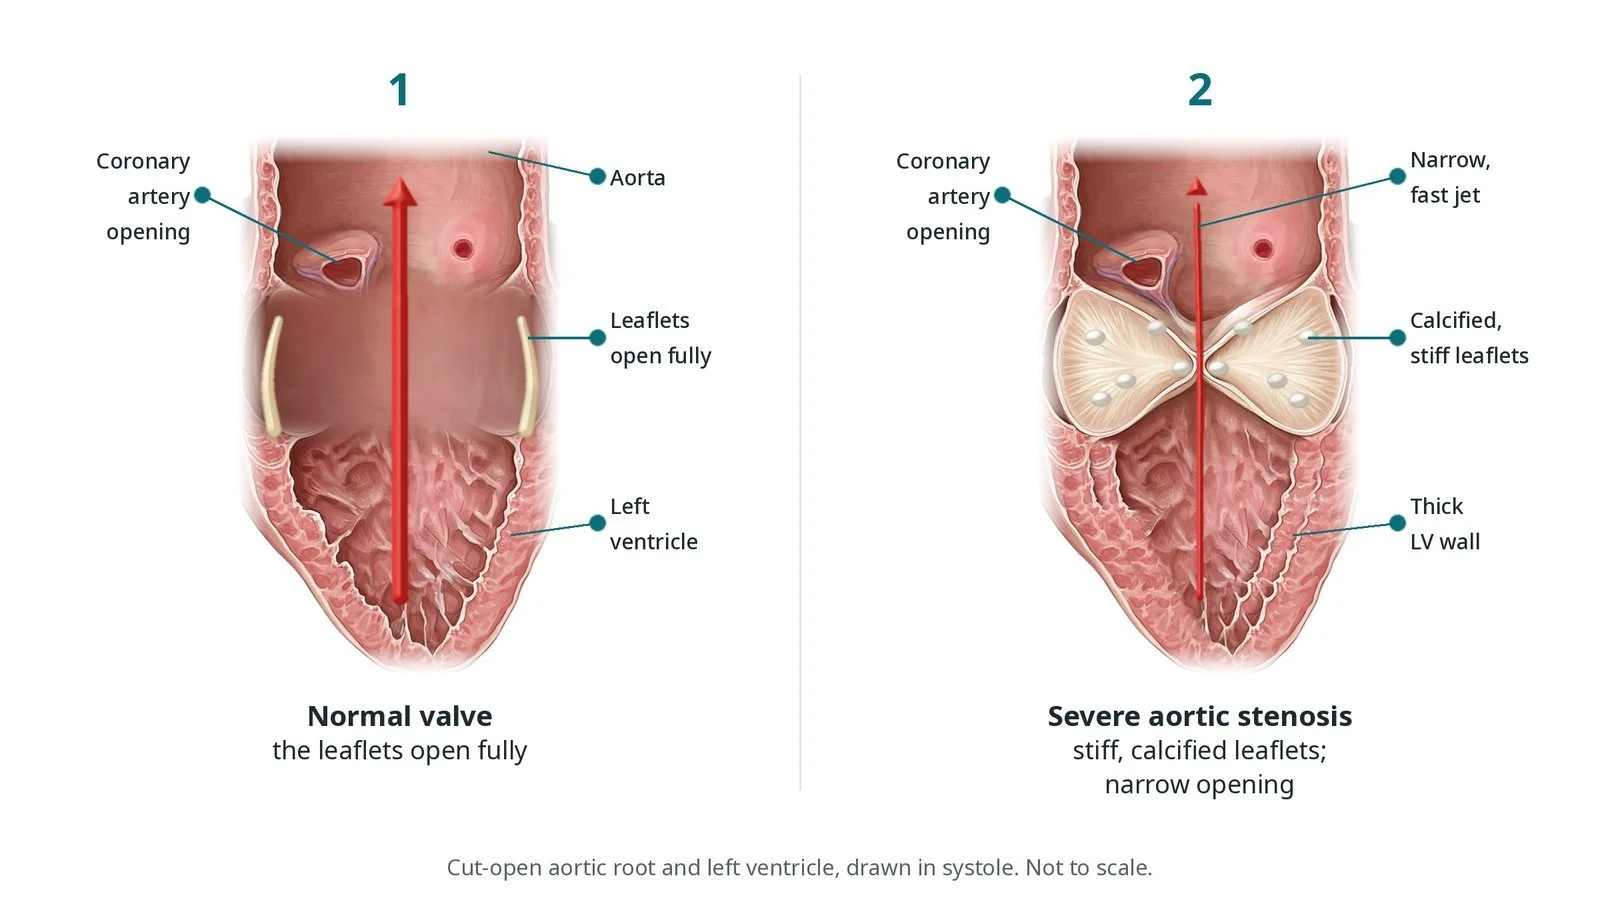
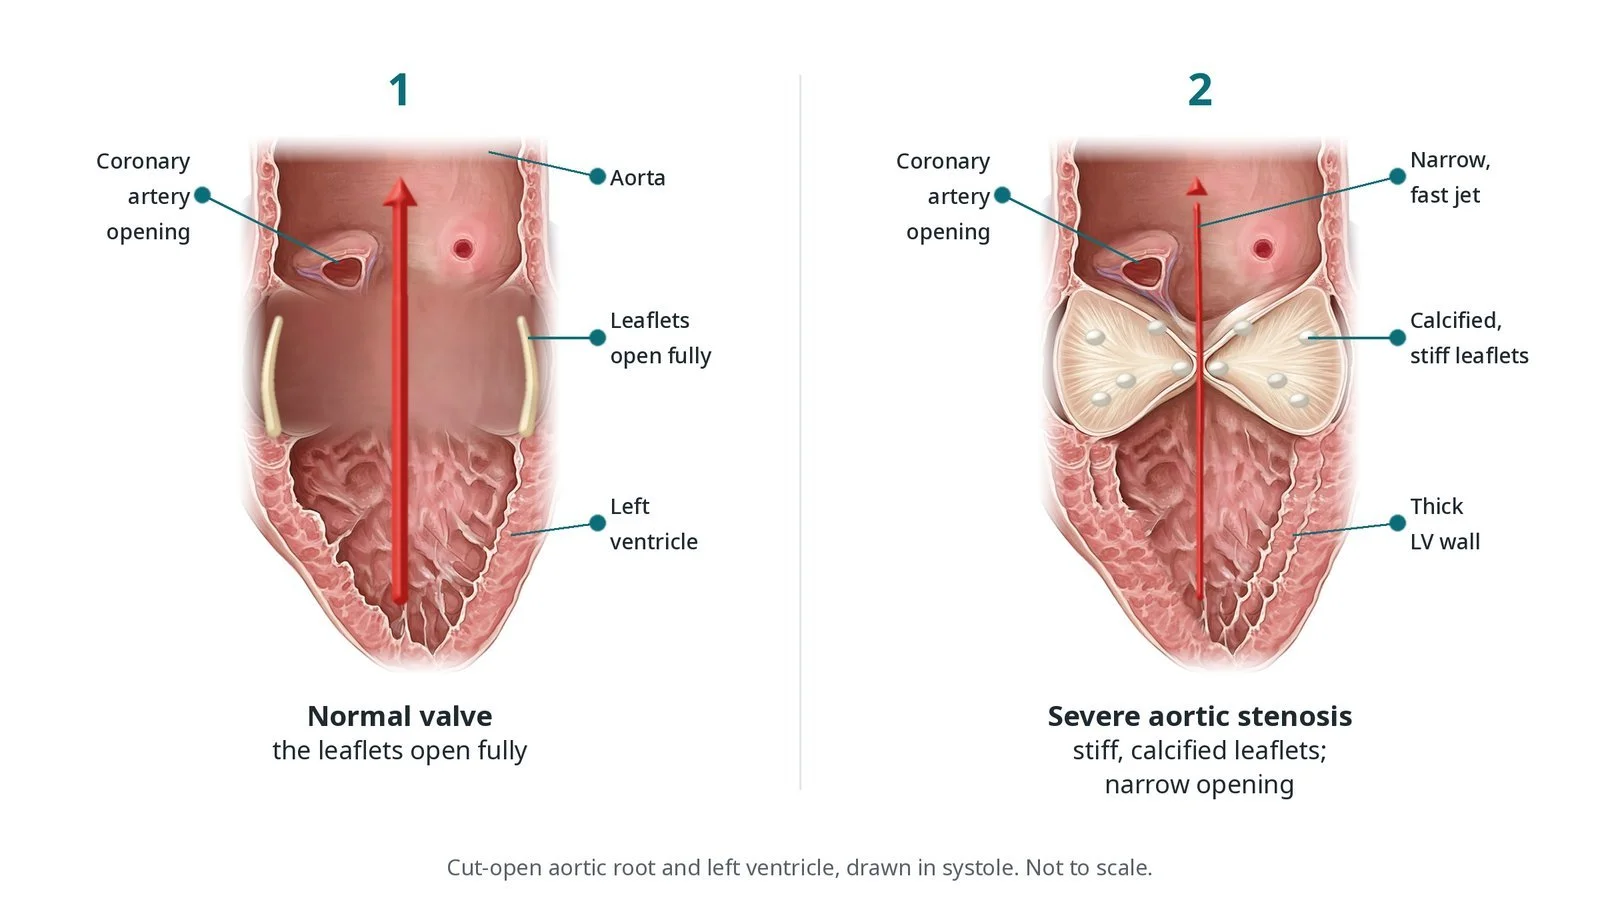
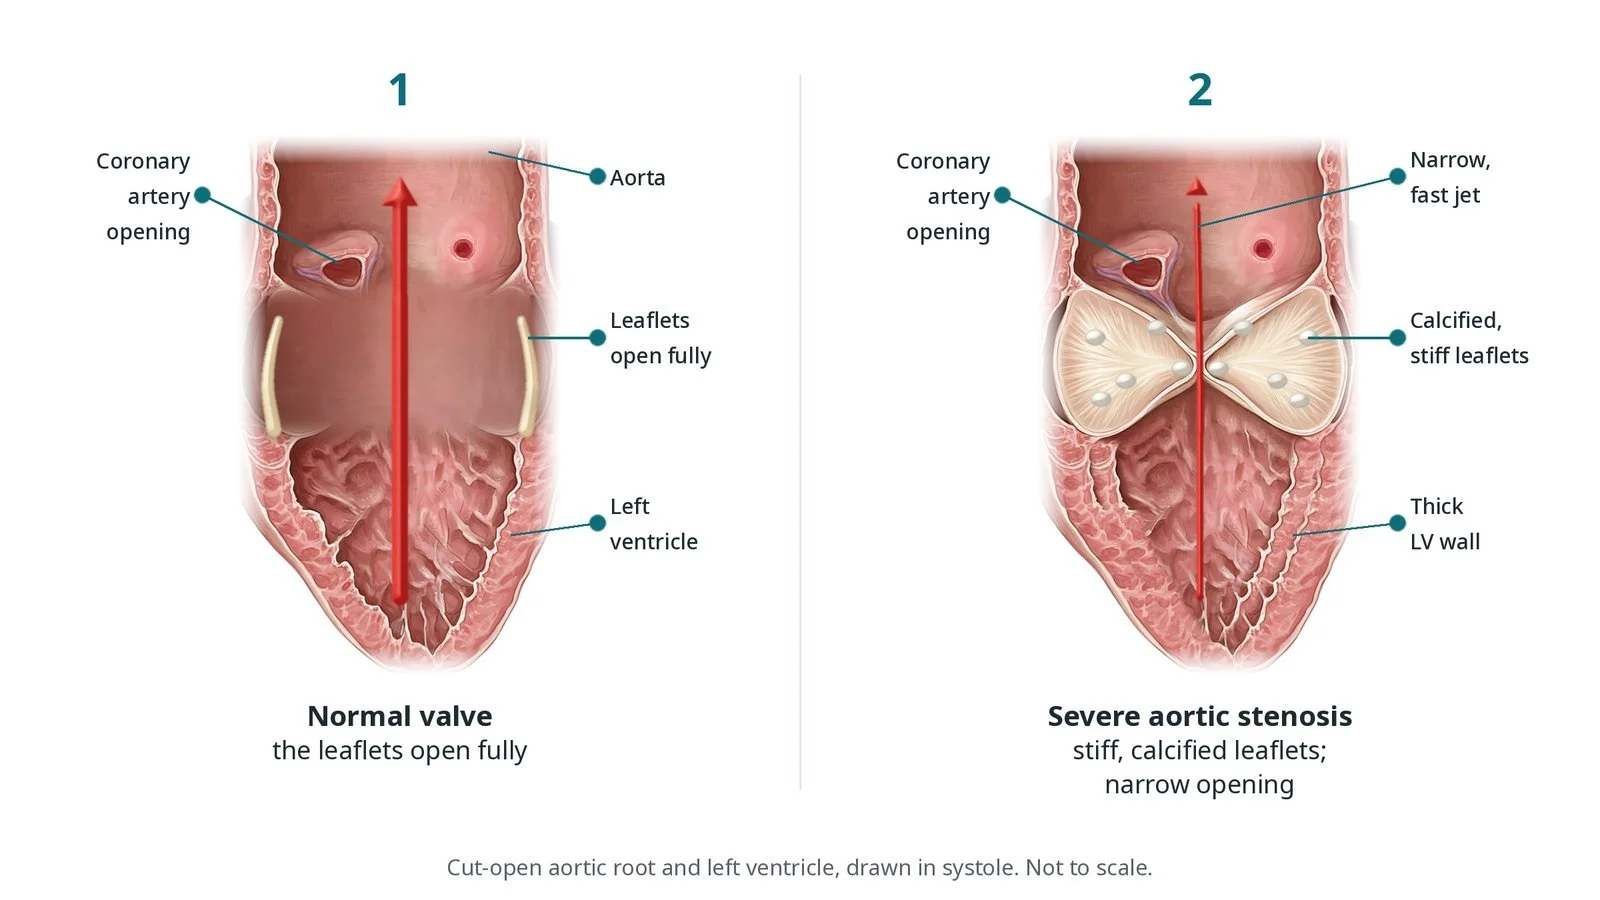
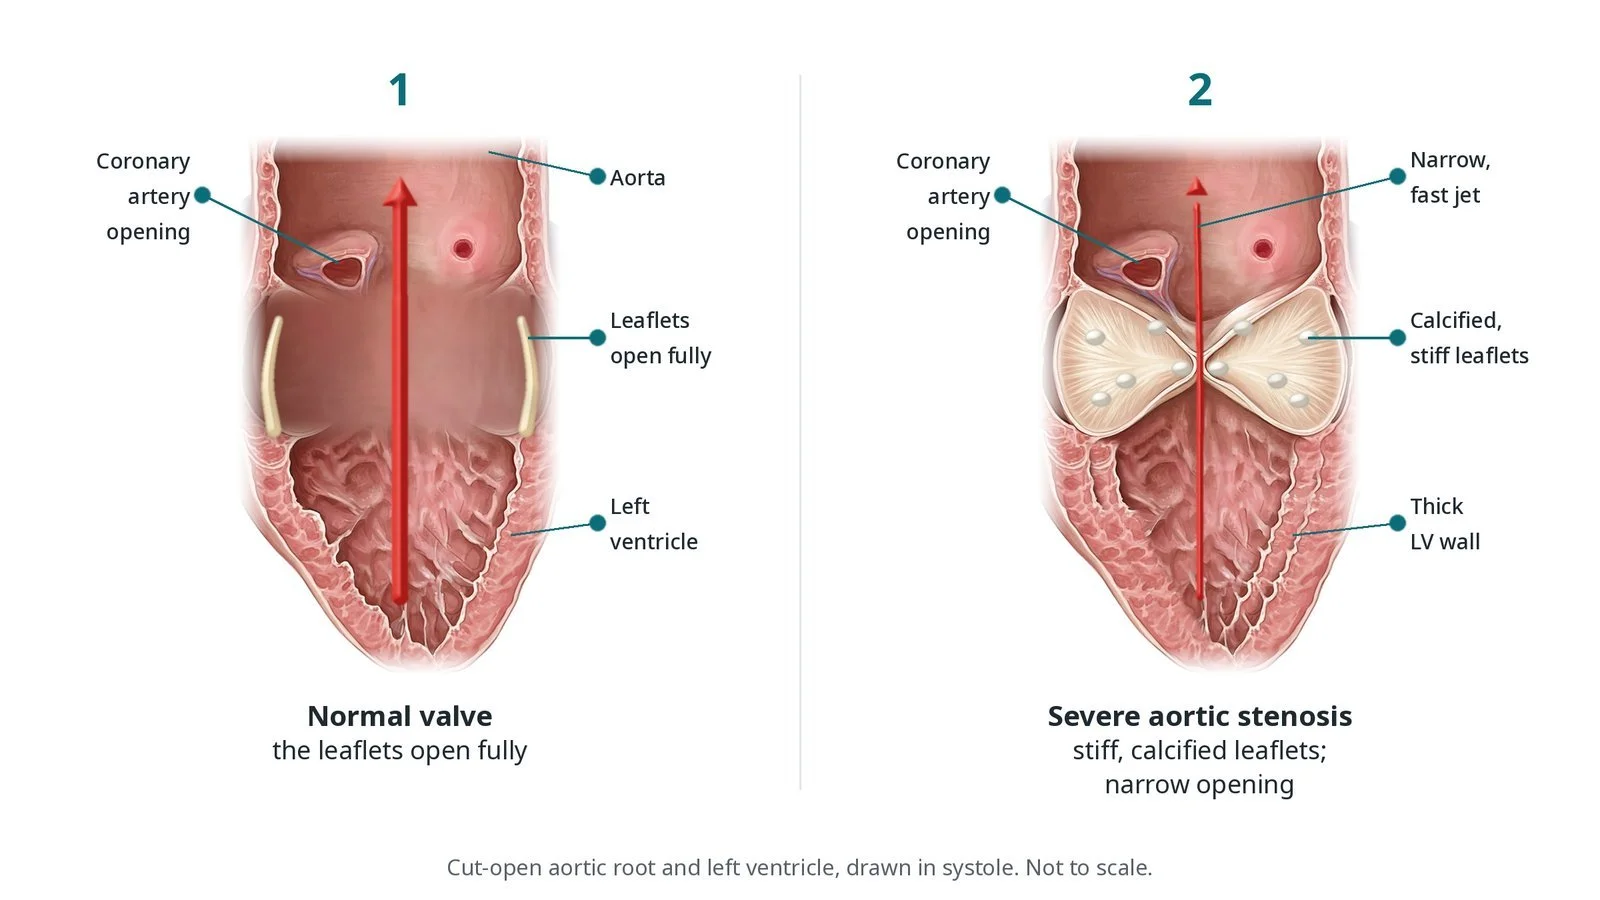
Normal valve vs severe aortic stenosis (AS), cut-open aortic root drawn in systole. Normal: the leaflets open fully against the wall. Severe AS: calcified, stiff leaflets, a narrow fast jet and a thick LV wall. The coronary arteries start from the sinuses just above the valve.
What is transcaval TAVI?
The aortic valve lets blood leave the heart into the aorta. In aortic stenosis, it becomes stiff and narrowed, usually from calcium build-up with age, causing breathlessness, chest pain, dizziness or blackouts. TAVI (transcatheter aortic valve implantation) places a new valve inside the old one using a catheter, without open-heart surgery. See the main TAVI guide.
Most TAVIs are done through the femoral artery in the groin (transfemoral). In some people the leg and pelvic arteries are too narrow, diseased, twisted or heavily calcified for the large delivery system. An alternative access route is then needed. The main options are transaxillary/subclavian (under the collarbone), transcarotid (the neck), transcaval (from the femoral vein into the aorta), and surgical routes through the chest wall. The heart team chooses the route using CT.
Transcaval access uses the fact that the IVC (the large vein returning blood from the legs) lies right next to the abdominal aorta. Veins are usually larger and healthier than diseased leg arteries, so the large TAVI sheath travels up the femoral vein. At a chosen point, an electrified wire crosses from the IVC into the aorta. The passage is enlarged for the sheath, the valve is delivered in the usual way, and the hole is then closed with a plug (occluder). Because the aorta lies next to the low-pressure IVC, small leaks usually drain back into the vein rather than into the abdomen.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
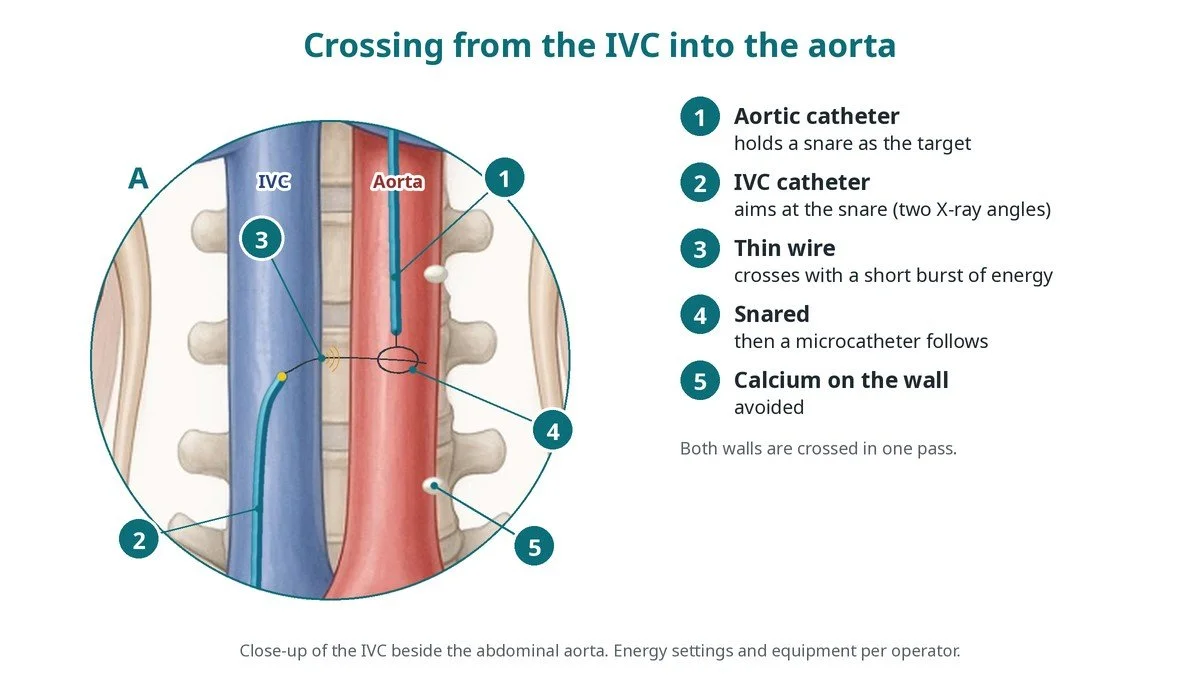
Close-up: the aortic catheter holds a snare as a target (1); the IVC catheter aims at it (2) and a thin wire crosses with a short burst of energy (3) and is snared (4). The crossing level is planned on CT away from calcium (5).
Who is it for?
NICE guidance on heart valve disease (NG208) recommends TAVI or surgery for severe symptomatic aortic stenosis based on age, risk and a heart team decision, and NICE interventional guidance on TAVI (HTG446) supports its use. The ESC/EACTS valvular heart disease guidelines state that transfemoral access is preferred and that non-transfemoral access may be considered in people unsuitable for surgery and for transfemoral TAVI. The choice between alternative routes depends on the person's anatomy and the centre's experience.
For transcaval access, CT must show a crossing point (often at the level of the lower lumbar spine) where the aortic wall is free of heavy calcium, there is no bowel or other structure between the vessels, and the distance is short. Transcaval access is a specialist technique done in experienced centres, and consent includes discussion of this access route.
When is it done?
It is planned. Before it, the team usually arranges:
CT angiography, including detailed planning of the crossing point
echo, ECG, blood tests and a group and save
a review of blood thinners, as per centre protocol
multidisciplinary planning, often including vascular surgery, with bail-out options agreed
Step by step
1. Anaesthetic and access
Done under general anaesthetic or sedation. Sheaths are placed in the femoral vein and the opposite femoral artery (for angiography and monitoring) under ultrasound, and a temporary pacing wire is placed. Sizes are per device and operator.
2. Crossing from the IVC into the aorta
A catheter in the aorta holds a snare (a wire loop) as a target at the planned level.
From the IVC, a guide catheter aims at the snare. Biplane or two-angle X-ray is used to line them up.
A thin wire inside an insulated microcatheter is connected to an electrosurgery pen; a brief burst of energy, per operator settings, lets it cross the IVC and aortic walls.
The wire is caught by the snare in the aorta, and a microcatheter is advanced across. Heparin is given, dose as per centre protocol.
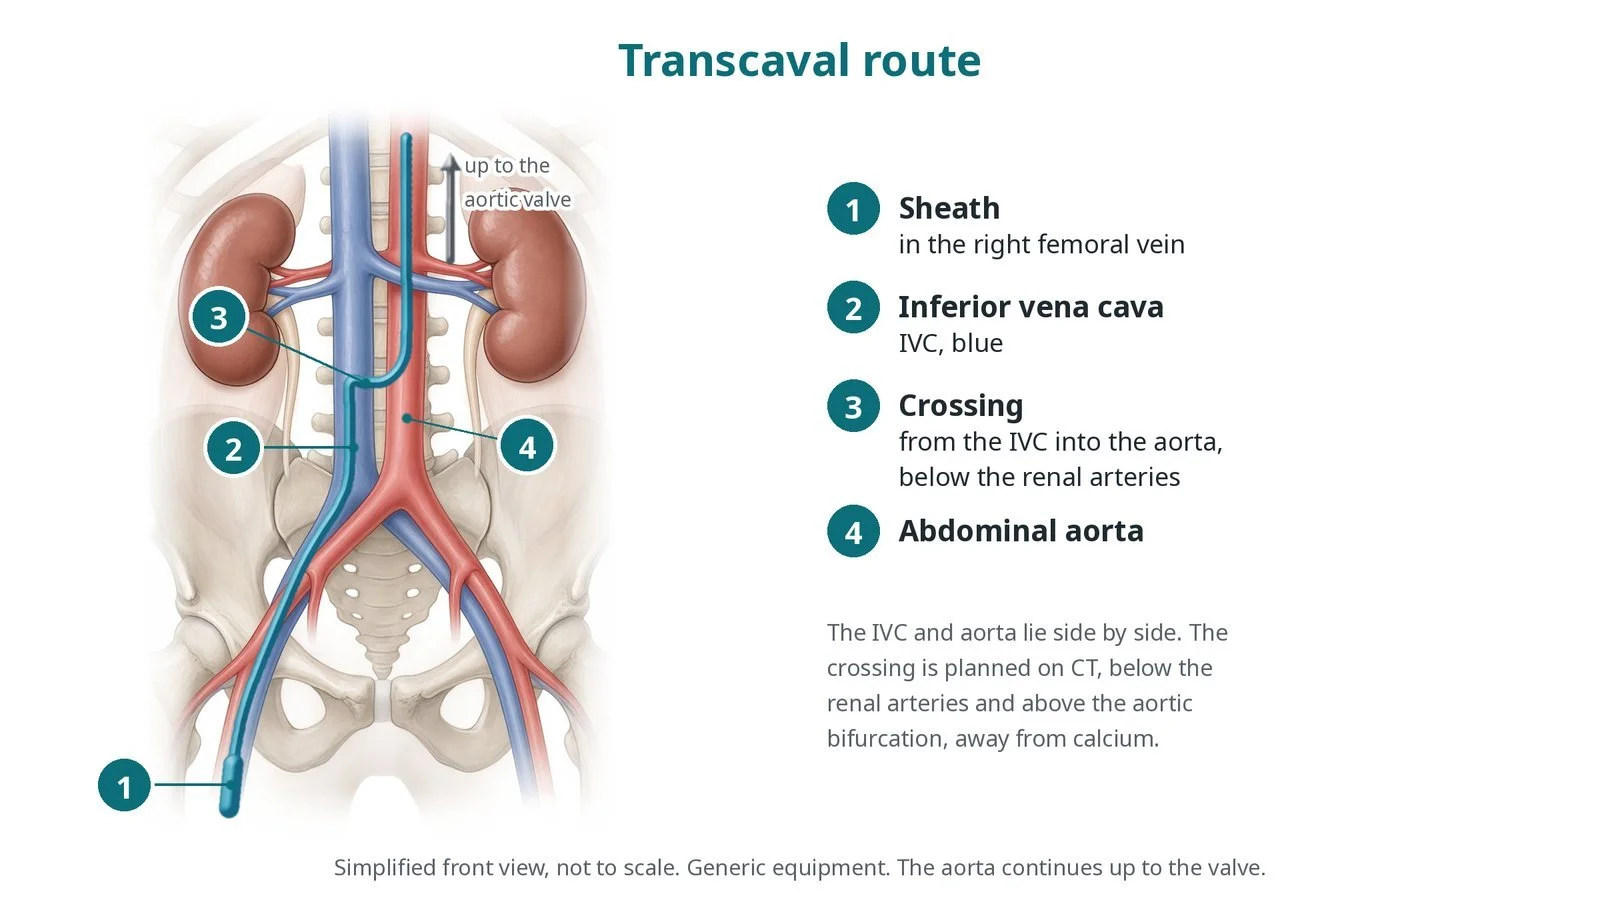
Route, front view: (1) sheath in the right femoral vein; (2) inferior vena cava; (3) crossing from the IVC into the aorta, below the renal arteries; (4) abdominal aorta. The aorta then continues up to the valve.
3. Sheath and valve
A. Stiff wire. The thin wire is exchanged for a stiff wire in the aorta.
B. Sheath. The TAVI sheath is passed up the IVC and across into the aorta.
C. Valve. The aortic valve is crossed, a stiff wire placed in the LV, and the valve deployed as in transfemoral TAVI.
D. Close. The sheath is pulled back into the IVC and an occluder plug is placed across the passage: one disc inside the aorta, the waist in the passage and the other disc in the IVC.
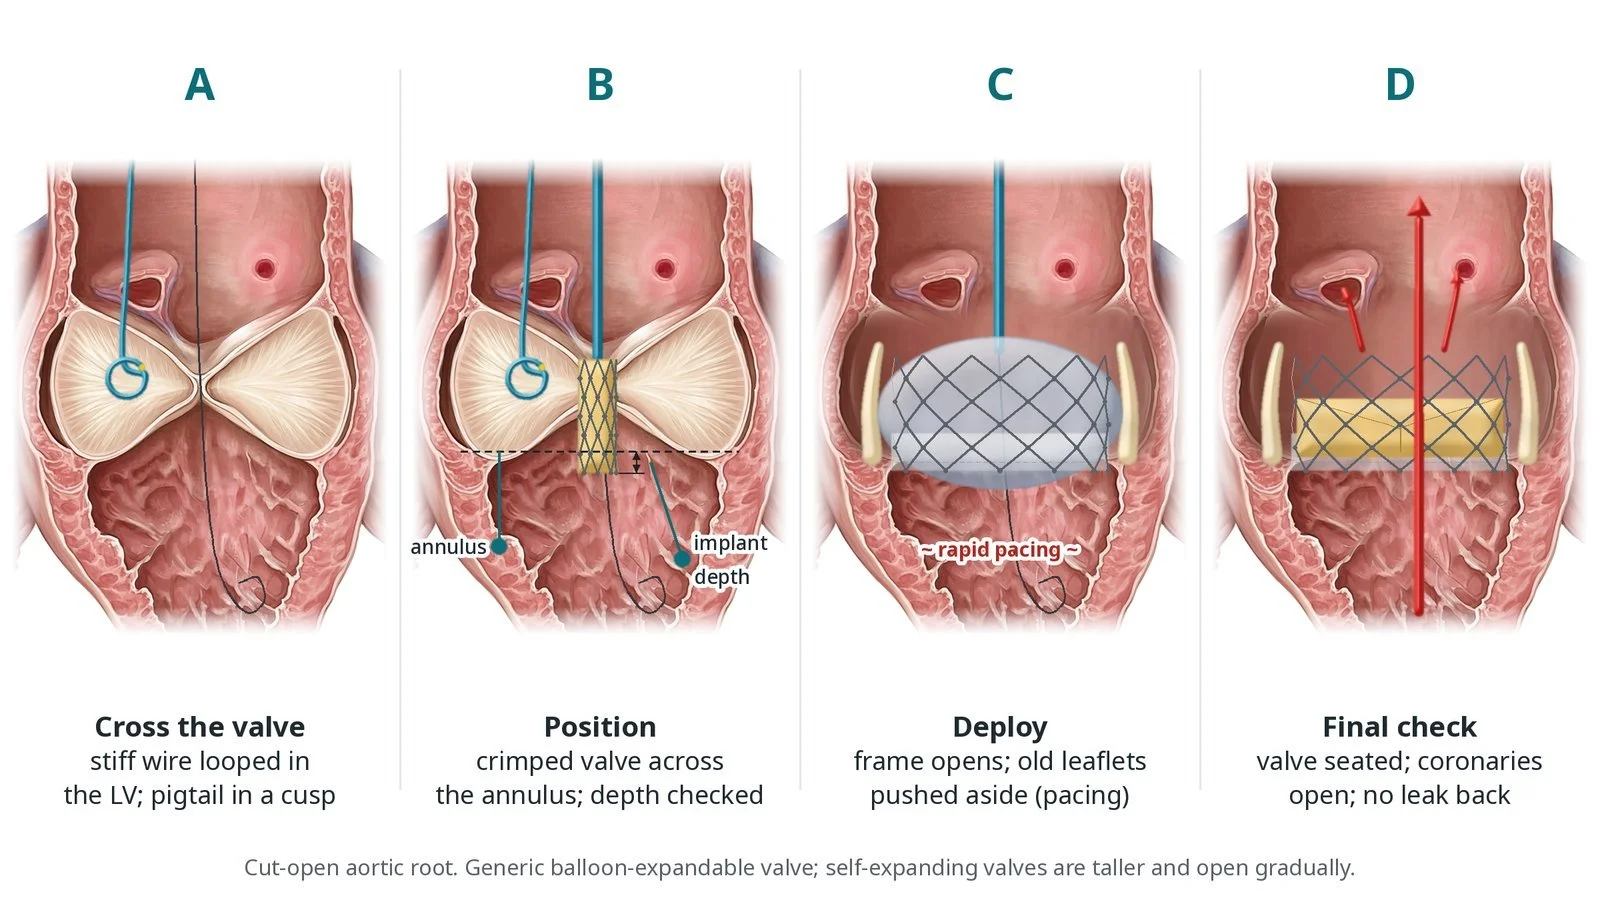
A: a stiff wire is looped in the LV and a pigtail sits in a cusp. B: the crimped valve is positioned across the annulus at the planned depth. C: the frame opens and the old leaflets are pushed aside, with pacing. D: the valve is seated, the coronaries are open and there is no leak back. The deployment steps are the same for every access route.
4. Checking the closure
An aortogram checks the plug. A small leak from the aorta into the IVC is common at first and often closes over time. Bail-out options (such as a balloon to block the aorta, or a covered stent graft) are kept ready.
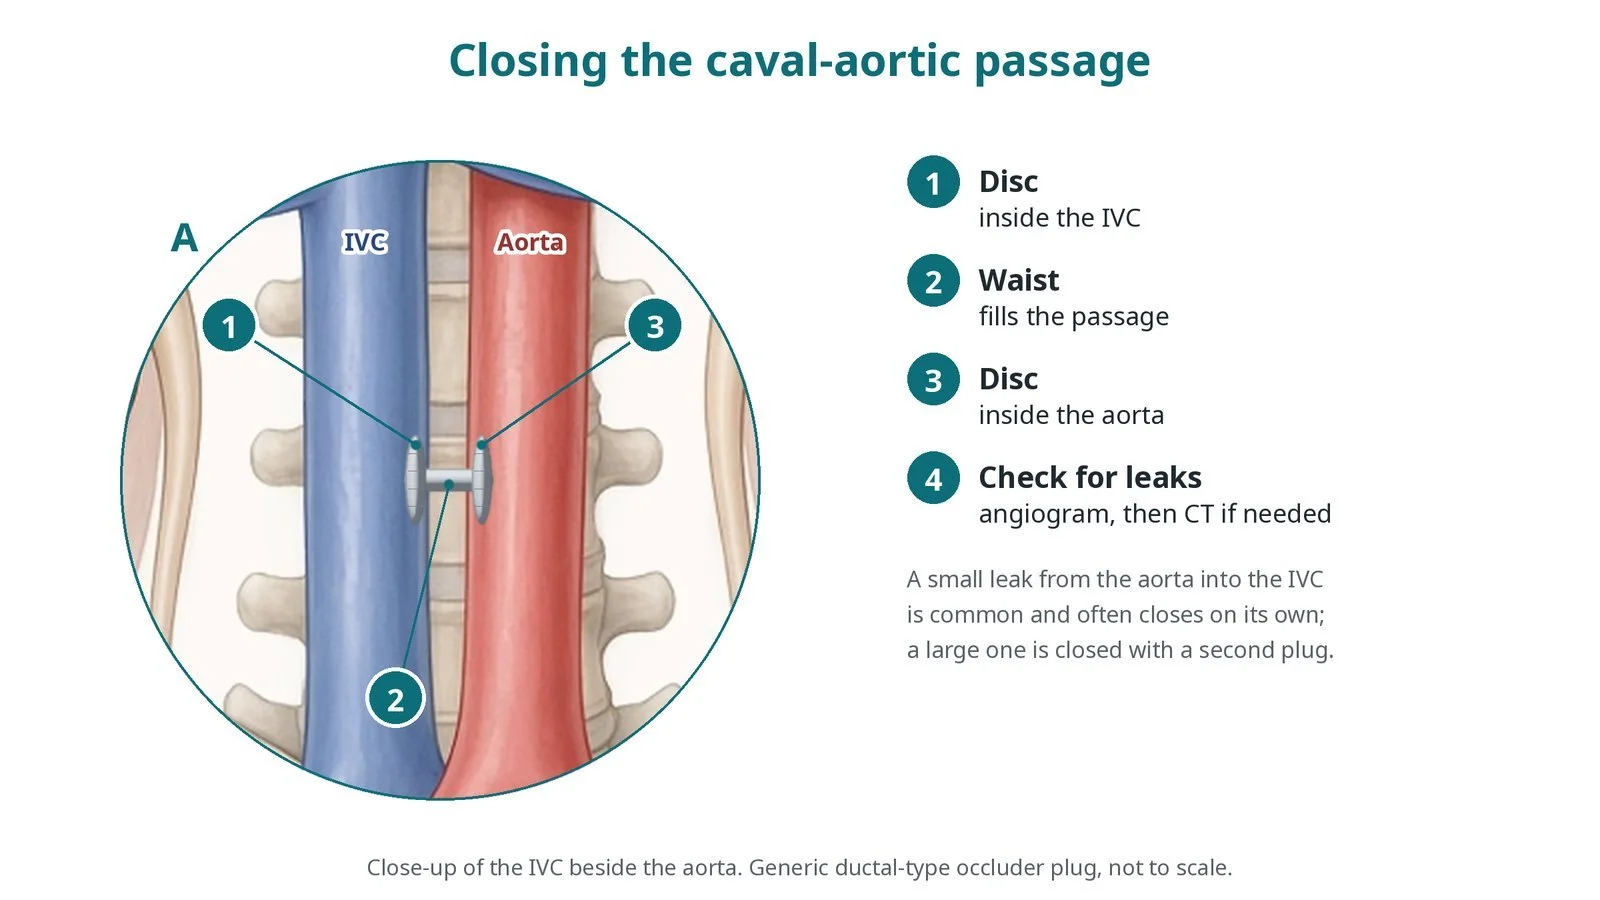
Closure: an occluder plug with one disc in the IVC (1), its waist in the passage (2) and one disc in the aorta (3). Leaks are checked by angiogram, then CT if needed.
Recovery and aftercare
First hours: recovery, often in a coronary care, high-dependency or intensive care area, with checks of the groins, blood count (haemoglobin), abdomen, heart rhythm and blood pressure, as per centre protocol.
Echo and blood tests: before discharge.
Heart rhythm: some people develop heart block and need a permanent pacemaker.
Going home: often after 1 to 3 nights, sometimes longer after alternative access.
Scans: a CT may be done after the procedure to check the plug and the passage.
Activity: avoid heavy lifting for a few weeks, or as advised.
Medicines: antiplatelet or anticoagulant medicines, as per your team's plan.
Driving: DVLA guidance after a percutaneous valve procedure for a car licence is not to drive for 2 weeks; bus and lorry drivers must tell the DVLA. Ask your team.
Call 999 if you have chest pain, sudden breathlessness, fainting, signs of a stroke, or bleeding or swelling at the access site.
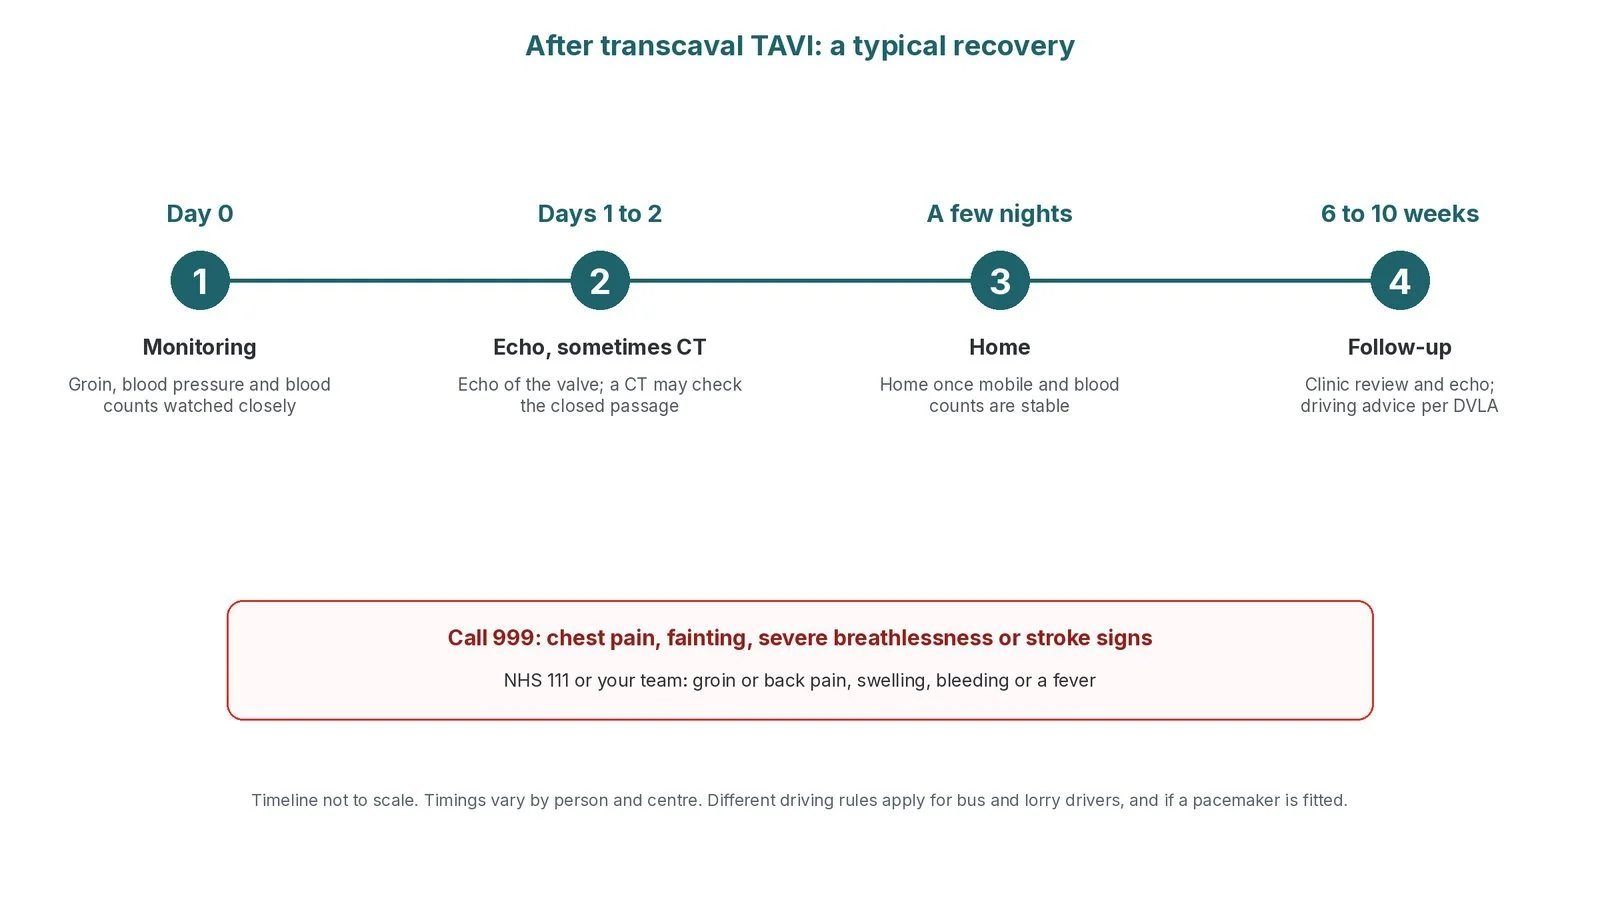
After transcaval TAVI: (1) monitoring and blood counts; (2) echo, sometimes CT; (3) home after a few nights; (4) follow-up at 6 to 10 weeks.
Risks and complications
Your team will discuss your own risks. Possible problems include:
bleeding into the back of the abdomen (retroperitoneal bleeding), sometimes needing a stent graft or transfusion
a persistent connection between the aorta and IVC (aorto-caval fistula)
the plug moving or sitting in the wrong position
breakdown of red blood cells (haemolysis)
injury to bowel or other structures (rare)
stroke
bleeding or injury to the access artery or vein
heart block needing a permanent pacemaker
a leak around the new valve
kidney strain from contrast dye
rarely, blockage of a coronary artery, damage to the aortic root, or the valve moving
Cath lab kit list (printable)
Barts example kit list
An example from one UK centre, written generically. Every lab has its own protocol, and sizes and doses vary.
Crossing
venous guide catheter (long, curved shape per operator); arterial guide catheter
stiff-tipped 0.014" crossing wire, per operator
wire converter or insulated microcatheter, and a braided 0.035" microcatheter, per operator
snare (large loop) with haemostasis valve
extra-stiff exchange wire, per operator
electrosurgery pen and generator, settings per operator
Closure
buddy 0.014" wire, per operator
occluder plugs (ductal-type), sizes per device and operator, with delivery system
steerable sheath, per operator
Bail-out
large compliant balloon for aortic occlusion, with a suitable sheath
covered stent grafts (aortic and iliac), per centre
usual TAVI kit; femoral sheaths of several sizes
Procedural steps (Barts example)
Femoral arterial and venous access; pacing wire
Snare positioned in the aorta at the planned level; venous guide aimed at it from the IVC
Crossing wire energised with the electrosurgery pen while advancing; wire snared in the aorta
Microcatheter across; exchange to extra-stiff wire; heparin
TAVI sheath up the IVC into the aorta; usual TAVI steps
Sheath back into the IVC; occluder plug placed across the passage under biplane views with an arterial pigtail
Aortogram; haemostasis; monitoring
First time in the cath lab?
💡 First-time tip
Know the bail-out. Find the aortic occlusion balloon and covered stents before the case starts. Diathermy safety. The pen is activated only when the operator says so; check the return pad and settings beforehand. Biplane matters. Lining up the snare and guide in two views is key; expect C-arm moves. Watch the haemoglobin. A falling blood count or pressure after the case can mean bleeding. Plug ready. Have the occluder sizes and delivery system ready before the sheath comes out.
FAQ
Is it safe to make a hole between the vein and the aorta?
It is a planned, controlled passage that is closed at the end with a plug. There are specific risks, including bleeding, which your team will discuss.
Why not use the groin artery?
Because it is too small or diseased for the delivery system, as shown on CT.
Will the plug stay in forever?
Yes. It is designed to stay in place.
How long will I stay in hospital?
Often a few nights.
Related Cath Lab 101 guides
Sources
All checked on 10 October 2026. Each page's own date is shown where it gives one.
NICE. Heart valve disease presenting in adults: investigation and management (NG208). nice.org.uk/guidance/ng208
NICE. Transcatheter aortic valve implantation for aortic stenosis (HTG446). nice.org.uk/guidance/htg446 (published 26 Jul 2017)
Vahanian A, et al. 2021 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J 2022;43(7):561–632. PubMed 34453165
British Heart Foundation. TAVI. bhf.org.uk
NHS. Aortic valve replacement. nhs.uk
DVLA / GOV.UK. Cardiovascular disorders: assessing fitness to drive (percutaneous valve intervention). gov.uk
Disclaimer
Education only. This page is for general education for healthcare students, cath lab staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, heart team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a heart emergency, call 999.
Disclosure: I work for a company that makes a device used in this procedure. This page is independent education, isn't sponsored or reviewed by any company, and doesn't recommend any product.
All diagrams on this page are original illustrations created for rodnieoro.com.