Transcatheter mitral valve implantation (TMVI, valve-in-valve): a Cath Lab 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
TMVI in one minute
What it is: some people have had their mitral valve replaced with a tissue (bioprosthetic) valve or repaired with a ring. These can wear out. Transcatheter mitral valve implantation (TMVI) places a new balloon-expandable valve inside the old one (valve-in-valve) or inside the ring (valve-in-ring), usually passed up a vein from the groin and across the wall between the atria.
Who it is for: people whose surgical mitral valve or repair has failed and who are at high risk from repeat open-heart surgery, as decided by a heart team.
Main risks: bleeding, a blockage of the outflow from the left ventricle, the valve moving or leaking around its edge, stroke, and a hole left in the septum. Your team will explain your own risk.
Usually: under general anaesthetic with transoesophageal echo (TOE), about 1.5 to 3 hours, often home after a few nights.
On this page: What is TMVI? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in the lab? · FAQ
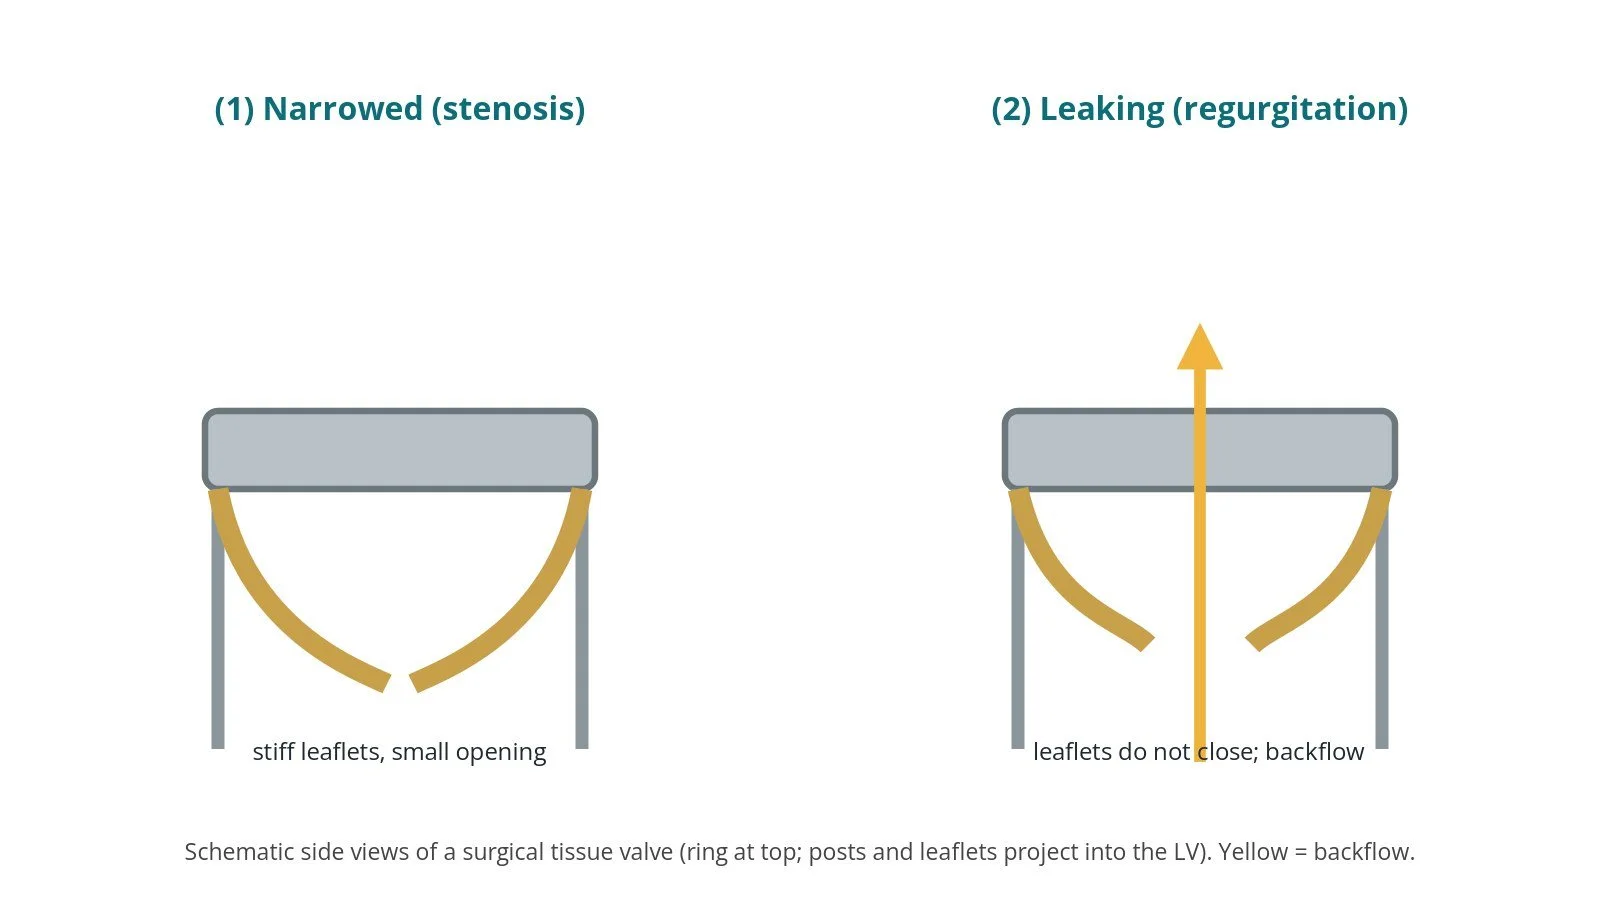
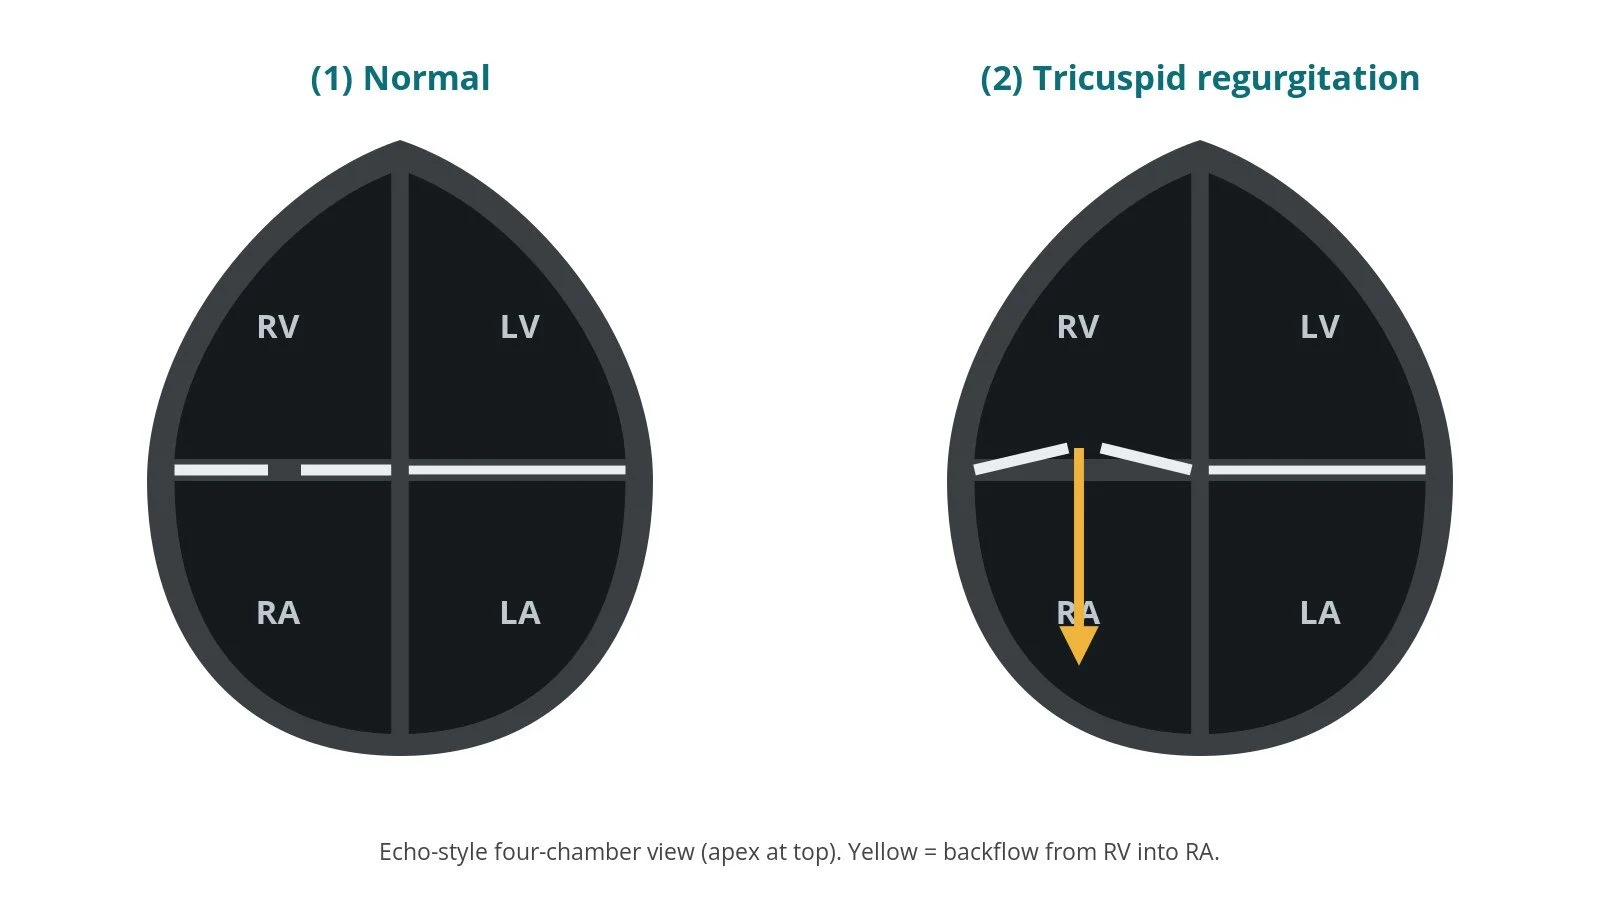
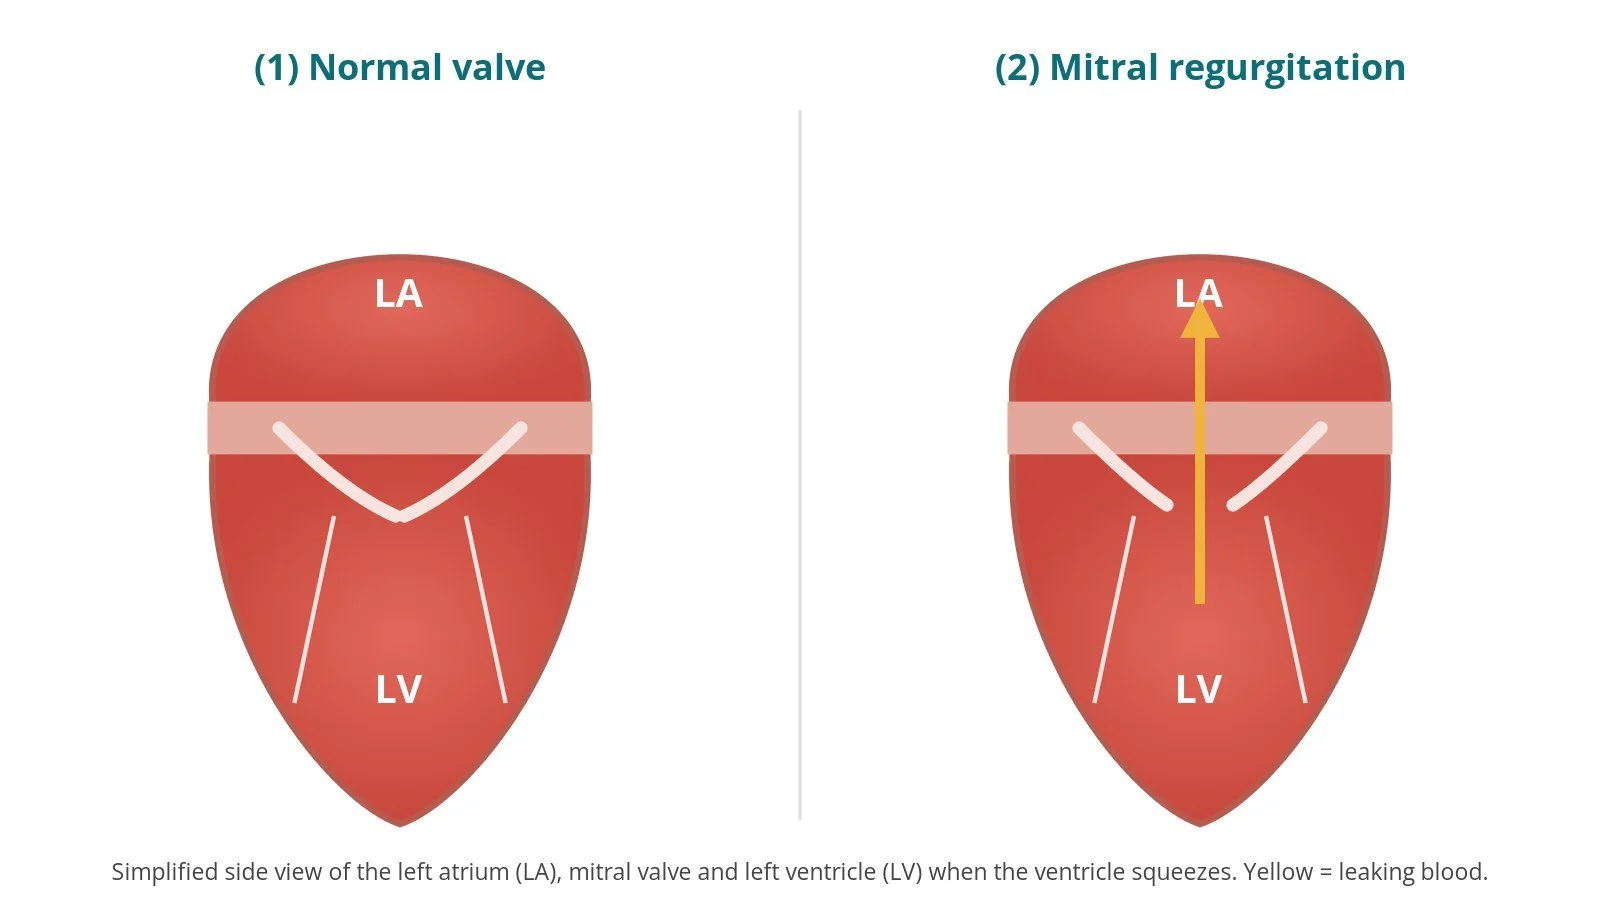
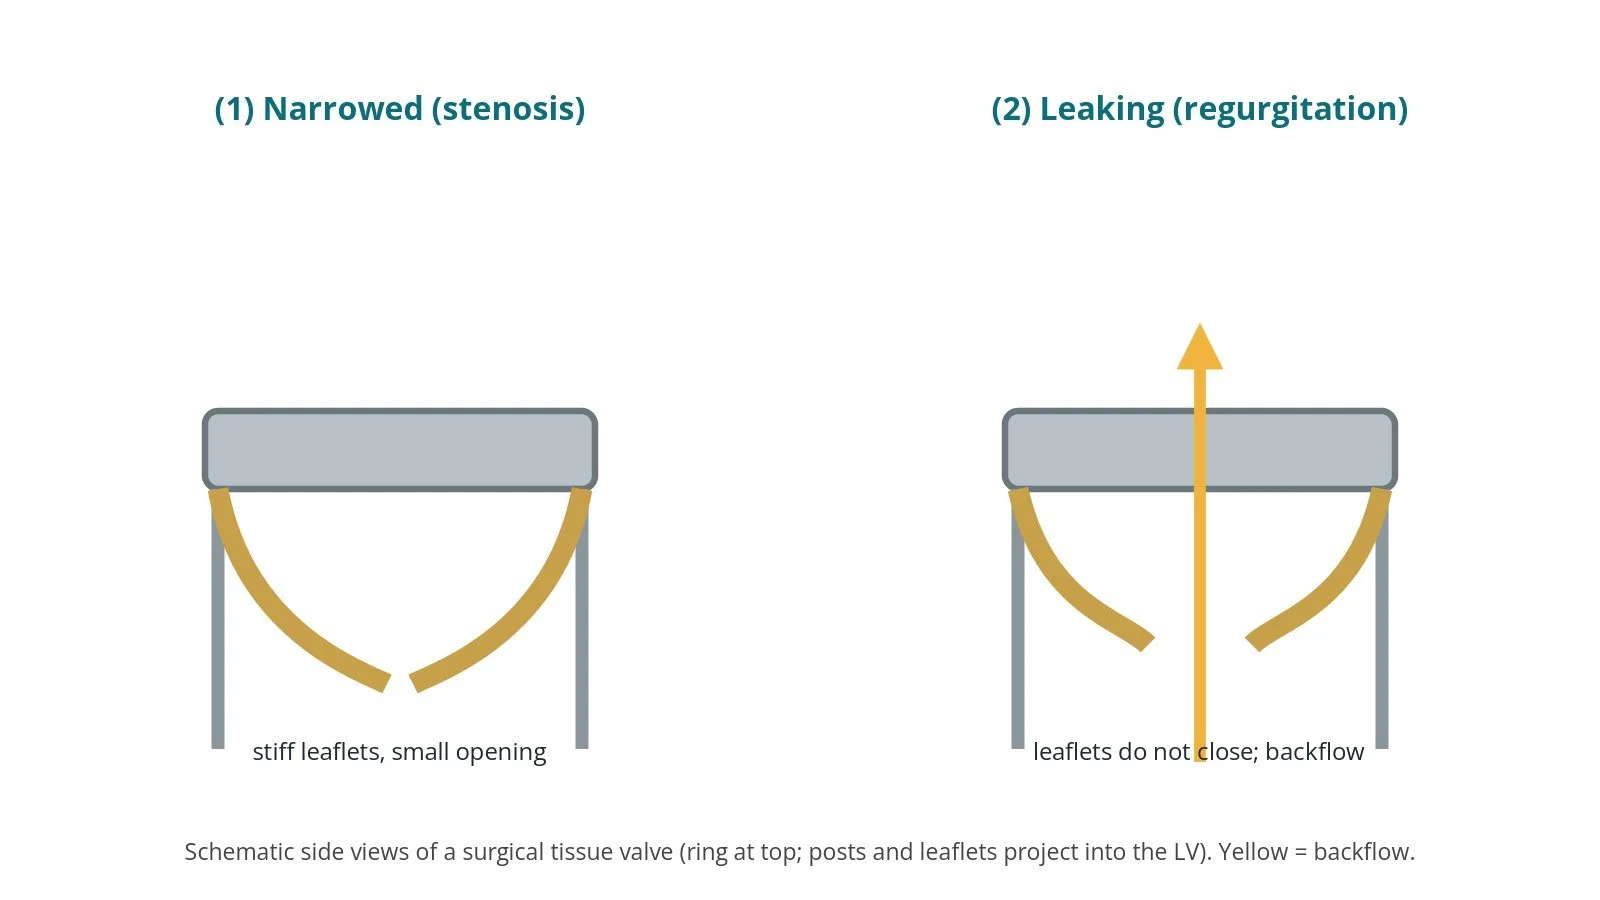
A surgical tissue valve can fail by (1) narrowing (stenosis) or (2) leaking (regurgitation).
What is TMVI?
When the mitral valve is replaced in open-heart surgery, many people receive a tissue (bioprosthetic) valve, which has a frame and a sewing ring stitched into the heart. Others have their own valve repaired and an annuloplasty ring sewn around it. Over years, tissue valves can degenerate: they become stiff and narrowed (stenosis), leaky (regurgitation), or both. Repairs can fail too.
Repeat open-heart surgery carries higher risks for some people. Transcatheter mitral valve implantation (TMVI) offers another option:
valve-in-valve (ViV): a new valve is expanded inside the old surgical valve, using its frame as an anchor
valve-in-ring (ViR): a new valve is expanded inside the surgical ring
The new valve is usually a balloon-expandable transcatheter valve, the same type of design used in TAVI. It is mounted on its delivery balloon the opposite way round to a TAVI valve, because blood flows from the left atrium down into the left ventricle.
TMVI in a person's own (native) valve, without a previous surgical valve or ring, uses different, dedicated devices and is not covered here.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
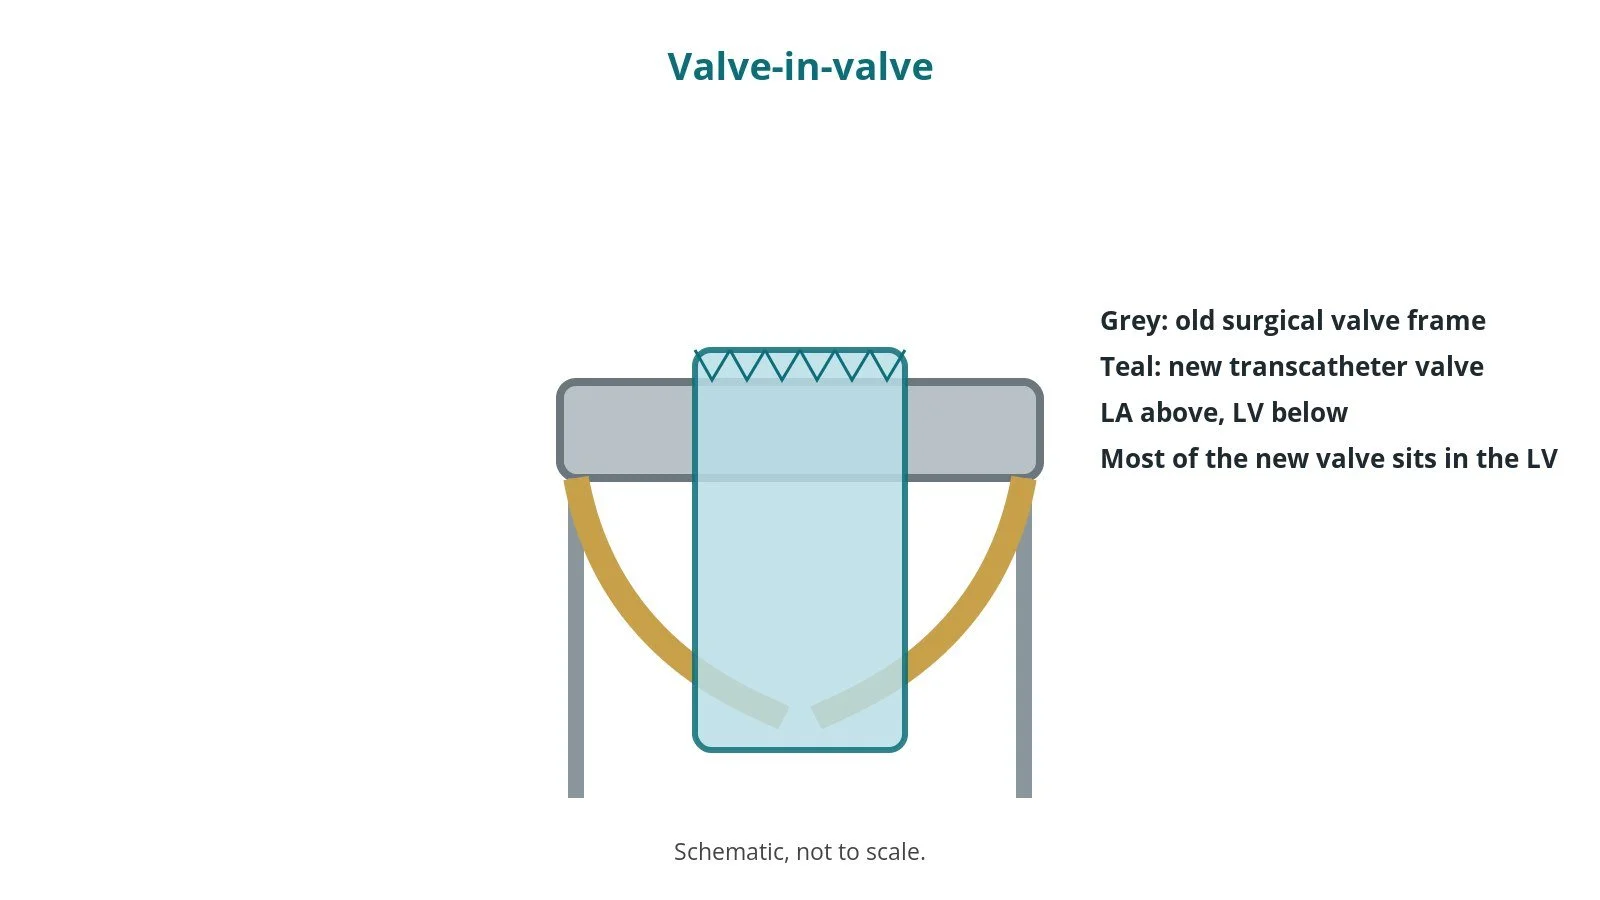
Valve-in-valve: the new valve (teal) is expanded inside the old surgical valve frame (grey), which anchors it.
Who is it for?
The ESC/EACTS valvular heart disease guidelines include transcatheter valve-in-valve as an option for selected people with a failed mitral bioprosthesis who are at high surgical risk, decided by a heart team. NICE guidance on mitral valve-in-valve (HTG592) and valve-in-ring (HTG593) implantation covers the transapical route (through a small cut in the chest wall) and recommends special arrangements; most centres now use the transseptal route described here where possible.
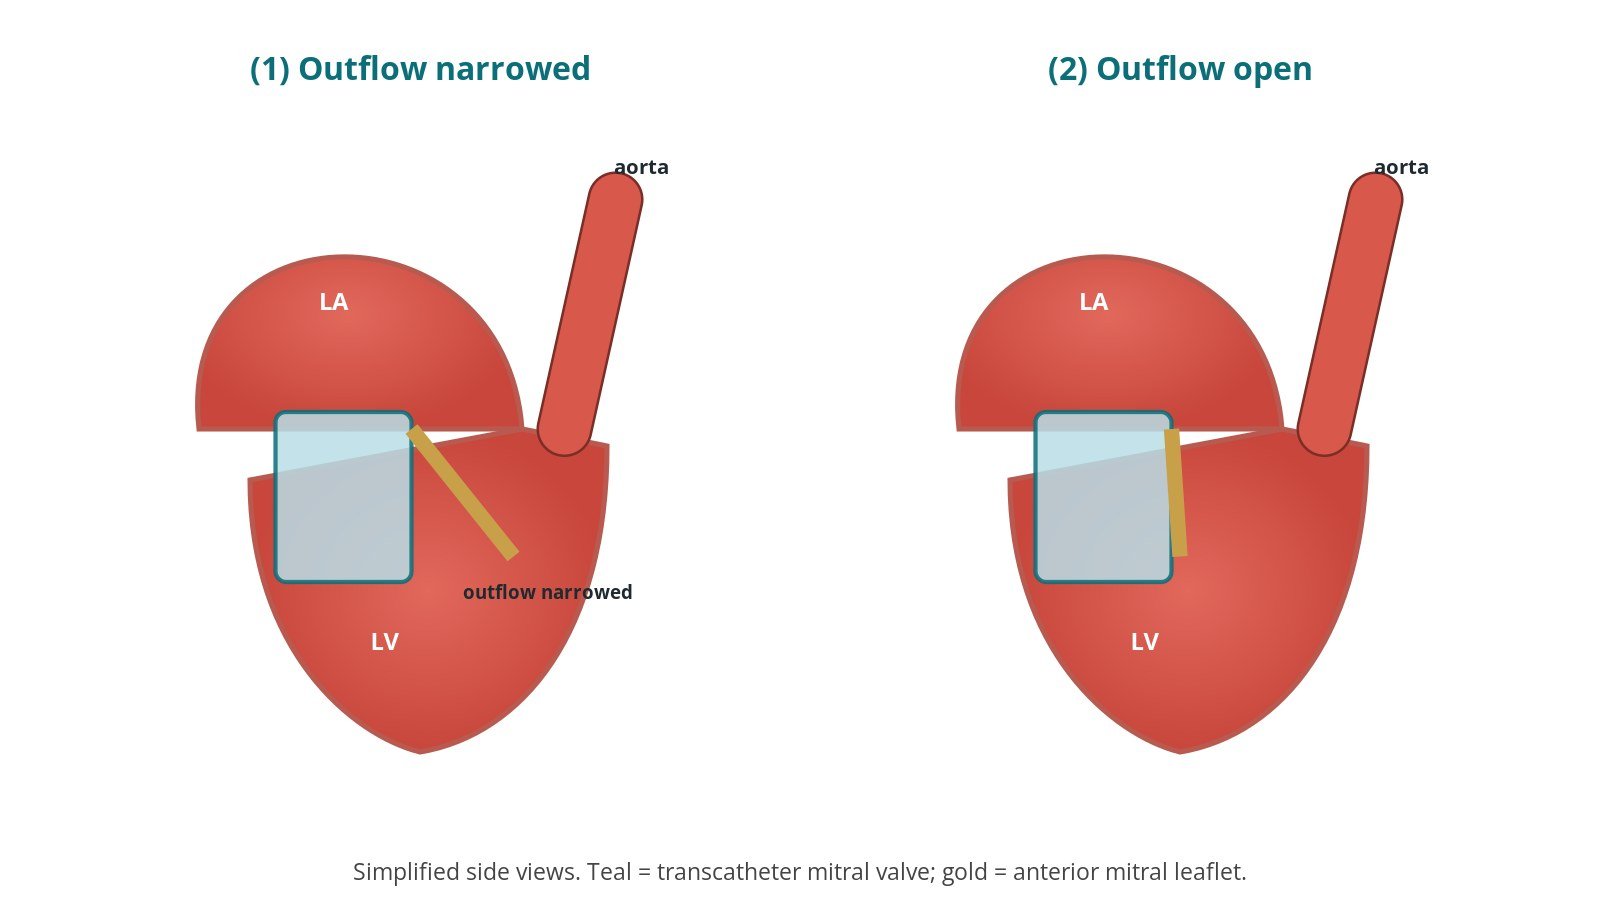
The team uses CT to measure the old valve or ring and to predict whether the new valve could block the outflow from the left ventricle (LVOT obstruction). If the risk is high, an extra step (such as LAMPOON, which splits the front leaflet) or a different plan may be needed.
When is it done?
It is usually planned. Before it, the team usually arranges:
echo and TOE to confirm how the valve has failed
CT to size the valve and assess LVOT risk and access
blood tests, including a group and save
a review of blood thinners, as per centre protocol
Step by step
1. Anaesthetic and set-up
TMVI is done in a cath lab or hybrid theatre under general anaesthetic with TOE. Sheaths are placed in the femoral veins (and often a femoral artery for pressure monitoring), under ultrasound. A temporary pacing wire is placed in the right ventricle for rapid pacing during deployment. A large sheath goes in the right femoral vein, often after a suture-based closure device is placed in advance. Sizes are per device and operator.
2. Transseptal puncture
The atrial septum is crossed under TOE and X-ray guidance, usually in a high and posterior position so the delivery system can bend down to the mitral valve. Heparin is given, dose as per centre protocol.
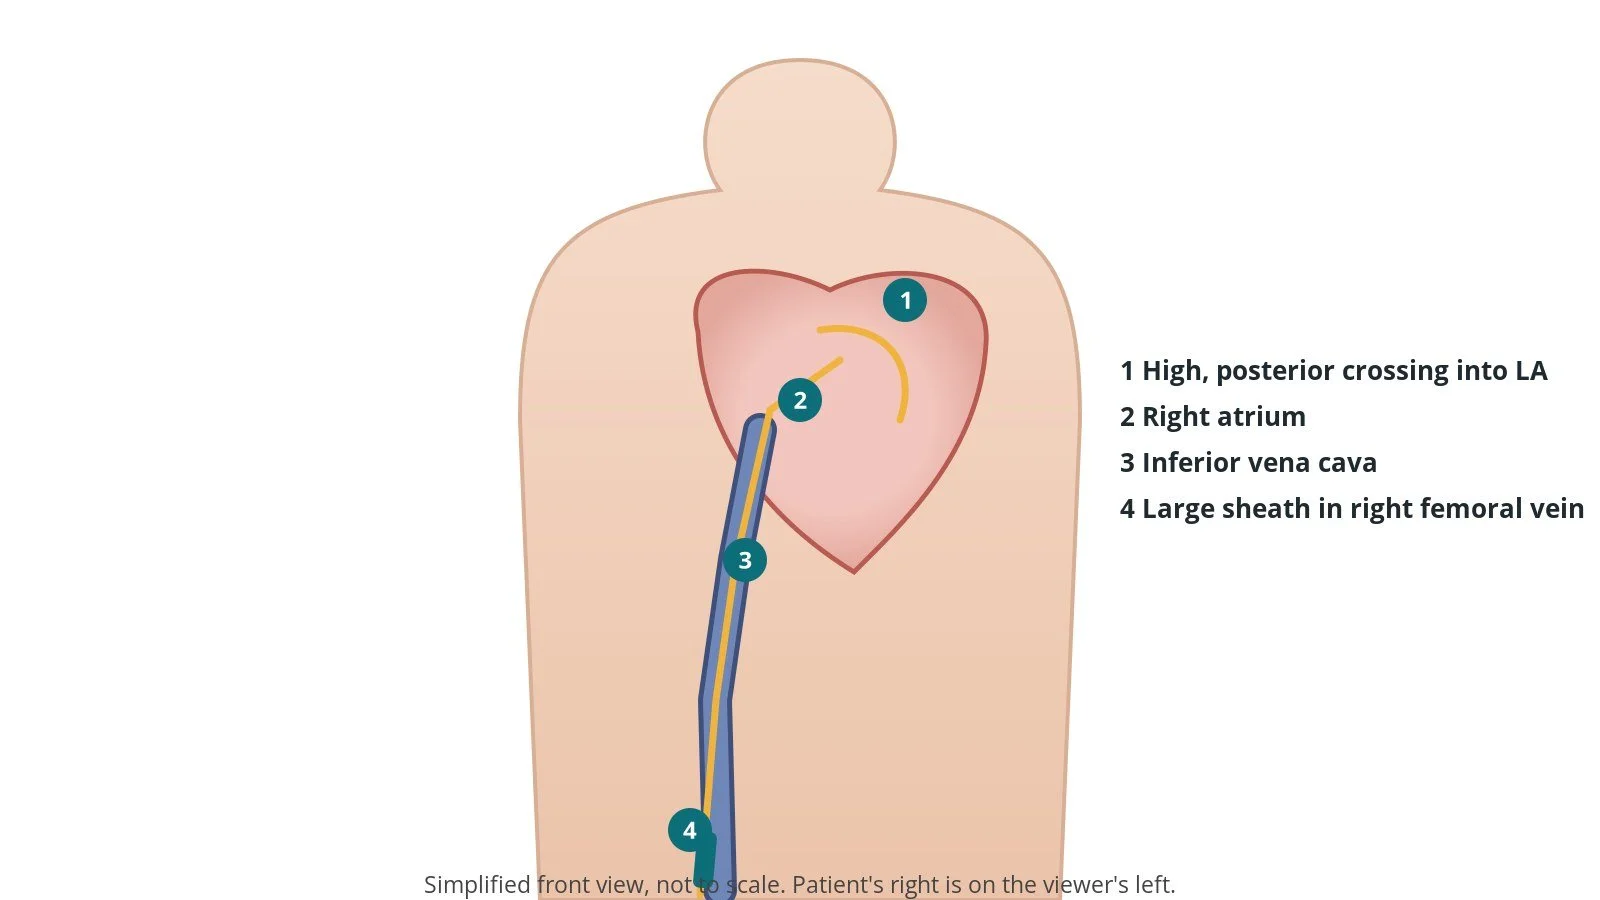
Access: (1) high, posterior crossing into the left atrium; (2) right atrium; (3) inferior vena cava; (4) large sheath in the right femoral vein.
3. Implanting the valve
A. Cross and wire. A steerable catheter is aimed at the mitral valve. A catheter crosses the old valve into the left ventricle, and a stiff pre-shaped wire is placed at the LV apex. A stable wire is essential.
B. Open the septum. The septum is stretched with a balloon (balloon atrial septostomy) so the delivery system can cross, per device and operator.
C. Position. The valve, mounted the opposite way round to a TAVI valve, is advanced across the septum and into the old valve, aligned with its frame on X-ray and TOE. Most of the new valve sits on the ventricular side, per device instructions.
D. Deploy. Under rapid ventricular pacing, the balloon is slowly inflated to expand the valve inside the old frame. TOE and pressure checks confirm position, function and any leak.
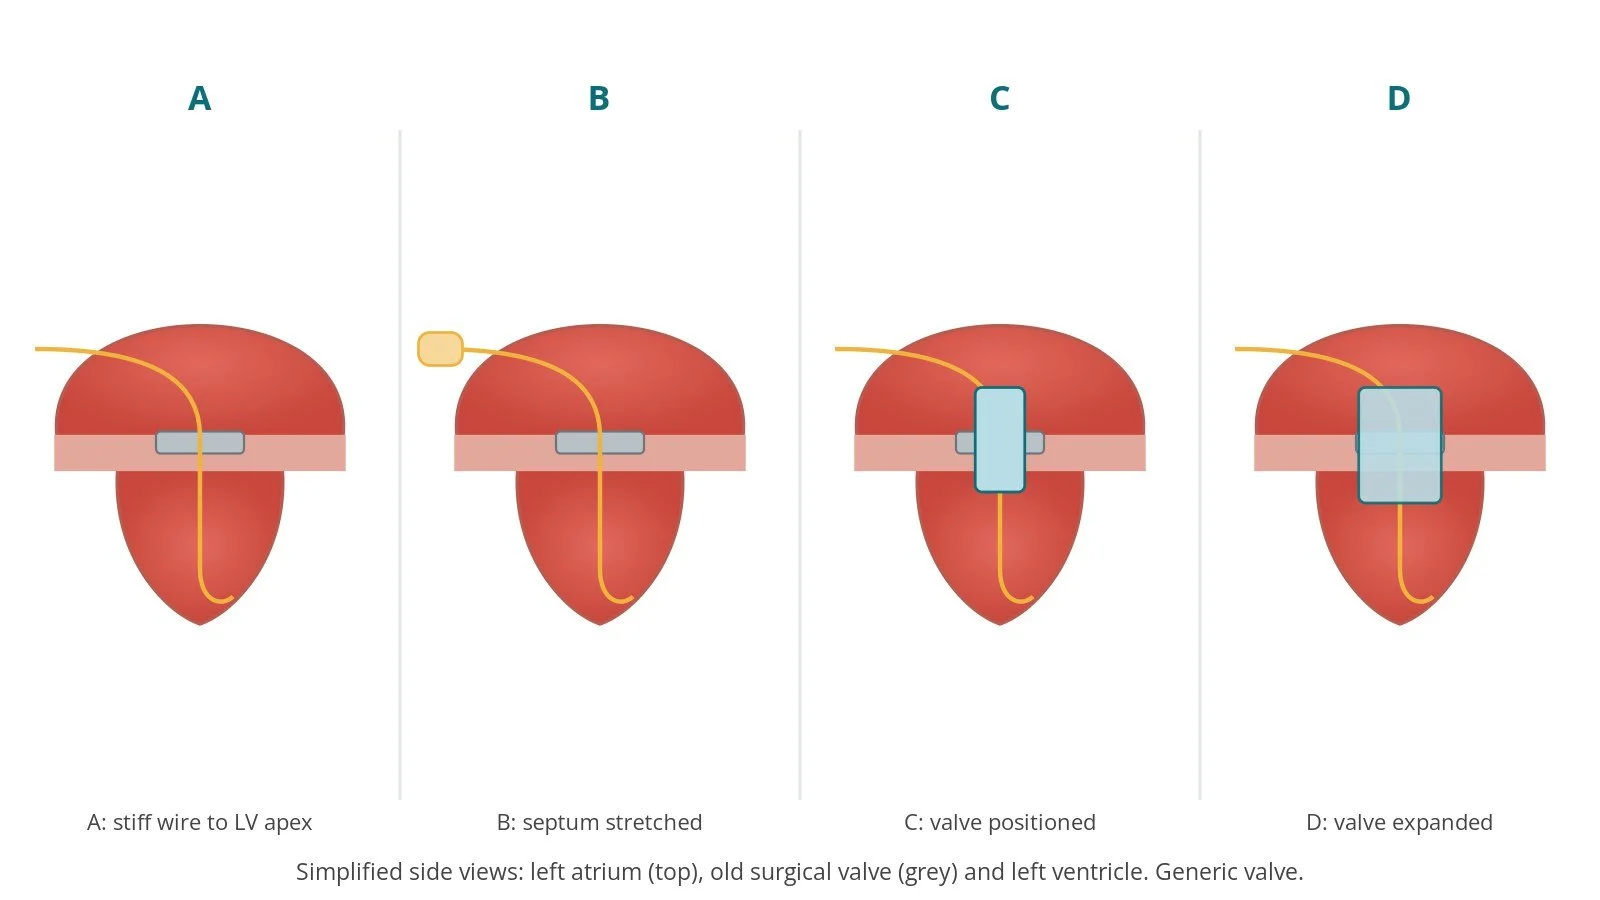
A: wire to the LV apex. B: septum stretched. C: valve positioned. D: valve expanded under rapid pacing.
4. Finishing
The delivery system is removed. A catheter is used to withdraw the stiff wire without injuring the heart. The septum is checked on echo for a significant shunt. Sheaths are removed and the veins are closed with the pre-placed sutures or pressure, per operator. Heparin may be reversed, as per centre protocol.
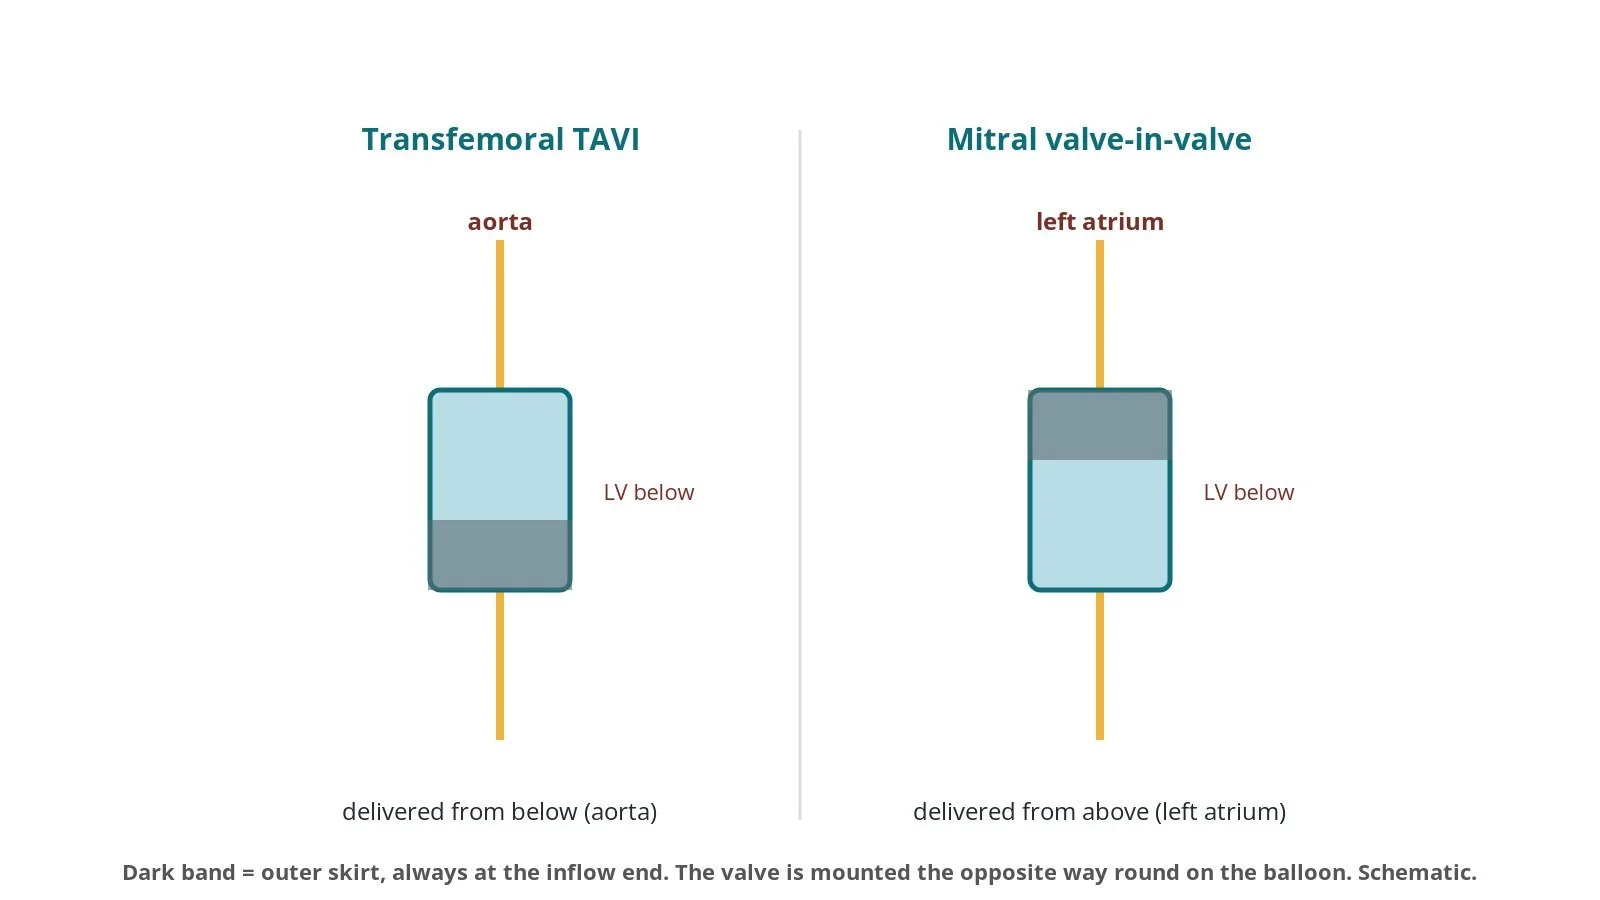
Orientation: the valve is mounted the opposite way round for mitral valve-in-valve compared with transfemoral TAVI.
Recovery and aftercare
First hours: recovery, often in a high-dependency area, with checks of the groins, heart rhythm and blood pressure, as per centre protocol.
Echo: before discharge to check the valve.
Going home: often after a few nights.
Medicines: a blood thinner (anticoagulant) is usually given for a time to reduce the risk of clots on the new valve, as per your team's plan.
Activity: avoid heavy lifting for about a week, or as advised.
Follow-up: clinic and echo checks.
Driving: DVLA guidance after a percutaneous valve procedure for a car licence is not to drive for 2 weeks; bus and lorry drivers must tell the DVLA. Ask your team.
Call 999 if you have chest pain, sudden breathlessness, fainting, signs of a stroke, or heavy groin bleeding.
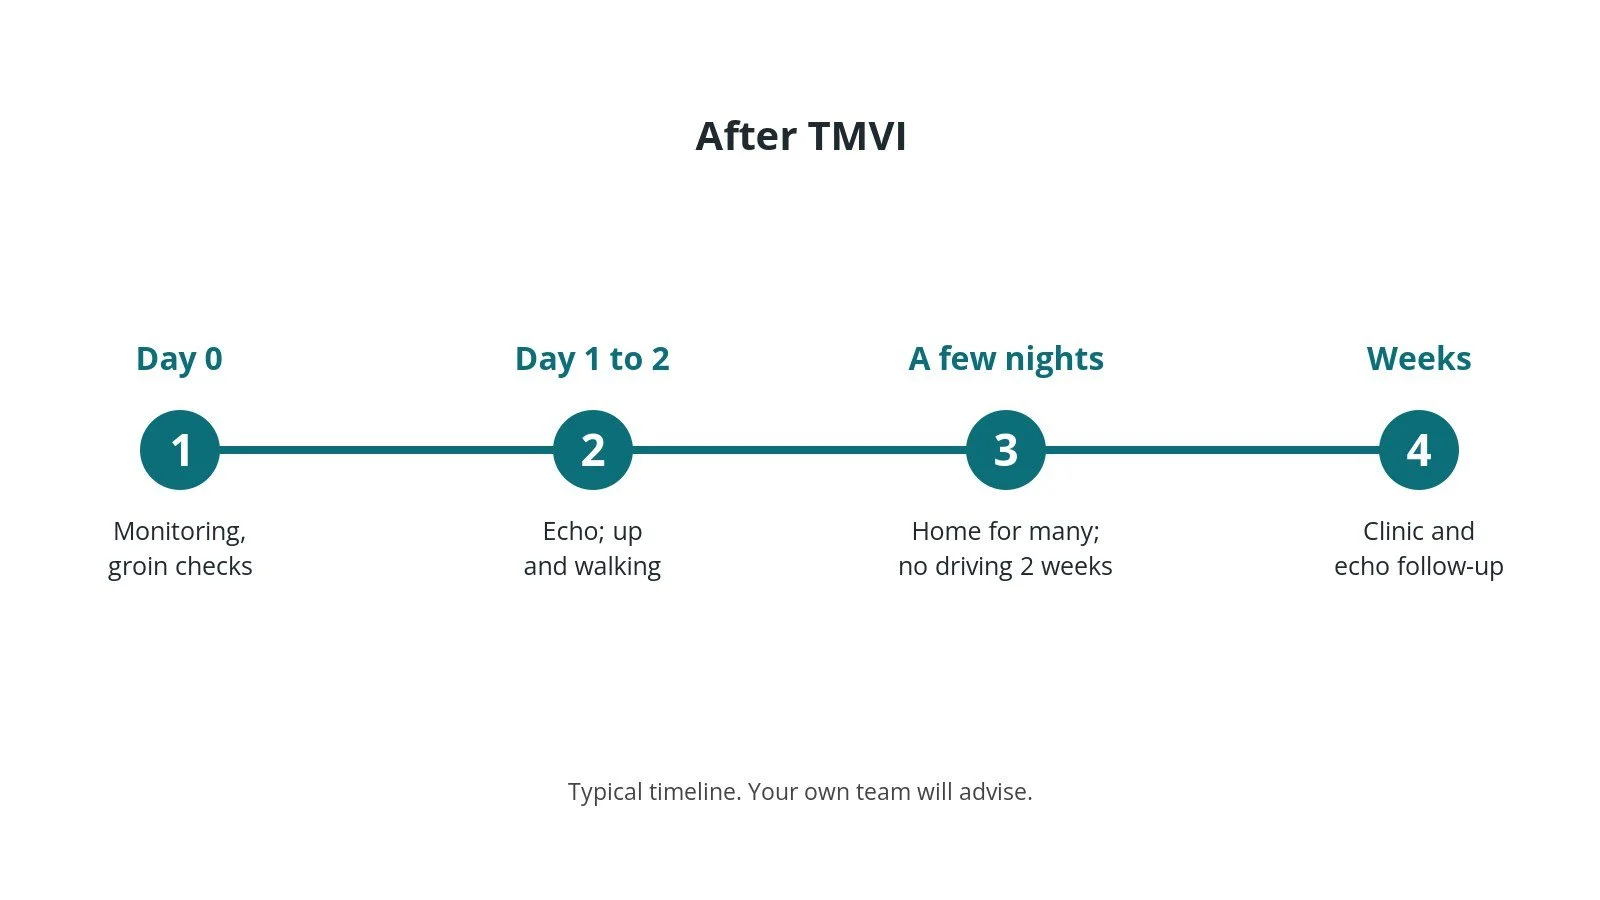
After TMVI: (1) monitoring; (2) echo; (3) home after a few nights for many; (4) follow-up and echo.
Risks and complications
Your team will discuss your own risks. Possible problems include:
bleeding or vein injury at the groin
LVOT obstruction, where the old valve leaflet or new valve blocks outflow from the left ventricle
the valve moving out of position (embolisation) or a leak around its edge
fluid around the heart (tamponade) or injury from the stiff wire
stroke
a remaining hole in the atrial septum
clot forming on the new valve (valve thrombosis)
heart rhythm problems
Cath lab kit list (printable)
Barts example kit list
An example from one UK centre, written generically. Every lab has its own protocol, and sizes and doses vary.
group and save sent
structural heart procedure pack
femoral arterial and venous sheaths; large-bore venous sheath (long), sizes per device and operator
suture-based vascular closure devices (two), per operator
diagnostic catheters (multipurpose and right coronary shapes), per operator
snare, per operator
long J-tip exchange wire; stiff pre-shaped LV wire, per operator
temporary pacing wire
transseptal crossing system (needle or radiofrequency wire, with transseptal sheath), per operator
steerable sheath, per operator
peripheral balloon for septostomy, size per device and operator
balloon-expandable transcatheter valve and delivery system, with crimping kit; contrast/saline inflation mix per device instructions
heparin and protamine, as per centre protocol
Procedural steps (Barts example)
General anaesthetic and TOE; femoral access; pacing wire to RV
Pre-close suture in the right femoral vein; large-bore sheath
High, posterior transseptal puncture; heparin as per centre protocol
Steerable catheter; cross the old valve; stiff wire to LV apex
Balloon septostomy
Valve crimped the opposite way round to TAVI (checked by two people); advanced across the septum
Aligned with the old valve frame; deployed with slow balloon inflation under rapid pacing
Assessment by TOE and pressures; wire withdrawn over a catheter
Sheaths out; sutures tied; heparin reversal as per centre protocol
First time in the cath lab?
💡 First-time tip
Orientation check. The valve is crimped the opposite way round to a TAVI valve. Two people check it before it goes in; a wrongly mounted valve is a serious error. Wire position matters. Keep an eye on the stiff wire in the LV apex throughout; it can move during exchanges. Know the old valve. Each surgical valve looks different on X-ray. Have its details and CT plan available. Pacing ready. Check the rapid pacing works before deployment. Watch the pressure. A falling blood pressure can mean tamponade or LVOT obstruction.
FAQ
Is this open-heart surgery?
No. It is done through veins in the groin, usually without opening the chest.
How long will the new valve last?
Transcatheter valves are tissue valves and can wear out over time. Your team will monitor it with echo.
Can this be done if I have a ring rather than a valve?
Sometimes. Valve-in-ring is possible for some rings, depending on their shape and size.
Will I need blood thinners?
Usually for at least a few months. Your team will advise on the type and duration.
Related Cath Lab 101 guides
Sources
All checked on 10 October 2026. Each page's own date is shown where it gives one.
NICE. Transapical transcatheter mitral valve-in-valve implantation for a failed surgically implanted mitral valve bioprosthesis (HTG592). nice.org.uk/guidance/htg592 (published 22 Sep 2021)
NICE. Transapical transcatheter mitral valve-in-ring implantation after failed annuloplasty for mitral valve repair (HTG593). nice.org.uk/guidance/htg593
NICE. Heart valve disease presenting in adults: investigation and management (NG208). nice.org.uk/guidance/ng208
Vahanian A, et al. 2021 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J 2022;43(7):561–632. PubMed 34453165
NHS. Heart valve disease. nhs.uk/conditions/heart-valve-disease
DVLA / GOV.UK. Cardiovascular disorders: assessing fitness to drive (percutaneous valve intervention). gov.uk
Disclaimer
Education only. This page is for general education for healthcare students, cath lab staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, heart team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a heart emergency, call 999.
Disclosure: I work for a company that makes a device used in this procedure. This page is independent education, isn't sponsored or reviewed by any company, and doesn't recommend any product.
All diagrams on this page are original illustrations created for rodnieoro.com.