Cystoscopy: an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Cystoscopy in one minute
What it is: a thin camera scope passed through the urethra to look inside the bladder, take biopsies or treat problems.
Who it is for: people with blood in the urine, recurrent infections, bladder symptoms, or follow-up after bladder cancer.
Main risks: burning when passing urine, blood in the urine, infection; rarely bladder injury.
Usually: flexible under local anaesthetic gel, or rigid under general or spinal anaesthetic; 5–30 minutes; usually same-day.
On this page: What is a cystoscopy? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
What is a cystoscopy?
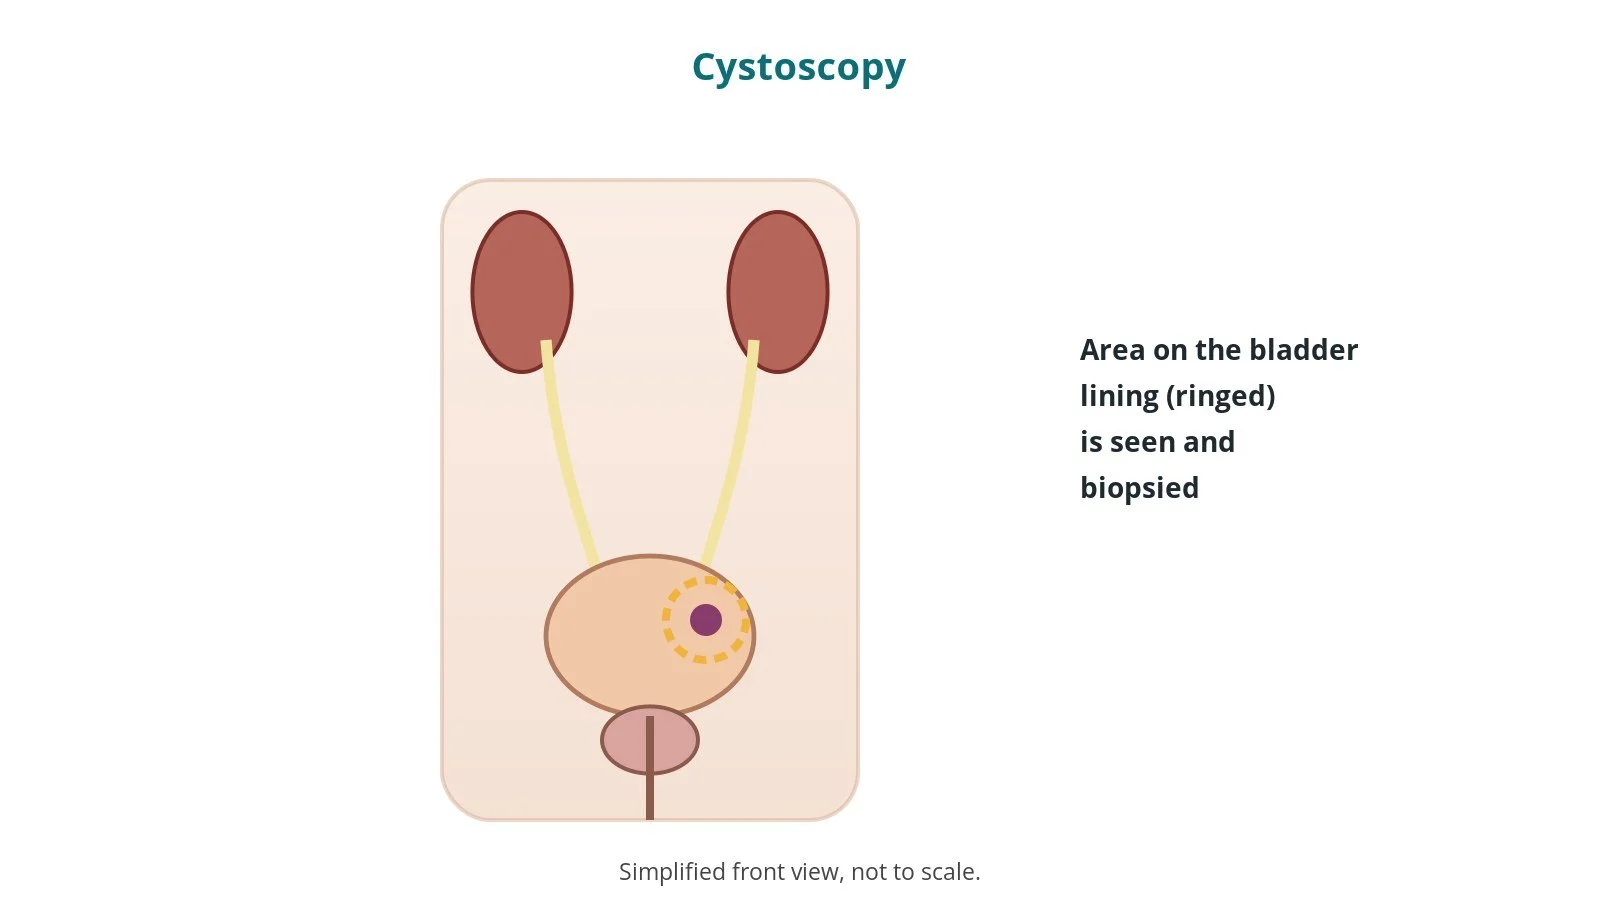
A cystoscopy lets the team see the inside of the bladder and urethra.
- Flexible cystoscopy: a thin bendy scope, usually in clinic with local anaesthetic gel.
- Rigid cystoscopy: a straight scope in theatre under general or spinal anaesthetic, allowing biopsies, removal of small growths, stent placement or removal, and other treatments.
Sterile fluid fills the bladder so the lining can be seen. Biopsies are sent to the lab.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- blood in the urine
- recurrent urine infections or bladder symptoms
- checks after bladder cancer
- stent removal or placement
The decision is made by your urology team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
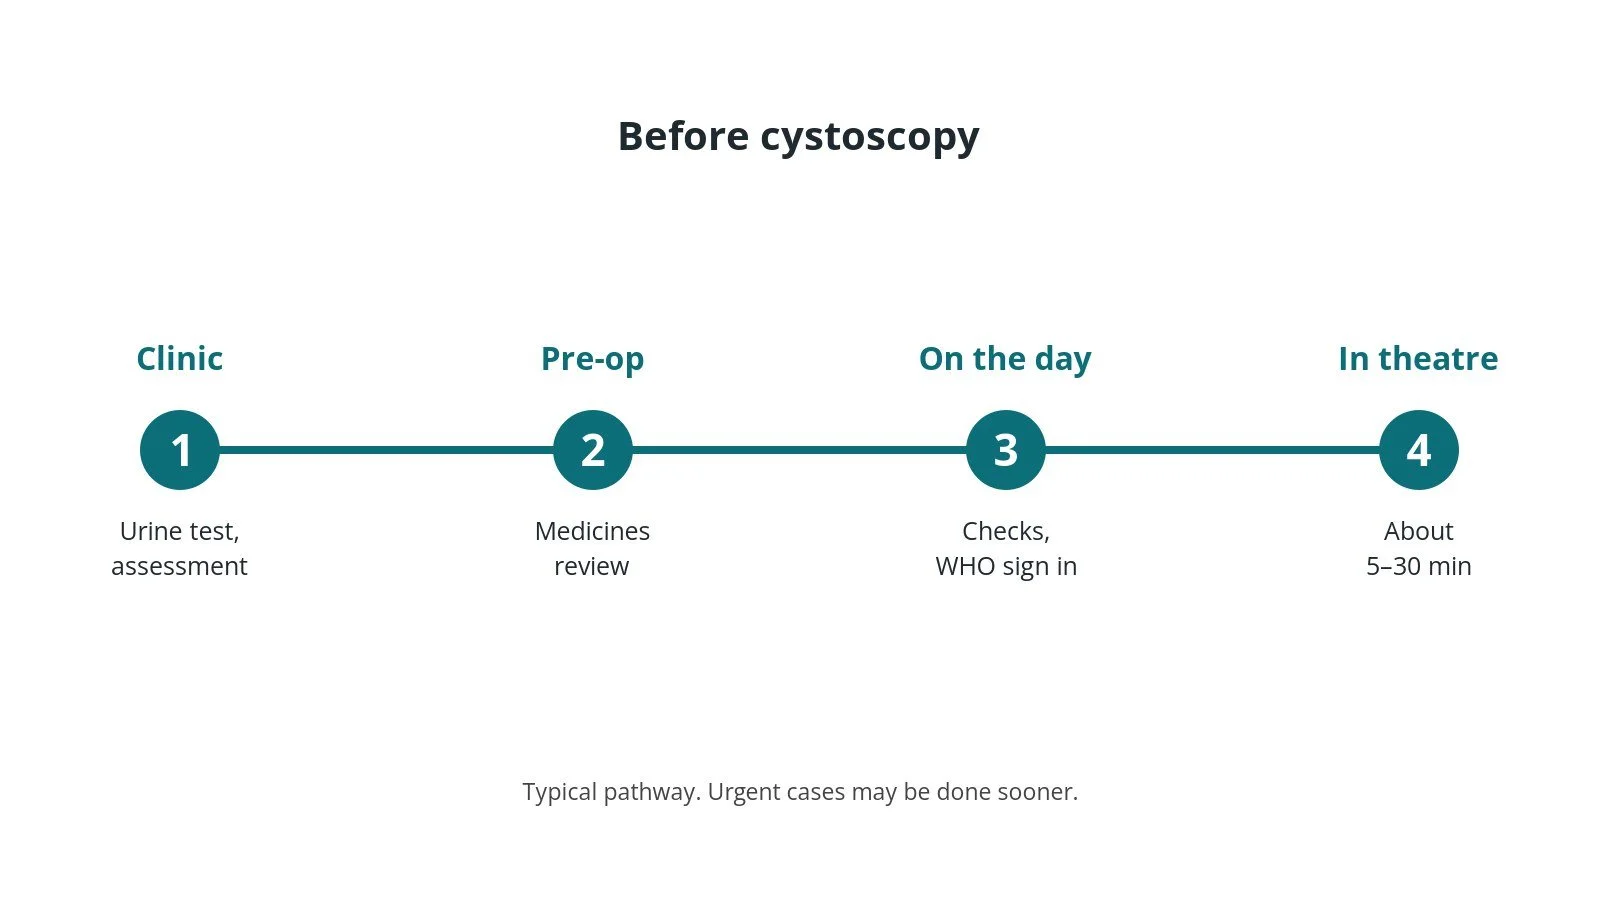
Most operations are planned; some are urgent. Before it, you usually have:
- a urine test, with infection treated first
- sometimes a scan
- a review of medicines, especially blood thinners if biopsy is planned, as per centre protocol
- a chance to ask questions and give consent
Step by step
1. Getting ready
Team brief and WHO checklist first, including the side and site where relevant. The anaesthetic team and ODP give the anaesthetic (local anaesthetic gel for flexible; general or spinal for rigid, as per centre protocol); antibiotics are given as per centre protocol. The circulating practitioner checks positioning in stirrups (lithotomy), pressure areas, warming, the camera stack and the irrigation fluid. The scrub practitioner sets up the endoscopy trolley and does the first count.
2. Access
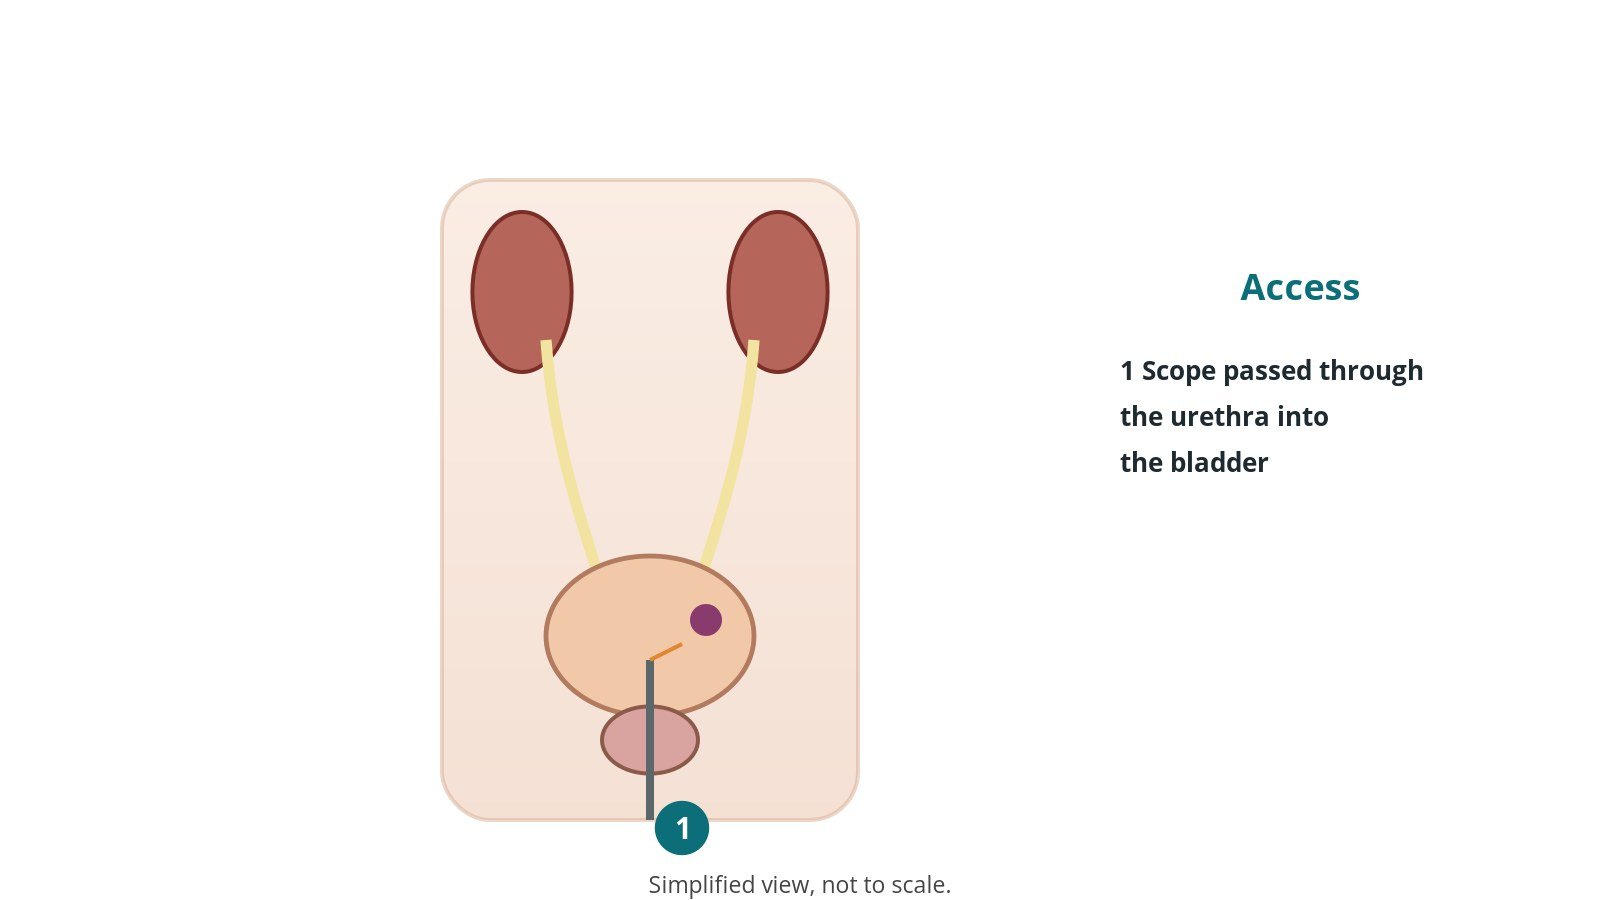
No skin cuts: the scope is passed through the urethra into the bladder.
3. Inspecting the bladder
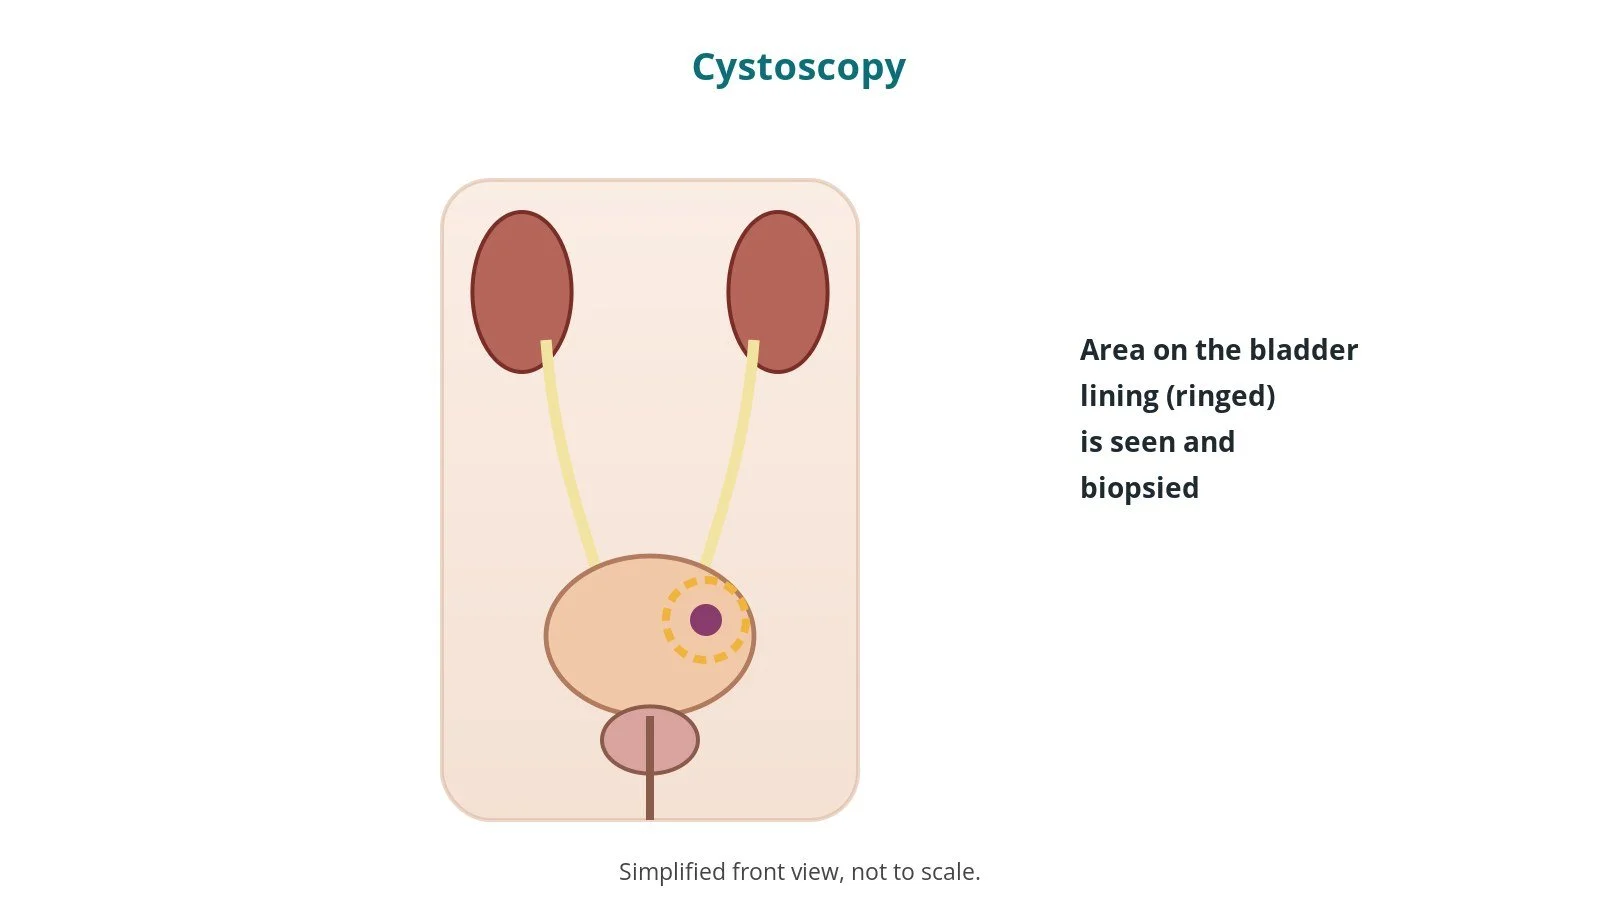
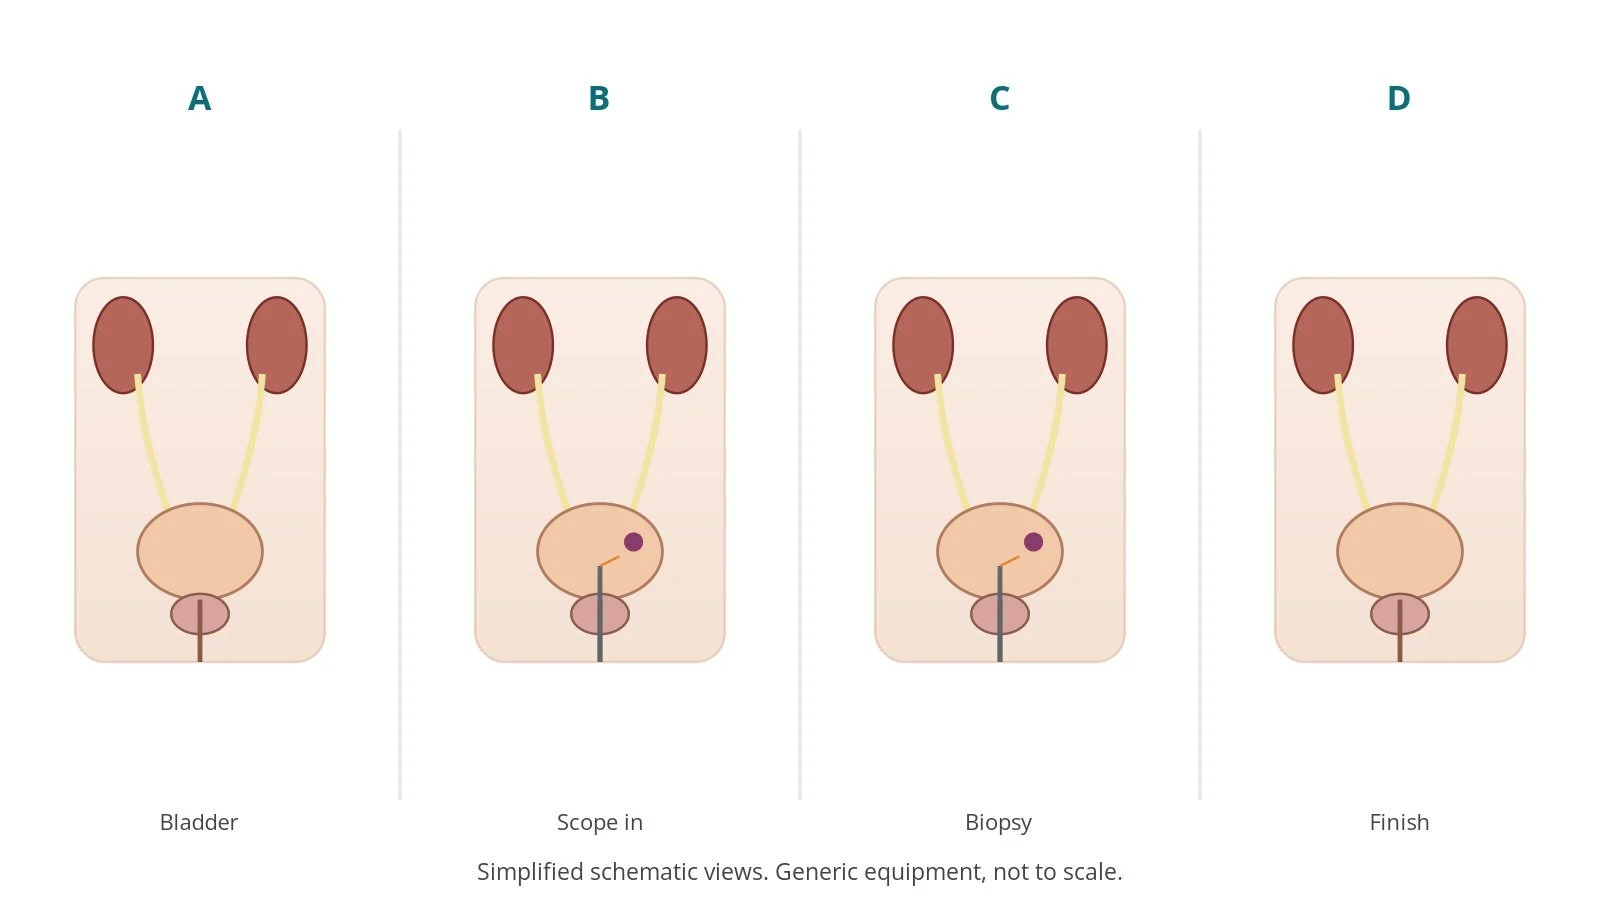
- A. Bladder. The bladder is filled with sterile fluid.
- B. Scope in. The scope is passed and the lining inspected systematically.
- C. Biopsy. Any abnormal area is biopsied or treated.
- D. Finish. The bladder is emptied; a catheter may be placed.
Biopsies are labelled with their site and checked before leaving theatre.
4. Finishing
The bladder is emptied and a catheter placed if needed, per surgeon. Final counts are confirmed, specimens labelled and checked, and the patient goes to recovery with a full handover.
Recovery and aftercare
- Same day: usually home the same day.
- Passing urine: stinging and some blood are common for a day or two.
- Drink plenty of fluids.
- Infection: seek help if you have a fever or worsening pain.
- Results: biopsy results are discussed at clinic.
- Activity: most people return to normal in 1–2 days.
Call 999 if you have chest pain, sudden breathlessness or collapse. Contact your team urgently if you cannot pass urine, pass large clots, have a high temperature or shivering, or have severe pain.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- stinging when passing urine
- blood in the urine
- urine infection
- difficulty passing urine (uncommon)
- bladder injury during biopsy (rare)
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
- cystoscopy stack: camera, light source, monitor
- flexible and rigid cystoscopes, per device and operator
- irrigation fluid and giving set
- biopsy forceps and diathermy, per surgeon
- local anaesthetic gel, as per centre protocol
- specimen pots and labels
- catheter, per surgeon
Procedural steps
- Team brief, WHO sign in; anaesthesia or local gel
- Positioning (lithotomy for rigid); prep and drape; count
- Scope passed; bladder filled
- Systematic inspection of the lining
- Biopsy or treatment; bleeding controlled
- Bladder emptied; catheter if needed; specimens; counts; sign out

First time in theatre?
💡 First-time tip
- Know your role. Scrub, circulating, anaesthetic and ODP each have their own checks; ask at the team brief.
- Counts matter. Swabs, needles and instruments are counted before, during and at closure; speak up if one is missing.
- Specimens. Label every specimen with site and side, and check it with the scrub practitioner before it leaves theatre.
- Specimens. Label each biopsy with its site in the bladder.
- Dignity. Keep the patient covered and explain each step if they are awake.
FAQ
Does it hurt?
Flexible cystoscopy is uncomfortable rather than painful; anaesthetic gel helps.
Will I be awake?
For flexible, yes; rigid is usually under anaesthetic.
When will I get results?
What was seen is often explained the same day; biopsy results take longer.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Cystoscopy. nhs.uk/conditions/cystoscopy
- NICE. Bladder cancer: diagnosis and management (NG2). nice.org.uk/guidance/ng2
- StatPearls (NCBI Bookshelf), search: cystoscopy. ncbi.nlm.nih.gov/books
- British Association of Urological Surgeons. Patient information leaflets. baus.org.uk
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.