Thyroidectomy: an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Thyroidectomy in one minute
What it is: surgery to remove part (hemithyroidectomy) or all (total thyroidectomy) of the thyroid gland in the neck.
Who it is for: people with thyroid nodules or cancer, an enlarged thyroid (goitre) causing pressure, or an overactive thyroid.
Main risks: bleeding in the neck, voice change, low calcium, needing thyroid tablets.
Usually: under general anaesthetic, 1–3 hours, home in 1–2 days.
On this page: What is a thyroidectomy? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
What is a thyroidectomy?
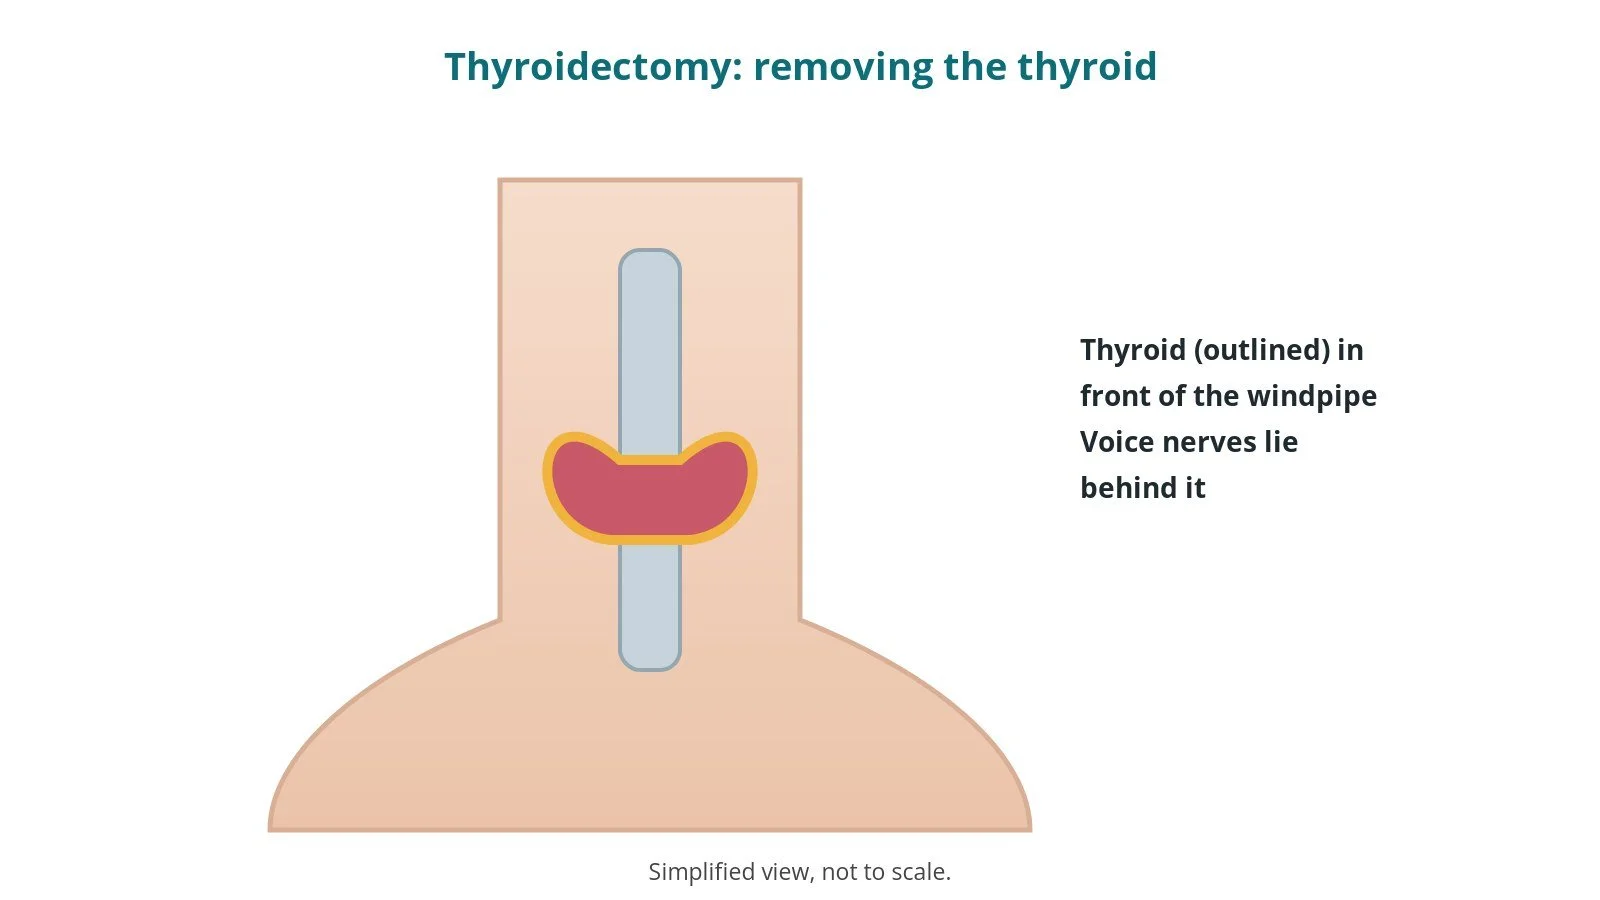
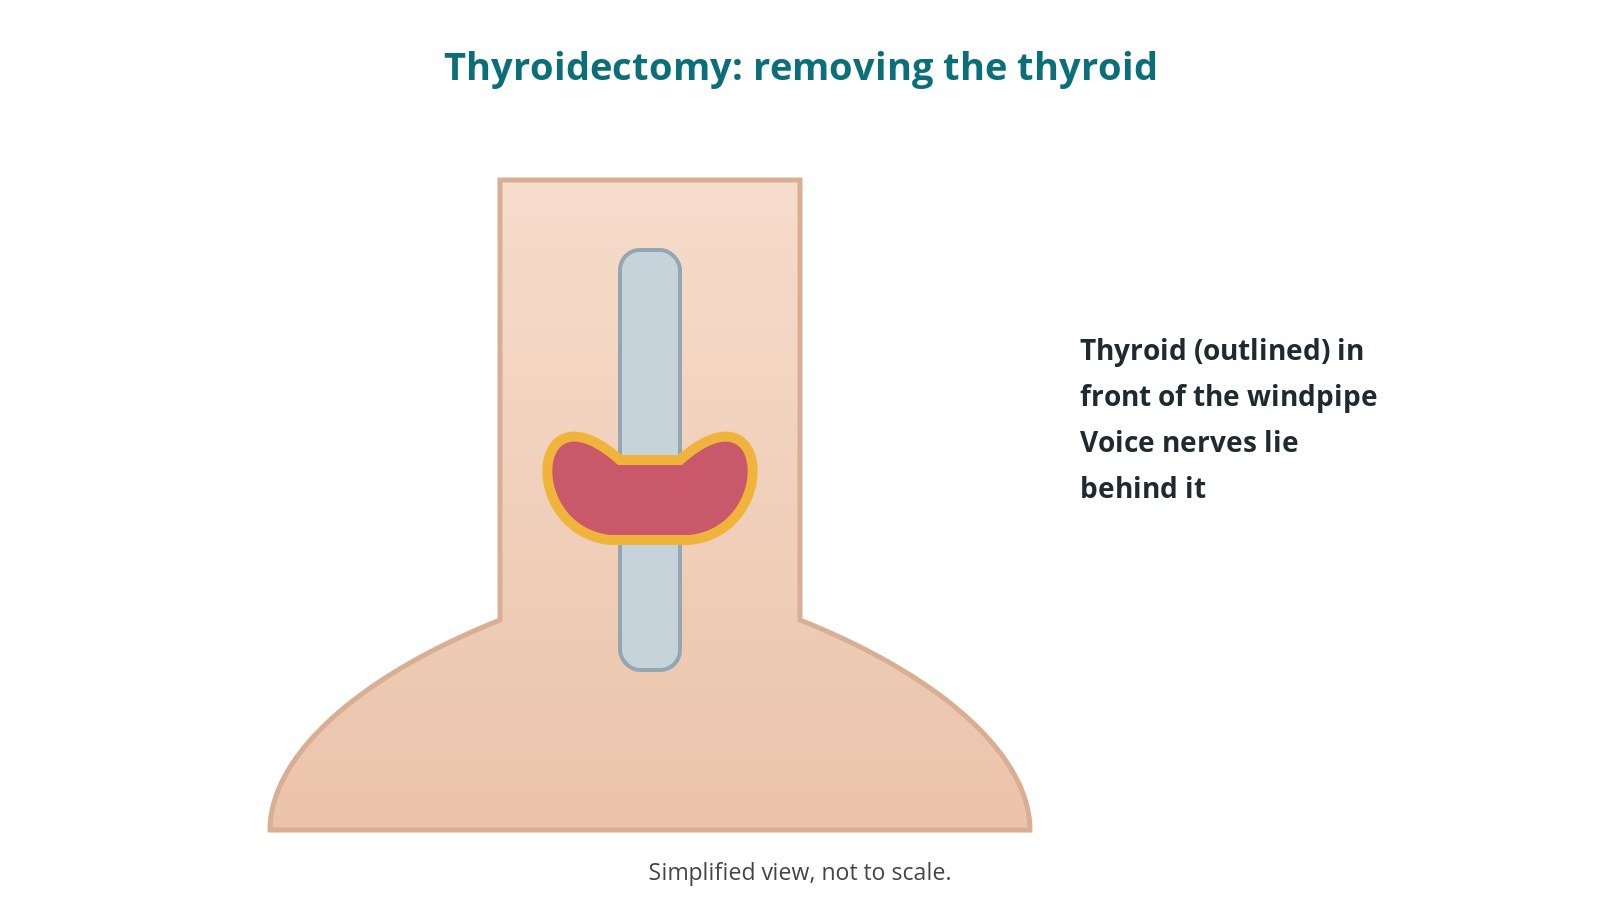
The thyroid is a butterfly-shaped gland at the front of the neck that makes thyroid hormone. Behind it lie the nerves to the voice box and the small parathyroid glands that control calcium.
- Hemithyroidectomy: one half (lobe) is removed
- Total thyroidectomy: the whole gland is removed; lifelong thyroid hormone tablets are needed
The surgeon works carefully to protect the voice nerves and parathyroid glands. A nerve monitor may be used, per surgeon and centre.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- a thyroid nodule that is suspicious or confirmed cancer
- an enlarged thyroid causing pressure on breathing or swallowing
- an overactive thyroid not controlled by other treatments
The decision is made by your surgical team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
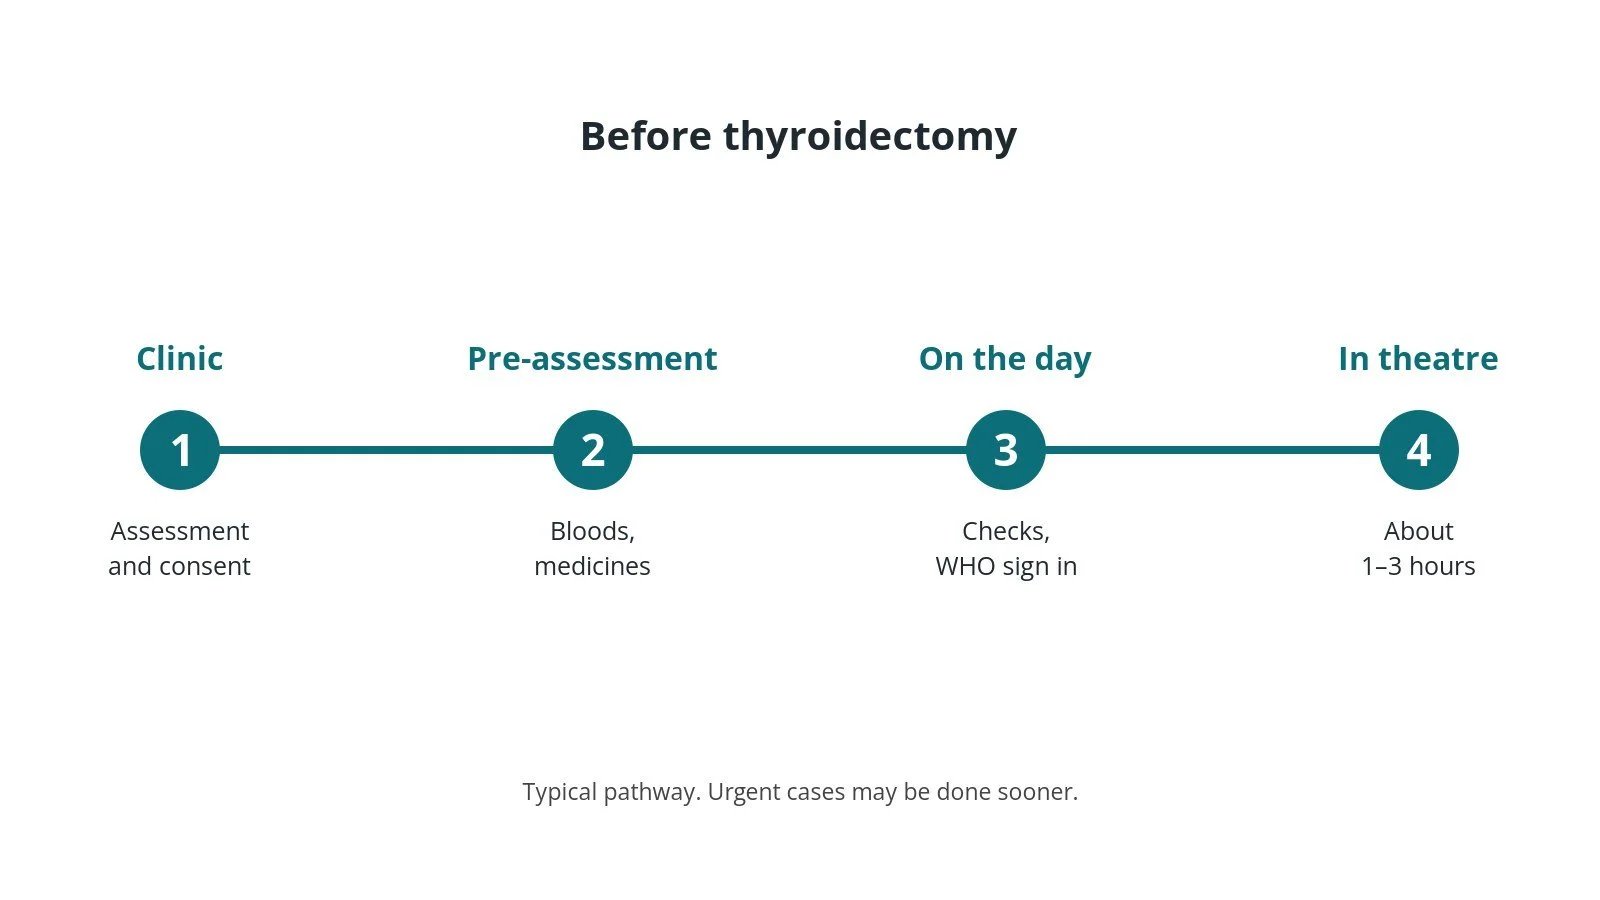
Most operations are planned; some are urgent. Before it, you usually have:
- an ultrasound scan and often a needle biopsy
- blood tests, including thyroid function and calcium
- a check of the vocal cords, per centre
- a review of your medicines, as per centre protocol
- a chance to ask questions and give consent
Step by step
1. Getting ready
Team brief and WHO checklist first. The anaesthetic team and ODP give the anaesthetic (general); antibiotics and blood-clot prevention are given as per centre protocol. The circulating practitioner checks positioning, pressure areas, the diathermy plate and warming. The scrub practitioner sets up the instrument trolley and does the first count. The neck is extended on a shoulder roll and head ring; a nerve-monitoring tube may be used.
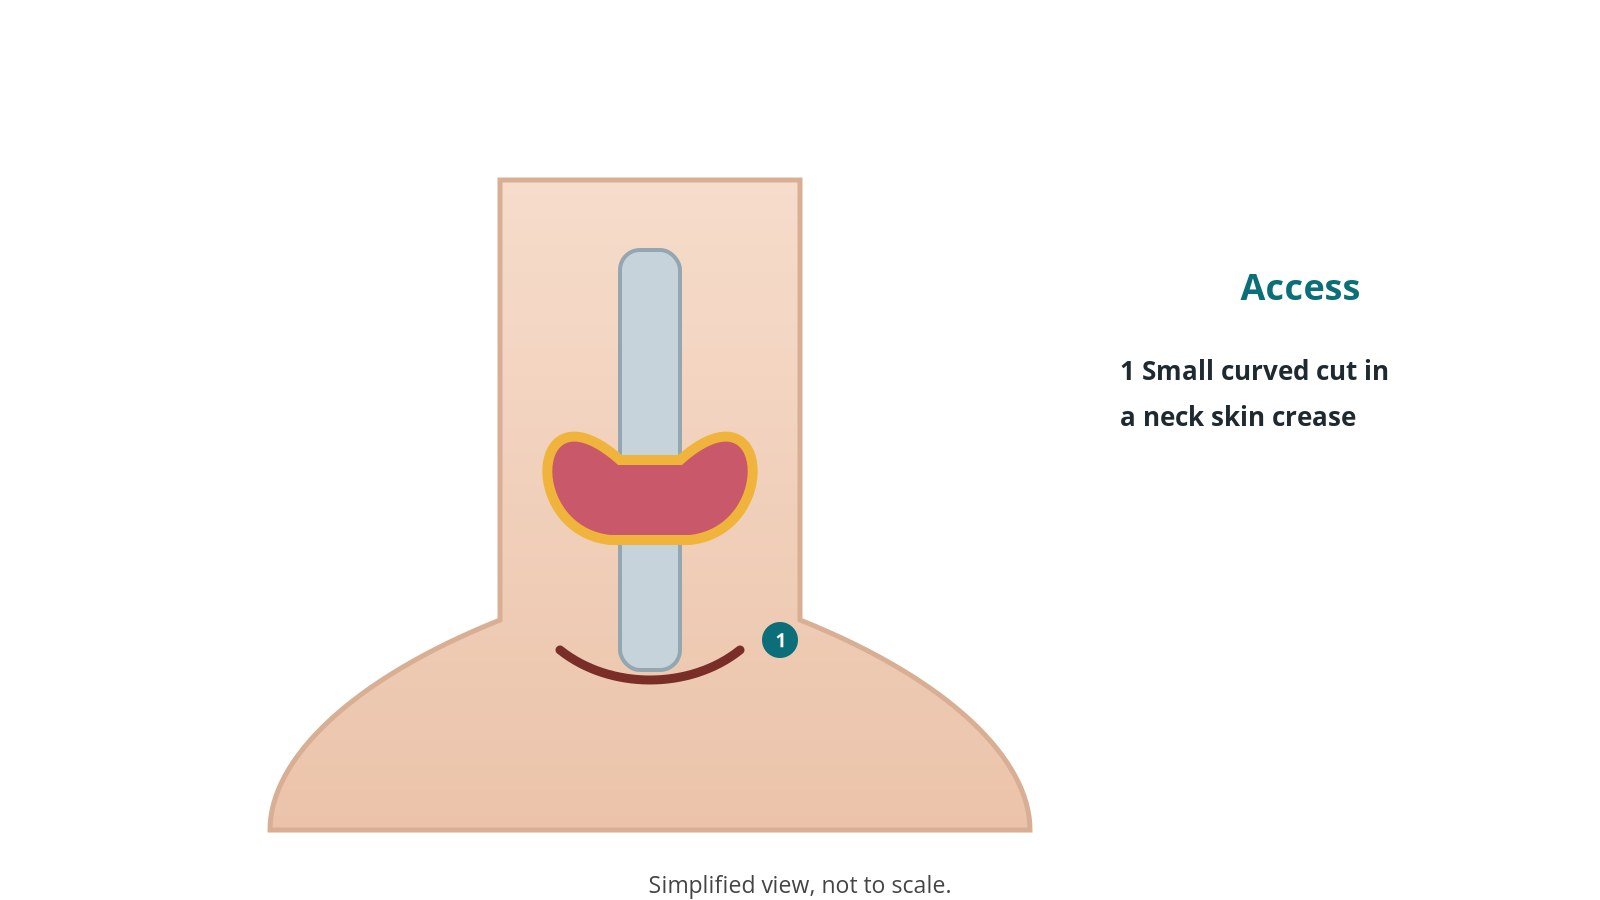
2. Access
A small curved cut is made in a skin crease at the front of the neck. The strap muscles are separated to reach the thyroid.
3. Removing the thyroid
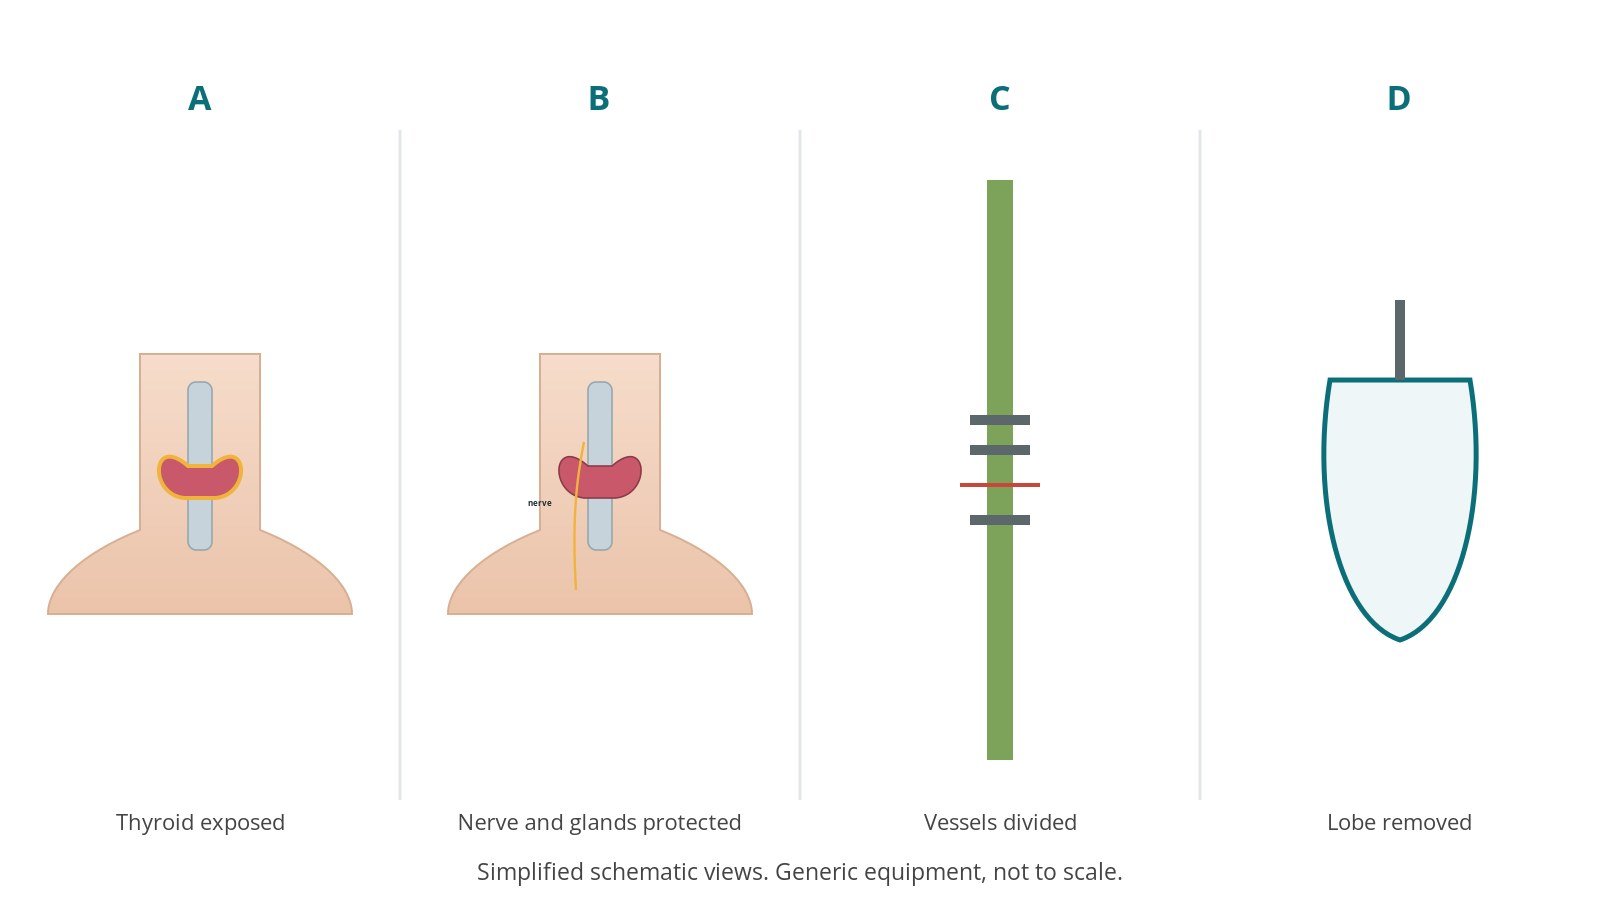
- A. Thyroid exposed. The strap muscles are separated and the thyroid seen.
- B. Nerve and glands protected. The voice nerve and parathyroid glands are found and kept safe, sometimes with a nerve monitor.
- C. Vessels divided. The thyroid blood vessels are sealed with ties or an energy device.
- D. Lobe removed. The lobe (or whole gland) is removed and bleeding checked.
4. Finishing
The muscles and skin are closed, often with dissolving sutures or glue; a drain is occasionally used. Final counts are confirmed before closure, specimens labelled and checked, and the patient goes to recovery with a full handover.
Recovery and aftercare
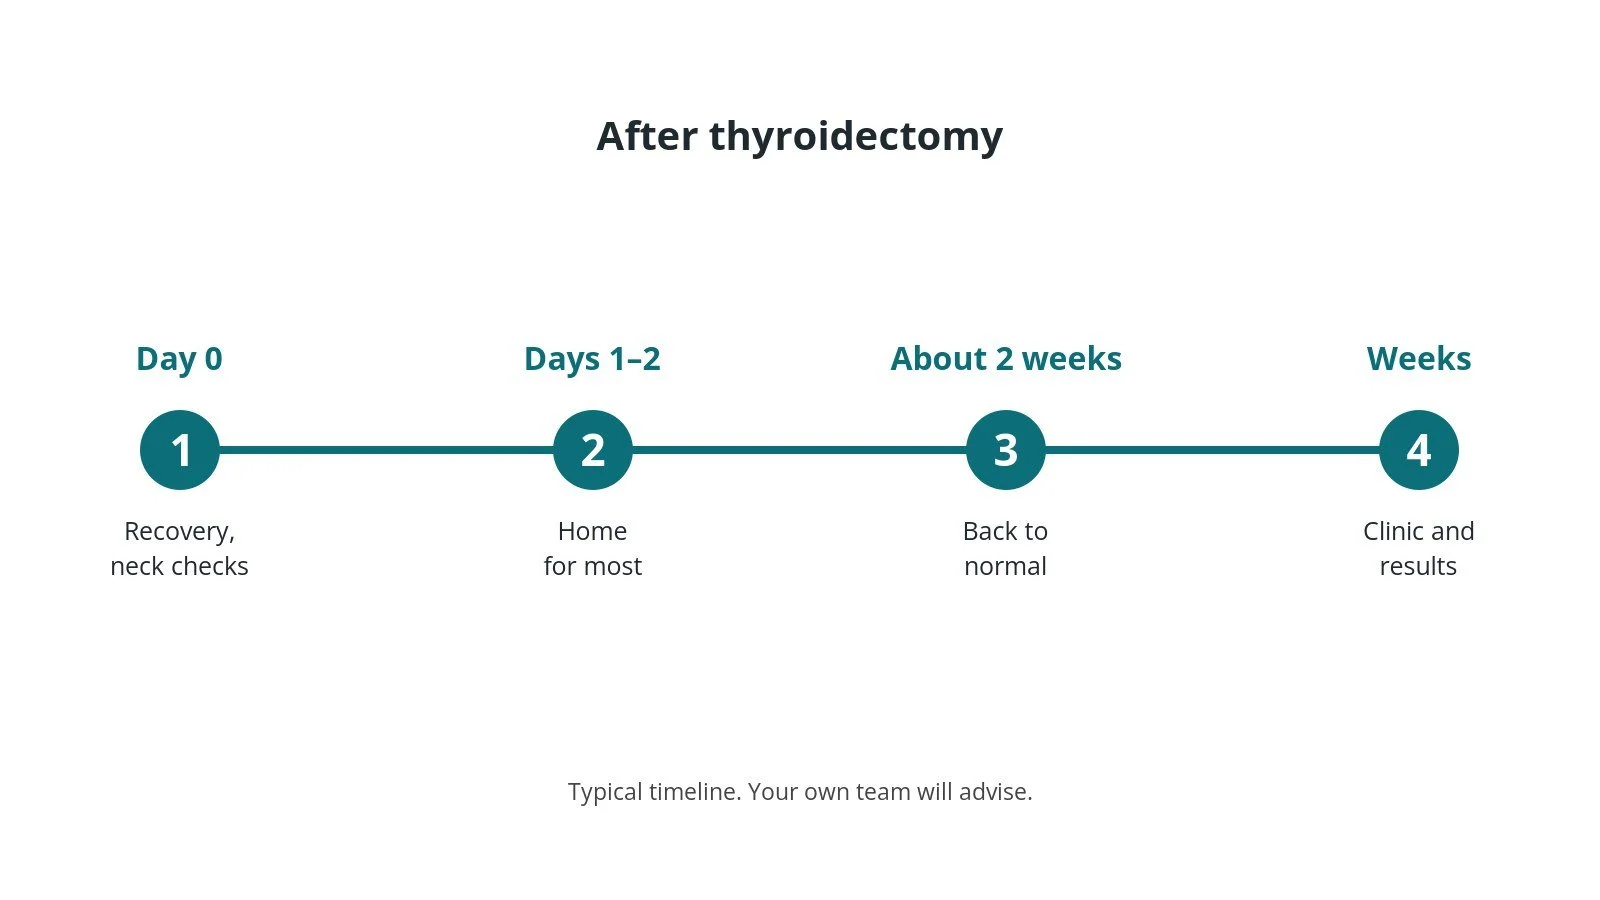
- First hours: in recovery, then a ward or day unit; pain relief and anti-sickness medicine as needed.
- Going home: usually 1–2 days.
- Activity: walking early; avoid heavy lifting for about 2 weeks; ask your team.
- Calcium: blood tests check calcium after a total thyroidectomy; tingling in the lips or fingers should be reported.
- Tablets: thyroid hormone tablets are needed after total thyroidectomy.
- Wounds: keep them clean and dry as advised; sutures or clips may need removing.
- Follow-up: clinic review or a phone call, as per centre protocol.
Call 999 if you have severe pain, heavy bleeding, breathlessness or collapse. Contact your team or GP if you have a fever, worsening tummy pain or swelling, vomiting, or a wound that becomes red, hot or leaky.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- bleeding in the neck, which can affect breathing (urgent)
- hoarse or weak voice, usually temporary
- low calcium, usually temporary
- needing thyroid hormone tablets
- wound infection or scarring
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
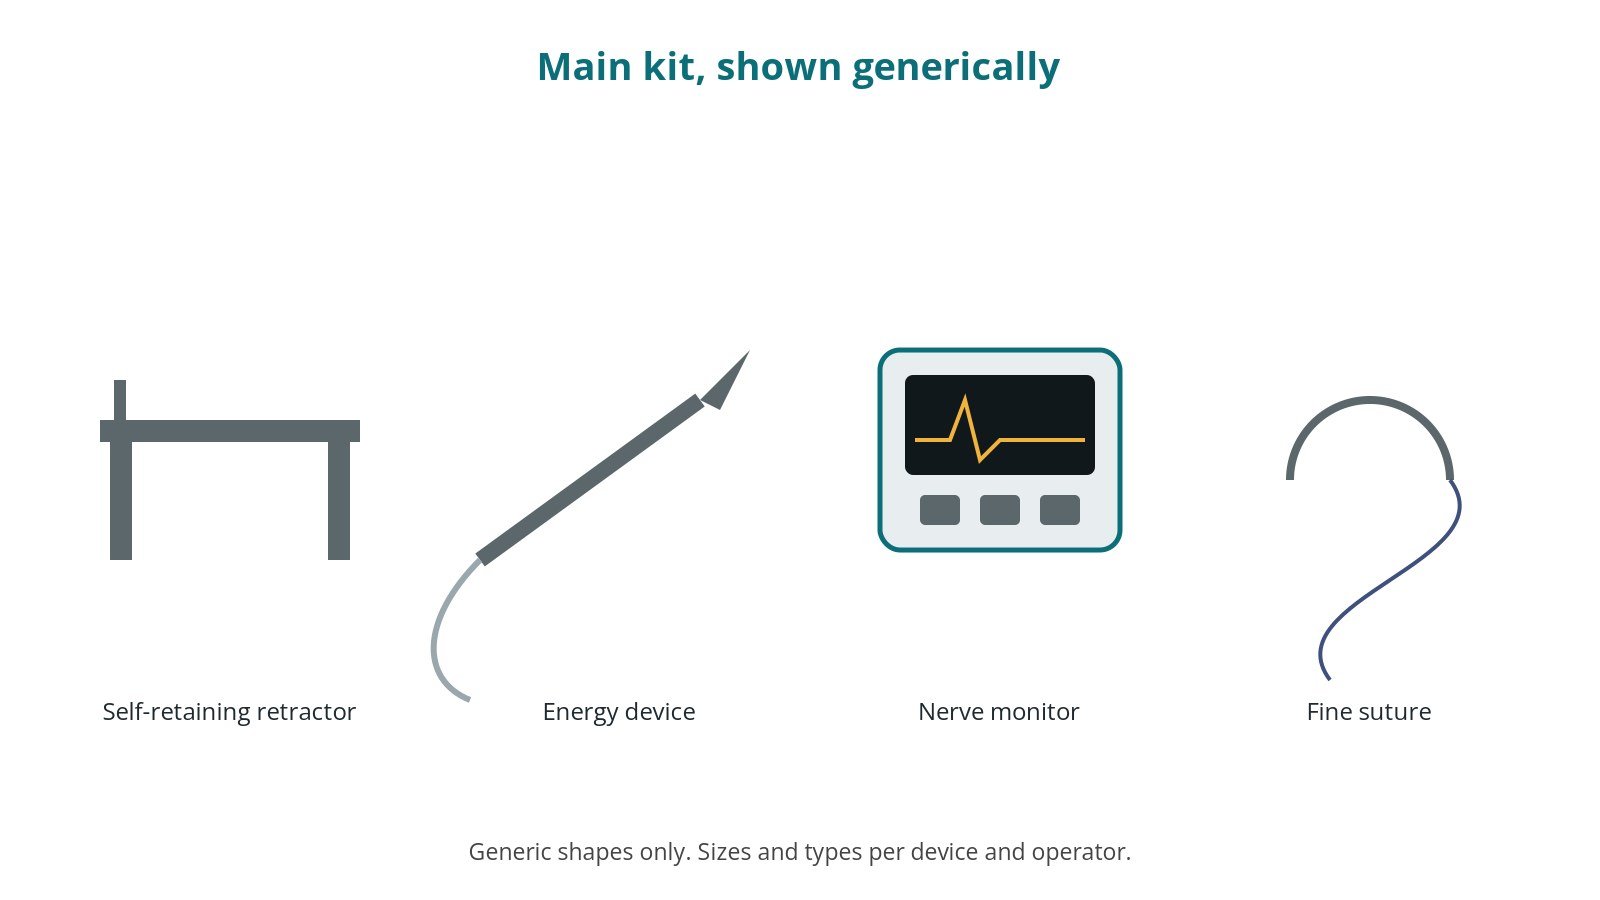
- thyroid instrument set
- small self-retaining retractor
- energy device for vessel sealing, per surgeon
- nerve monitor and tube, per surgeon and centre
- fine ties and sutures
- shoulder roll and head ring
- skin closure and dressing
Procedural steps
- Team brief, WHO sign in; anaesthesia; nerve-monitor tube if used
- Neck extended; prep and drape; count
- Collar incision; strap muscles separated
- Nerve and parathyroids identified; vessels sealed
- Lobe or gland removed; bleeding check
- Closure; counts; specimen check; sign out and handover; neck check in recovery
First time in theatre?
💡 First-time tip
- Know your role. Scrub, circulating, anaesthetic and ODP each have their own checks; ask at the team brief.
- Counts matter. Swabs, needles and instruments are counted before, during and at closure; speak up if one is missing.
- Specimens. Label every specimen with site and side, and check it with the scrub practitioner before it leaves theatre.
- Neck checks. In recovery, watch for neck swelling and breathing difficulty; know your unit's emergency plan for neck bleeding.
- Nerve monitor. Check the monitor is connected and tested before the cut.
FAQ
Will my voice change?
Most voices are normal; a few people have temporary hoarseness.
Will I need tablets?
After total thyroidectomy, yes, lifelong. After half, sometimes.
Will there be a scar?
A small neck scar that usually fades well in a skin crease.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Thyroid cancer: treatment. nhs.uk/conditions/thyroid-cancer/treatment
- NICE. Thyroid disease: assessment and management (NG145). nice.org.uk/guidance/ng145
- StatPearls (NCBI Bookshelf), search: thyroidectomy. ncbi.nlm.nih.gov/books
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.