Thoracotomy and VATS: an OR 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Thoracotomy and VATS in one minute
What it is: the two main ways a surgeon reaches the lung and chest: an open cut between the ribs (thoracotomy) or keyhole surgery with a camera (VATS).
Who it is for: people needing lung resection, biopsy, treatment of fluid or air around the lung, or other chest operations.
Main risks: air leak, bleeding, infection, long-lasting wound pain; rarely death.
Usually: under general anaesthetic, 1–4 hours, 2–7 days in hospital depending on the operation.
On this page: What are thoracotomy and VATS? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in theatre? · FAQ
What are thoracotomy and VATS?
Both are approaches (ways in) rather than a single operation. Many chest operations can be done either way.
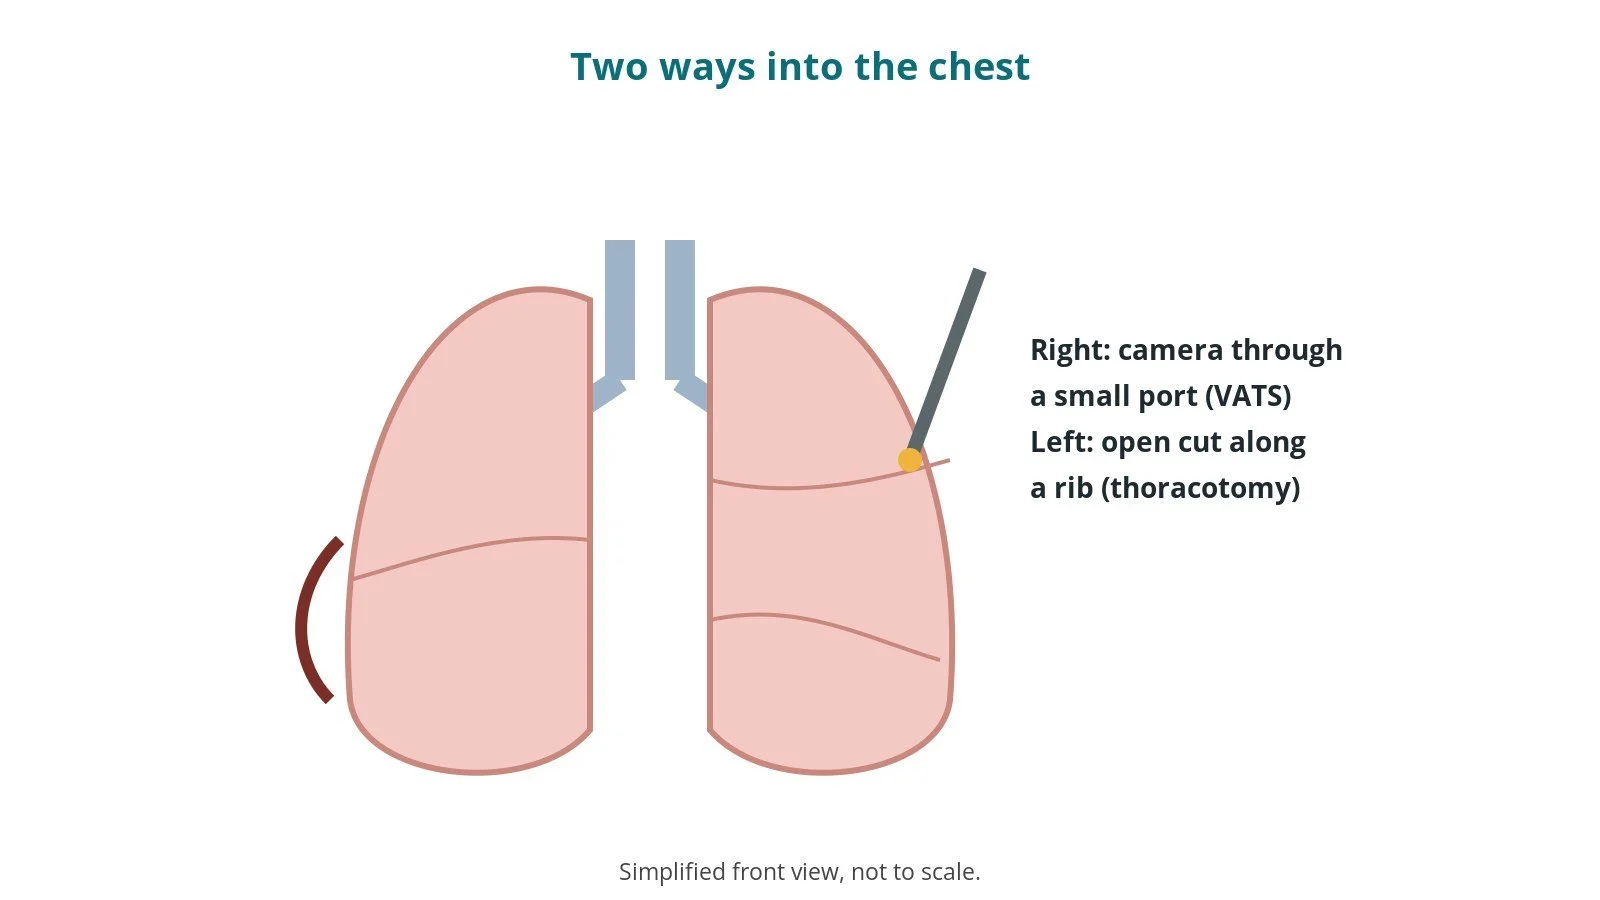
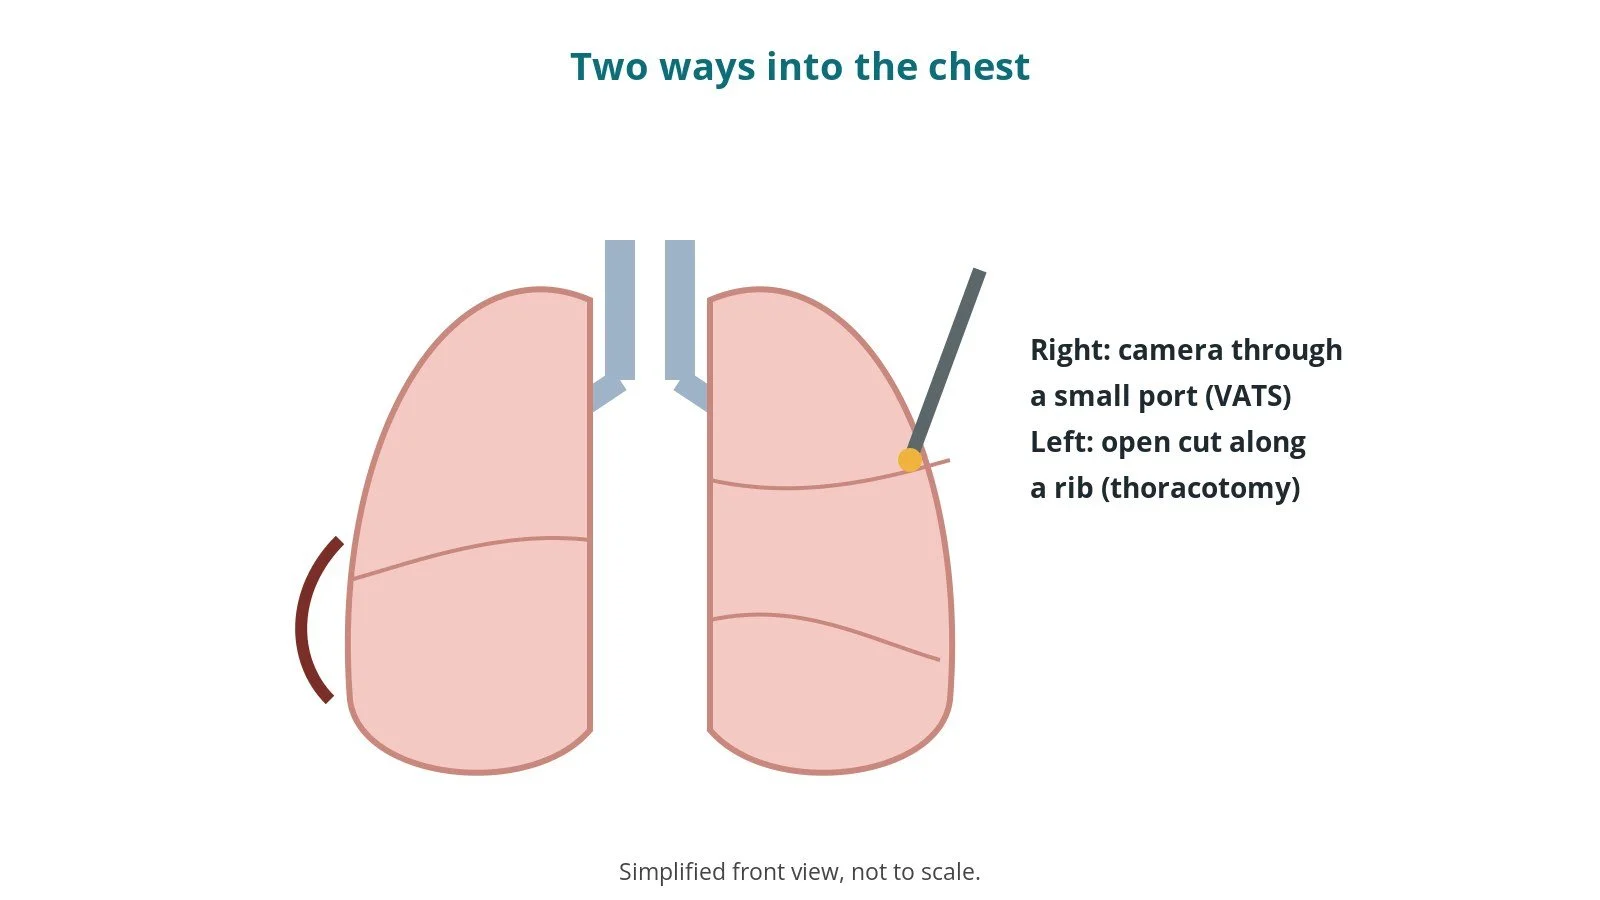
- VATS (video-assisted thoracoscopic surgery): one to four small cuts between the ribs; a camera shows the inside of the chest on a screen and long instruments are used through the ports
- Thoracotomy: a longer cut on the side or back of the chest; the ribs are gently spread to give the surgeon a direct view and hands-on access
- Robotic surgery: keyhole surgery using a robot-assisted system, in some centres
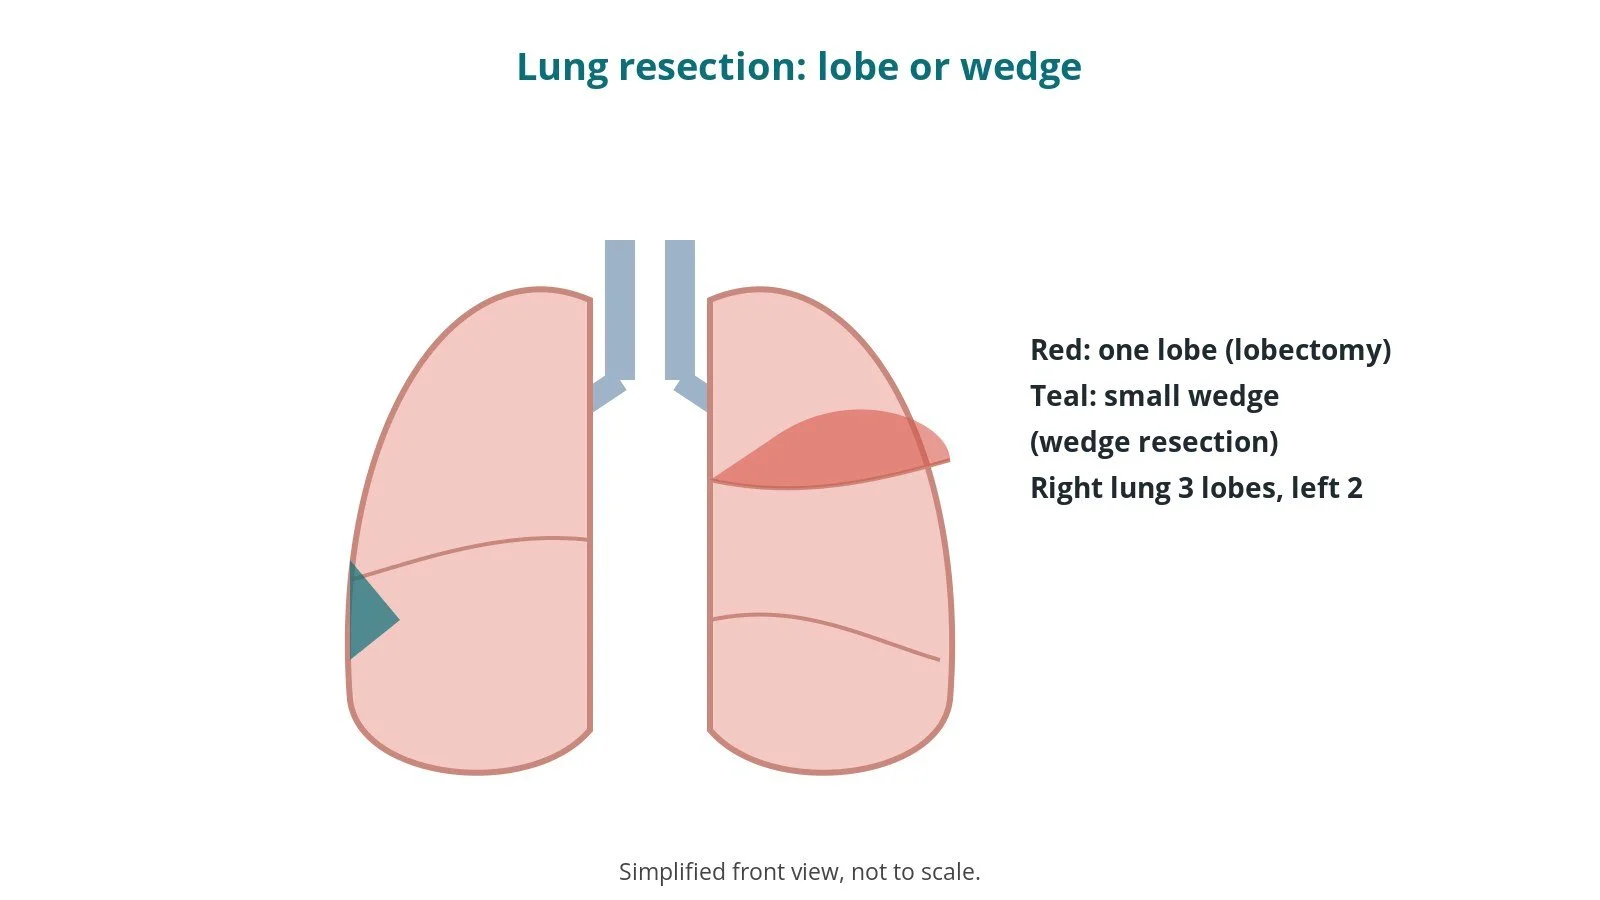
Common operations include lobectomy and wedge resection, lung biopsy, treating collapsed lung (pneumothorax), draining infected fluid (empyema) and pleural procedures.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- lung resection for cancer or nodules
- repeated or persistent collapsed lung (pneumothorax)
- infected or trapped fluid around the lung (empyema)
- biopsy of the lung, pleura or lymph nodes
- chest injuries or bleeding (sometimes as an emergency, usually thoracotomy)
The decision, including keyhole or open, is made by your surgical team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
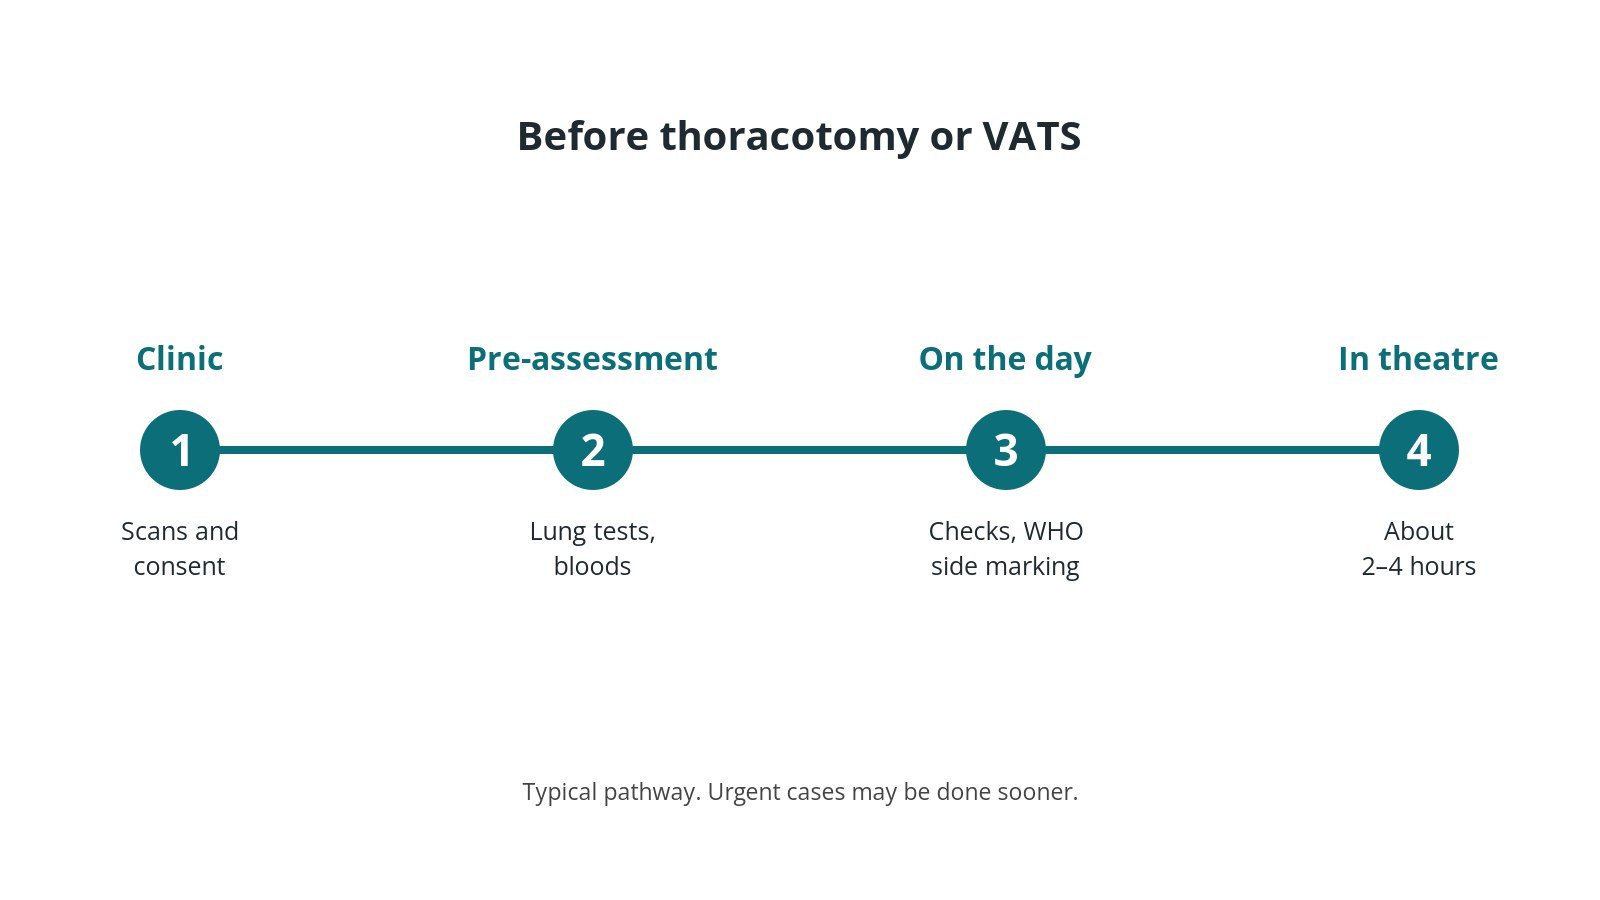
Most operations are planned; some are urgent. Before it, you usually have:
- CT and other scans of the chest
- breathing (lung function) tests
- blood tests, an ECG and sometimes an echo
- a review of your medicines, especially blood thinners, as per centre protocol
- a chance to ask questions and give consent, including the chance of conversion from keyhole to open
Step by step
1. Getting ready
Theatre team brief and WHO checklist first. The anaesthetic team and ODP give a general anaesthetic and place a double-lumen tube (or blocker) so one lung can be deflated, plus an arterial line and pain relief such as a nerve block or epidural, as per centre protocol. The patient is turned onto their side (lateral position) with careful padding; the circulating practitioner checks pressure areas, the diathermy plate, warming and the correct side marking. The scrub practitioner sets up the thoracic and camera trolleys.
2. Access
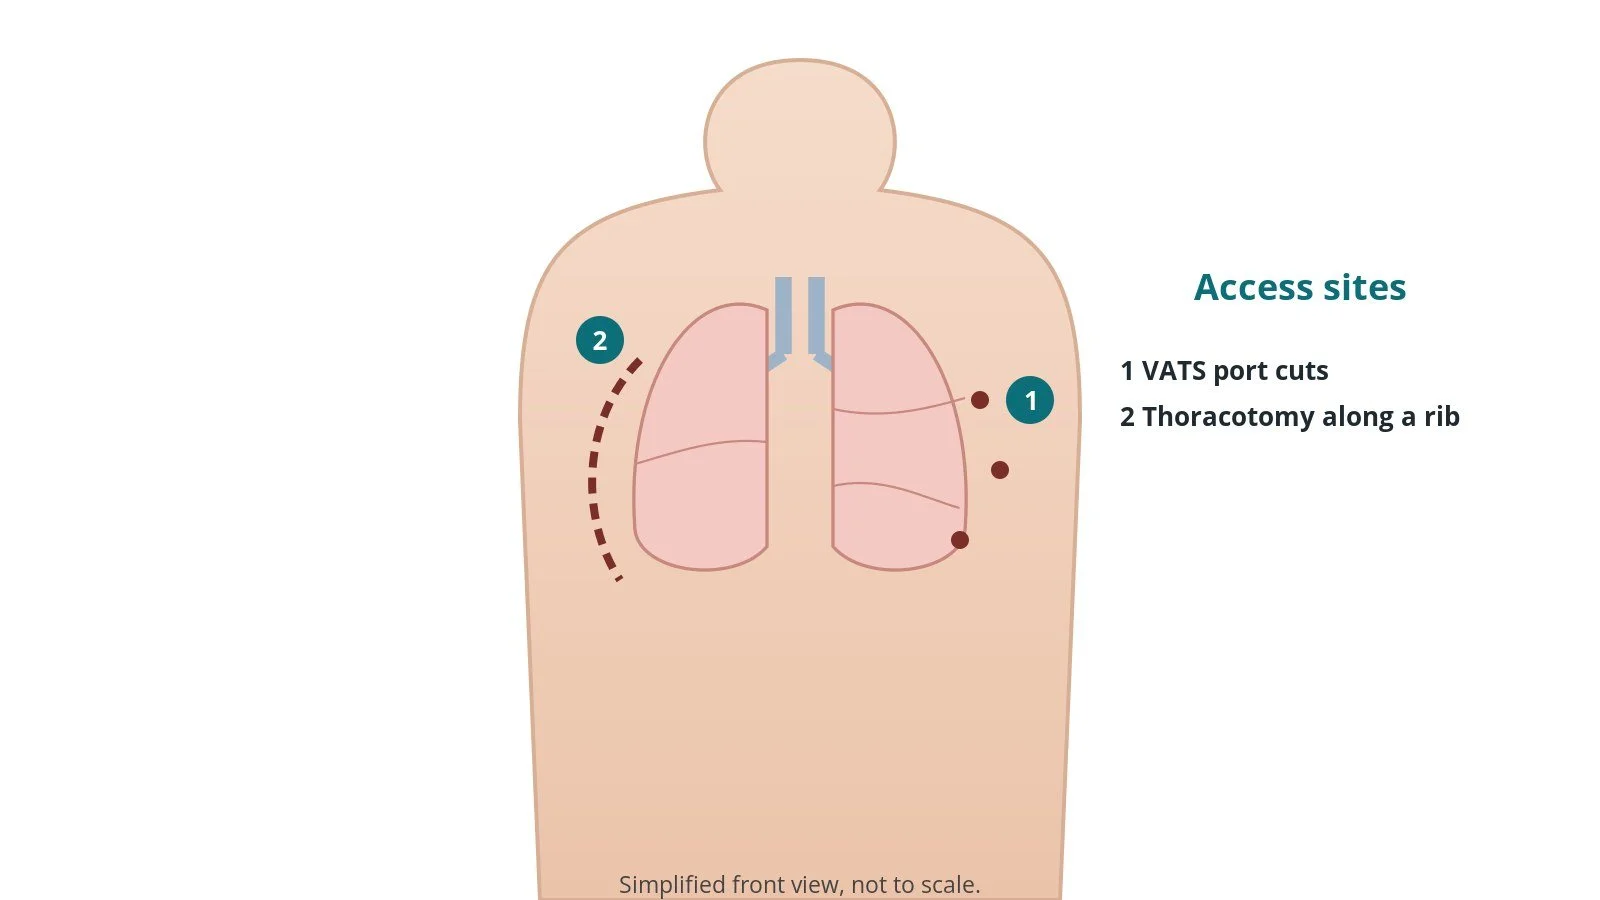
For VATS, small port cuts are made between the ribs and the camera is inserted first. For a thoracotomy, a longer cut is made along a rib space, muscles are divided or spared, and a rib spreader opens the space. Counts are recorded, as per centre protocol.
3. Working inside the chest
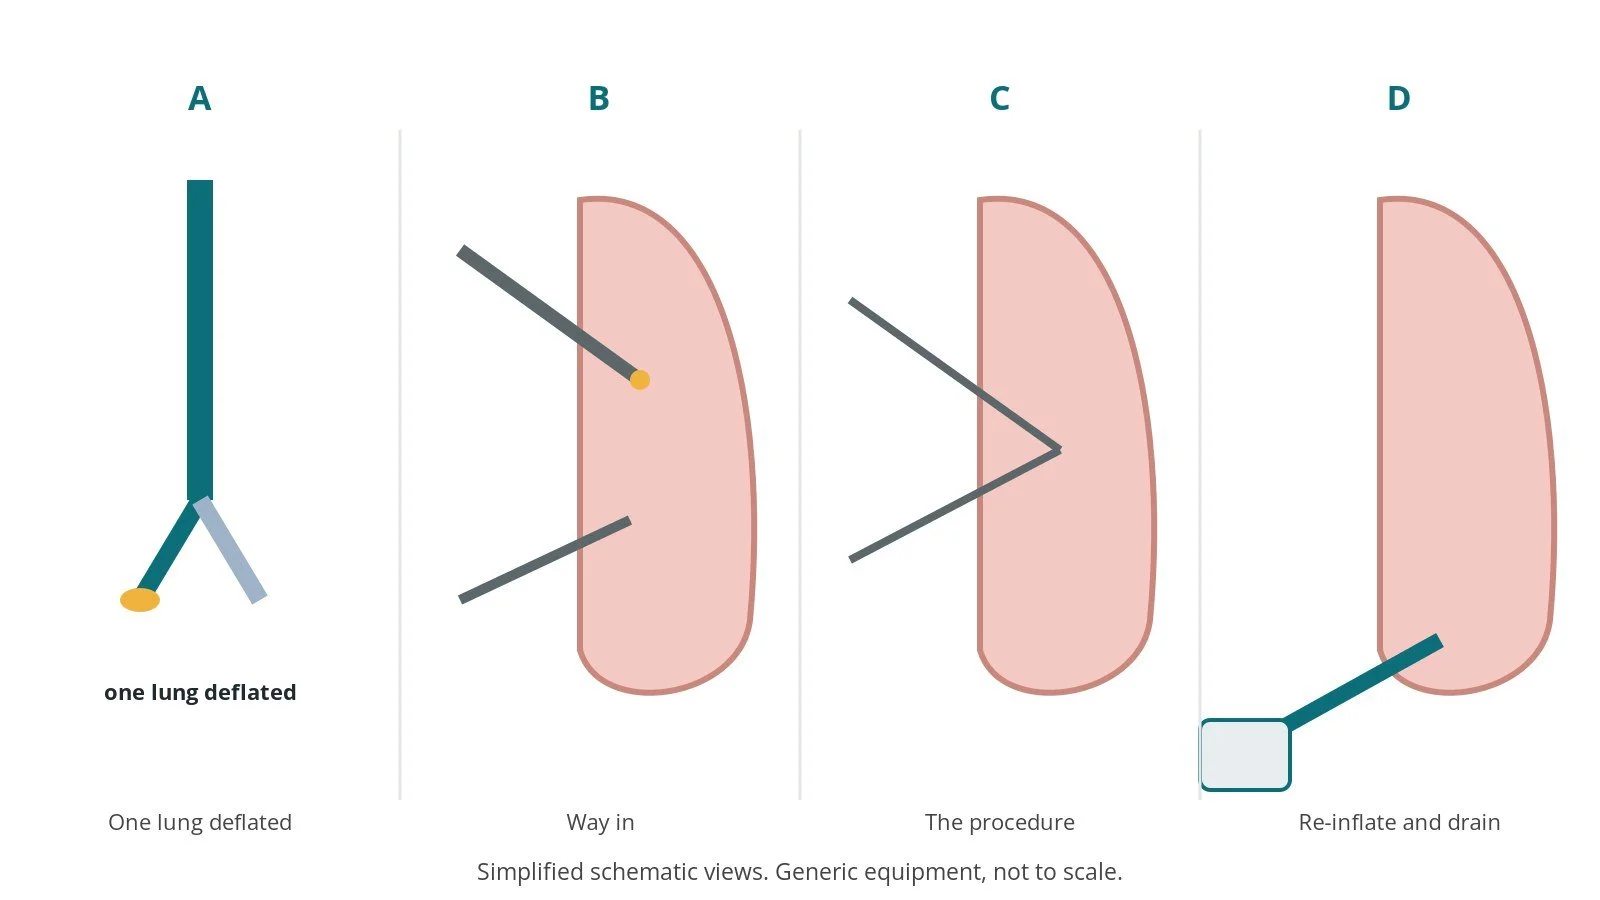
- A. One lung deflated. The lung on the operating side is deflated through the double-lumen tube.
- B. Way in. Ports and camera (VATS), or an incision between the ribs and a rib spreader (thoracotomy).
- C. The procedure. The planned operation is carried out: resection, biopsy, removing fluid or treating the pleura, per surgeon.
- D. Re-inflate and drain. The lung is re-inflated, air leaks checked, and a chest drain placed before closing.
If bleeding or difficult anatomy occurs during VATS, the surgeon may convert to a thoracotomy; the open tray should be ready to open immediately.
4. Finishing
One or more chest drains are placed and connected to a drainage system. For a thoracotomy, the ribs are brought together with strong sutures and the muscle and skin closed in layers. Nerve block or catheter pain relief is placed, as per centre protocol. Final counts are confirmed and the patient goes to recovery with a full handover.
Recovery and aftercare
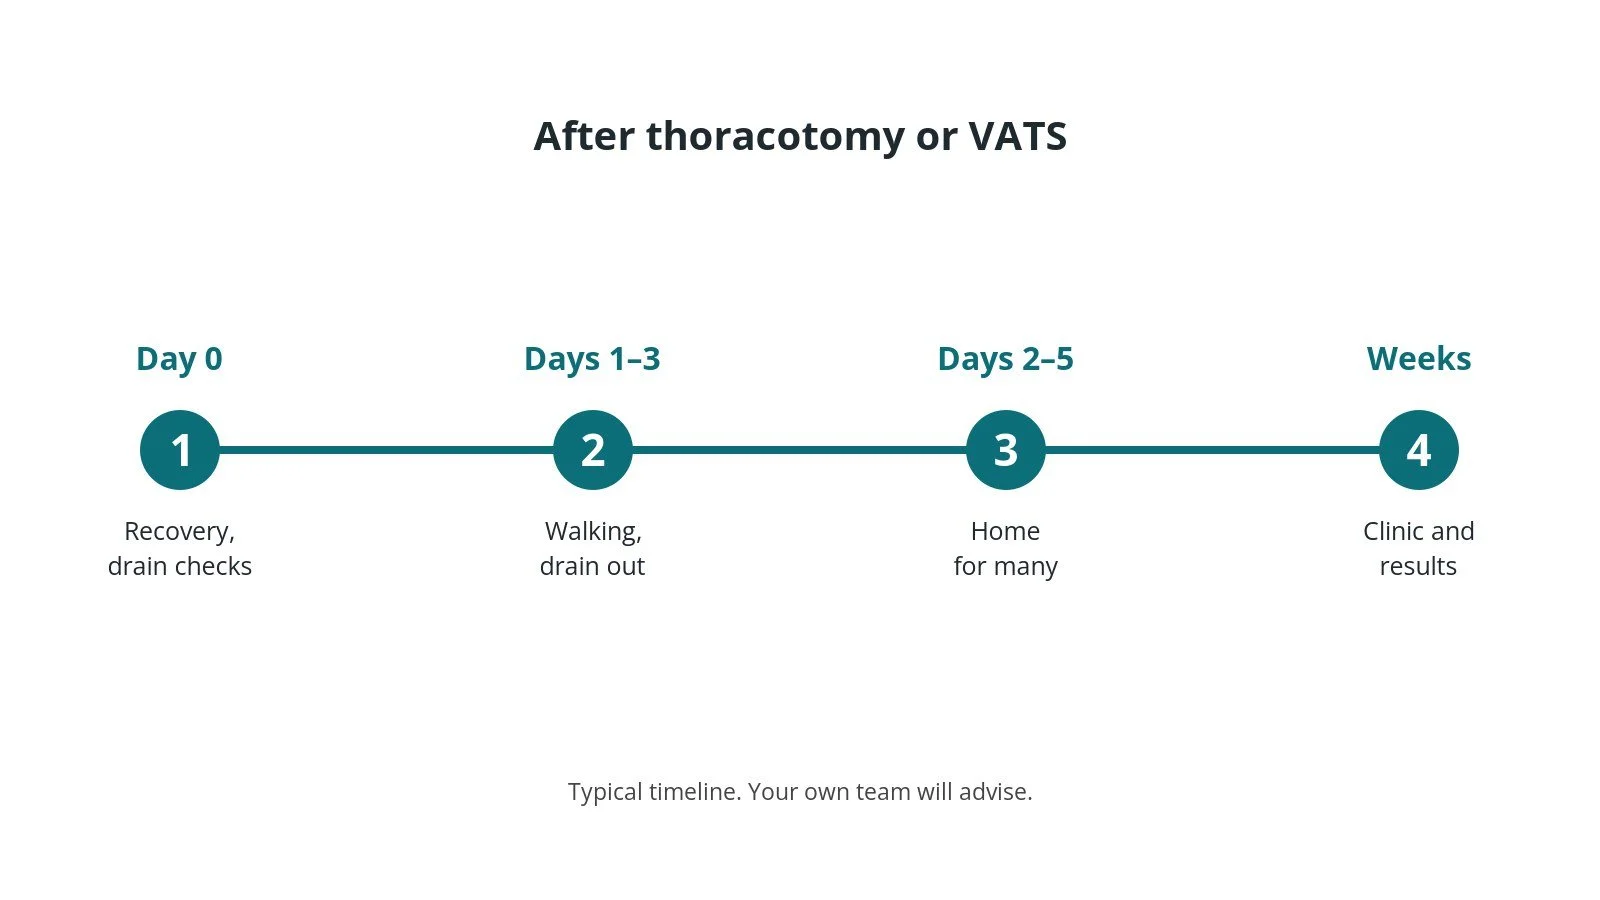
- First hours: in recovery, then a ward or high-dependency bed; oxygen, pain relief and chest drain checks, as per centre protocol.
- Breathing and walking: physiotherapy, deep breathing and walking start on day one.
- Chest drain: usually stays until air leak and fluid settle, often 1–3 days.
- Going home: often 2–5 days after VATS; a thoracotomy usually needs a longer stay.
- Pain: good pain control helps you breathe deeply and cough; tell the team if it is not controlled.
- Activity: avoid heavy lifting for several weeks; ask your team.
- Results: tissue results are discussed at clinic, usually within a few weeks.
Call 999 if you have severe breathlessness, chest pain or coughing up a lot of blood. Contact your team if you have a fever, or a wound becomes red, hot or leaky.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- air leak from the lung, keeping the chest drain in longer
- bleeding, rarely needing a return to theatre
- chest infection or pneumonia
- irregular heartbeat, usually atrial fibrillation
- wound pain or numbness that can last months
- blood clots in the legs or lungs
- conversion from keyhole to open surgery
- death (uncommon)
Theatre kit list (printable)
Example kit list
Every theatre has its own protocol, and sizes and doses vary.
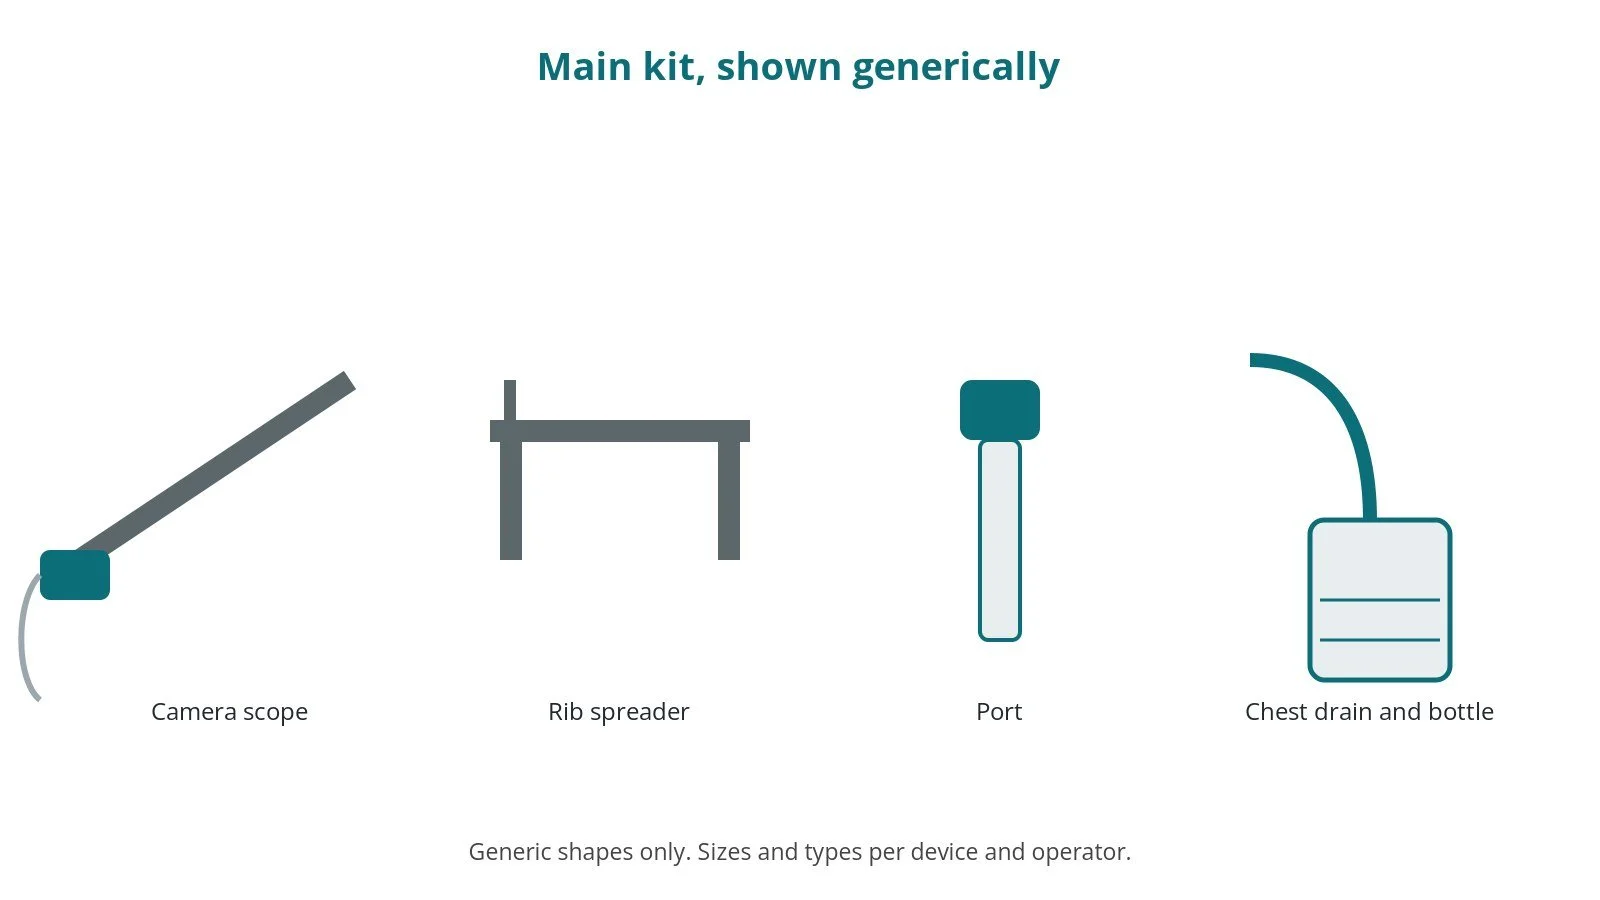
- thoracic instrument set; VATS instruments (long graspers, scissors, dissectors)
- camera stack with scope, light source and warmer
- ports or wound protector, per surgeon
- thoracotomy tray: rib spreader, rib approximator, periosteal elevators
- surgical staplers and reloads, sizes per device and operator
- energy device for dissection, per surgeon
- strong rib-closure sutures and layered closure sutures
- chest drains, drainage system and suction
- local anaesthetic for nerve block or catheter, as per centre protocol
- specimen pots, labels and request forms
Procedural steps
- Team brief, WHO sign in; side marked; anaesthesia, double-lumen tube, lines, block
- Lateral position, padding, arm support; prep and drape; counts
- VATS ports and camera, or thoracotomy and rib spreader
- Planned procedure; specimens labelled
- Leak test; haemostasis; chest drain(s)
- Rib closure (thoracotomy); layered closure; counts; sign out and handover
First time in theatre?
💡 First-time tip
- Correct side. The side is marked and checked at sign in and again before the cut; join in the check.
- One-lung ventilation. Anaesthetic and ODP confirm tube position with a camera after turning; stay out of the way at this moment.
- Camera first. Know how to white-balance the camera and warm the scope to stop fogging.
- Specimens. Label every specimen with side and site and check it with the scrub practitioner before it leaves theatre.
- Open set ready. A thoracotomy tray stays available in case keyhole surgery has to convert to open.
FAQ
Which is better, VATS or thoracotomy?
Keyhole surgery usually means less pain and a shorter stay, but some operations need open access. Your surgeon decides case by case.
Why do I need a chest drain?
It lets air and fluid out so the lung can stay fully inflated while it heals.
Will the pain last?
Most pain settles over weeks; some people have numbness or ache along the rib for longer. Tell your team.
Related guides
Sources
All checked on 14 October 2026. Each page's own date is shown where it gives one.
- NHS. Lung cancer: treatment. nhs.uk/conditions/lung-cancer/treatment
- StatPearls (NCBI Bookshelf), search: video assisted thoracoscopic surgery. ncbi.nlm.nih.gov/books
- StatPearls (NCBI Bookshelf), search: thoracotomy. ncbi.nlm.nih.gov/books
- World Health Organization. Surgical Safety Checklist. who.int
Disclaimer
Education only. This page is for general education for healthcare students, theatre staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, surgical team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a medical emergency, call 999.
Disclosure: I work in the medical device industry. This page is independent education and isn't sponsored or reviewed by any company.
All diagrams on this page are original illustrations created for rodnieoro.com.