Vein of Marshall ethanol infusion: a Cath Lab 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: November 2026 · Education only, not medical advice
Vein of Marshall ethanol infusion in one minute
What it is: The vein of Marshall is a small vein on the side of the left atrium that drains into the coronary sinus. Through a tiny balloon placed in the vein, ethanol (alcohol) is infused to treat the muscle and nerves around it. Radiofrequency ablation then completes the lines.
Who it is for: People having ablation for persistent AF, a repeat AF ablation, or flutter circling the mitral valve (mitral isthmus flutter), when the team thinks this area needs treating.
Main risks: Groin bruising, fluid around the heart, inflammation around the heart, and rarely injury to the coronary sinus or stroke. As with all AF ablation, the rhythm can come back.
Usually: Added to an AF ablation, under general anaesthetic or deep sedation, a few hours in total, home the same or next day.
On this page: What is vein of Marshall ethanol infusion? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in the lab? · FAQ
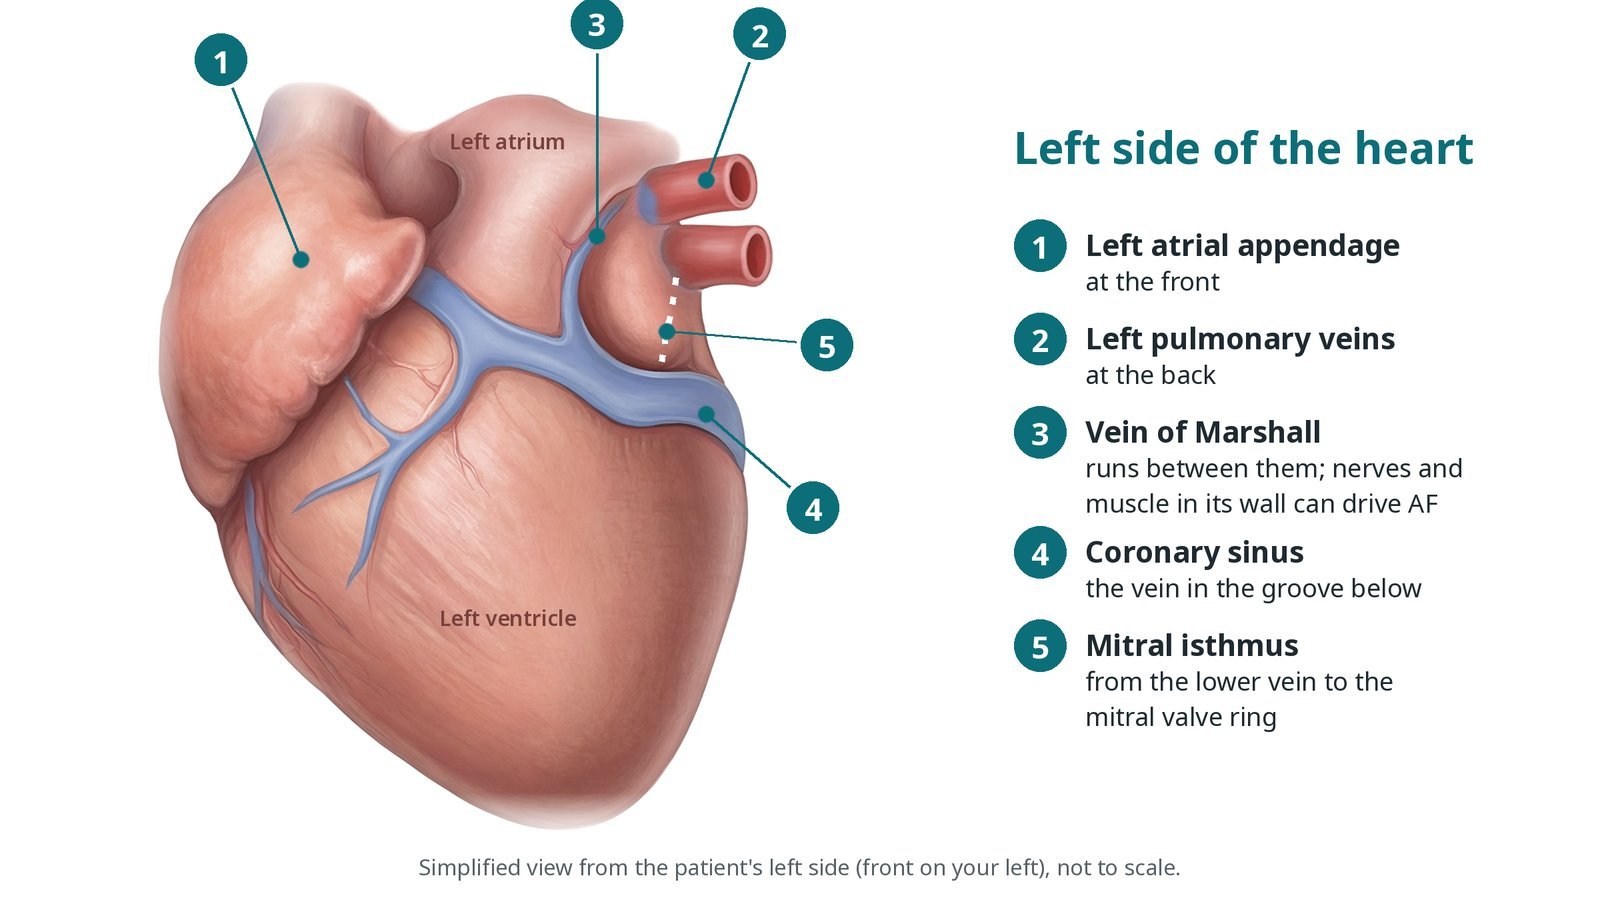
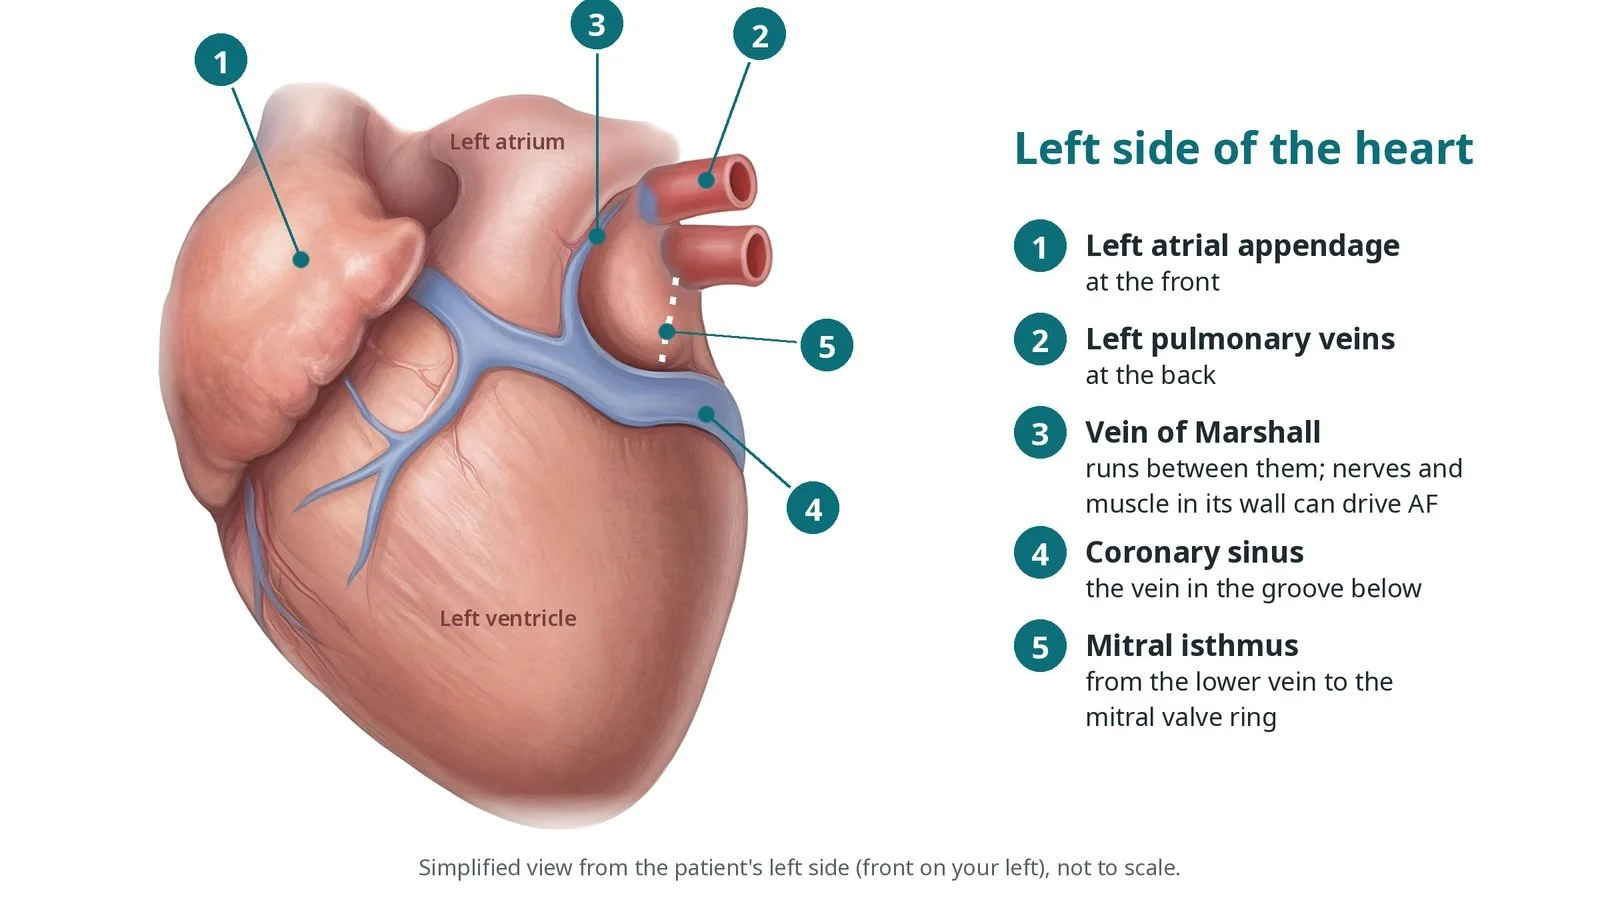
Left side of the heart: (1) left atrial appendage; (2) left pulmonary veins; (3) vein of Marshall, running between them; (4) coronary sinus in the groove below; (5) mitral isthmus.
What is vein of Marshall ethanol infusion?
The vein of Marshall is left over from a vein present before birth. It runs down the outside of the left atrium, between the left atrial appendage and the left pulmonary veins, and drains into the coronary sinus: the large vein in the groove between the left atrium and left ventricle.
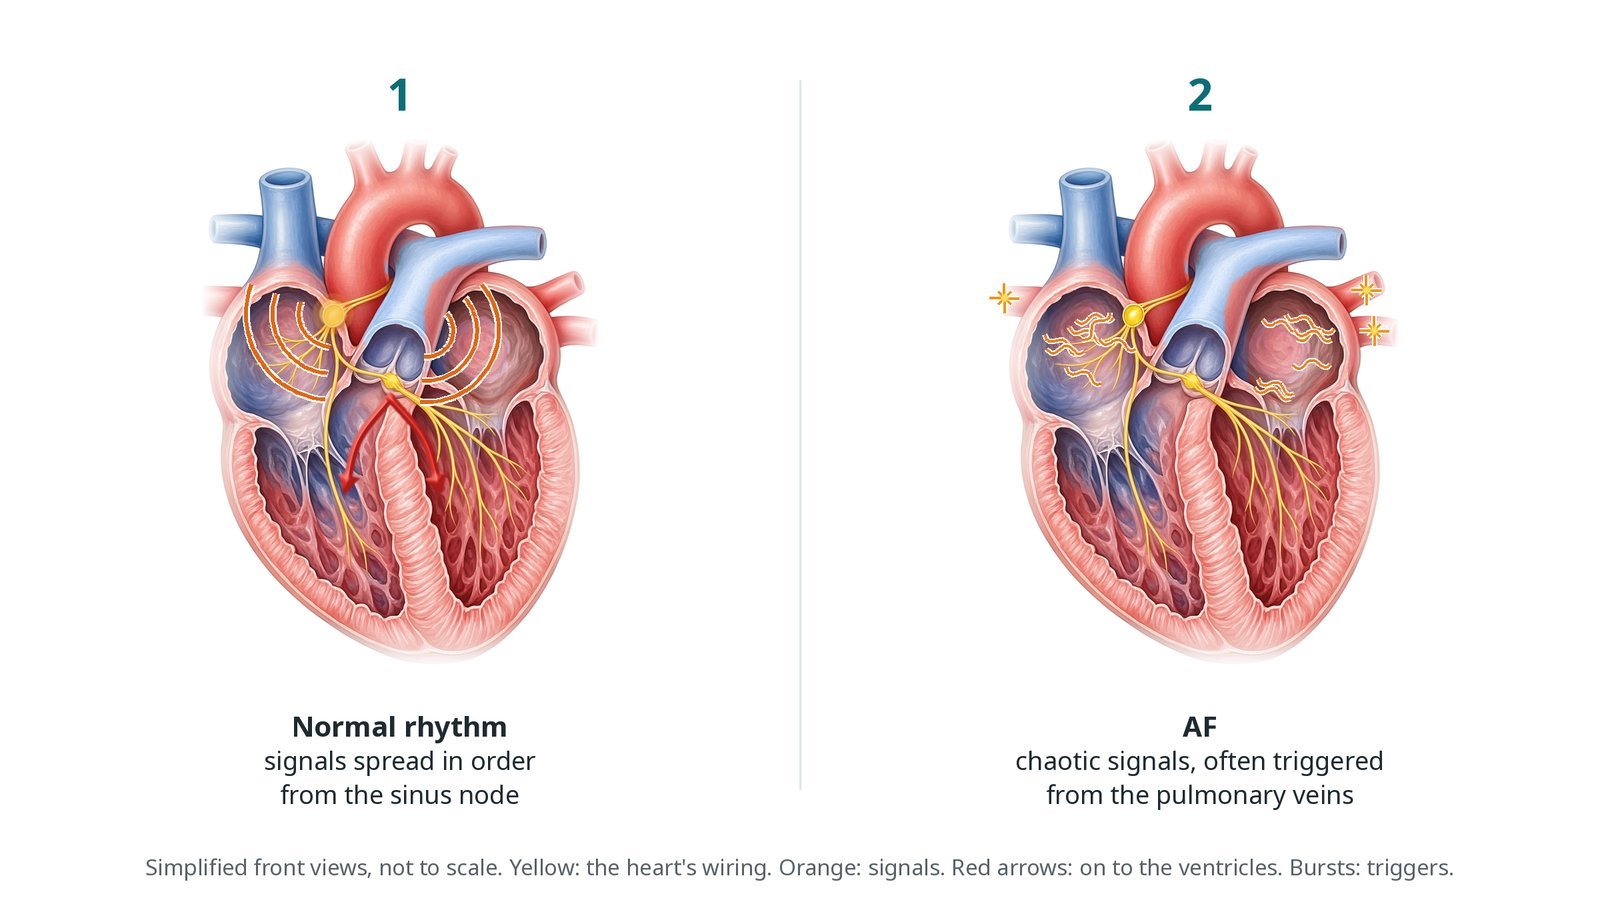
The vein and the bundle around it (the ligament of Marshall) contain muscle fibres and nerves. These can start or keep AF going, and can let signals leak across ablation lines, especially at the mitral isthmus: the strip of atrium between the left inferior pulmonary vein and the mitral valve ring. This area is hard to block with heat from inside the heart alone, partly because the coronary sinus and its blood flow cool the tissue.
Ethanol infused into the vein spreads into the surrounding tissue and makes a lasting lesion from the outside in. Radiofrequency ablation from inside the left atrium then completes the lines, such as a mitral isthmus line, alongside pulmonary vein isolation.
Not everyone has a vein that can be found and entered. If it is too small or absent, the team carries on with ablation alone.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people having:
ablation for persistent AF, as part of a planned set of lesions
a repeat AF ablation after the pulmonary veins have already been isolated
ablation of mitral isthmus (perimitral) flutter, where a mitral line is needed
The decision is made by the operator, based on the rhythm, previous procedures and maps. It is offered in experienced centres.
The decision is made by your heart team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
It is planned as part of an AF or flutter ablation.
Before it, you usually have:
ECGs and often a heart rhythm monitor
blood tests, including kidney function
a review of blood thinners, as per centre protocol
sometimes a CT scan of the heart
gives you a chance to ask questions and give consent
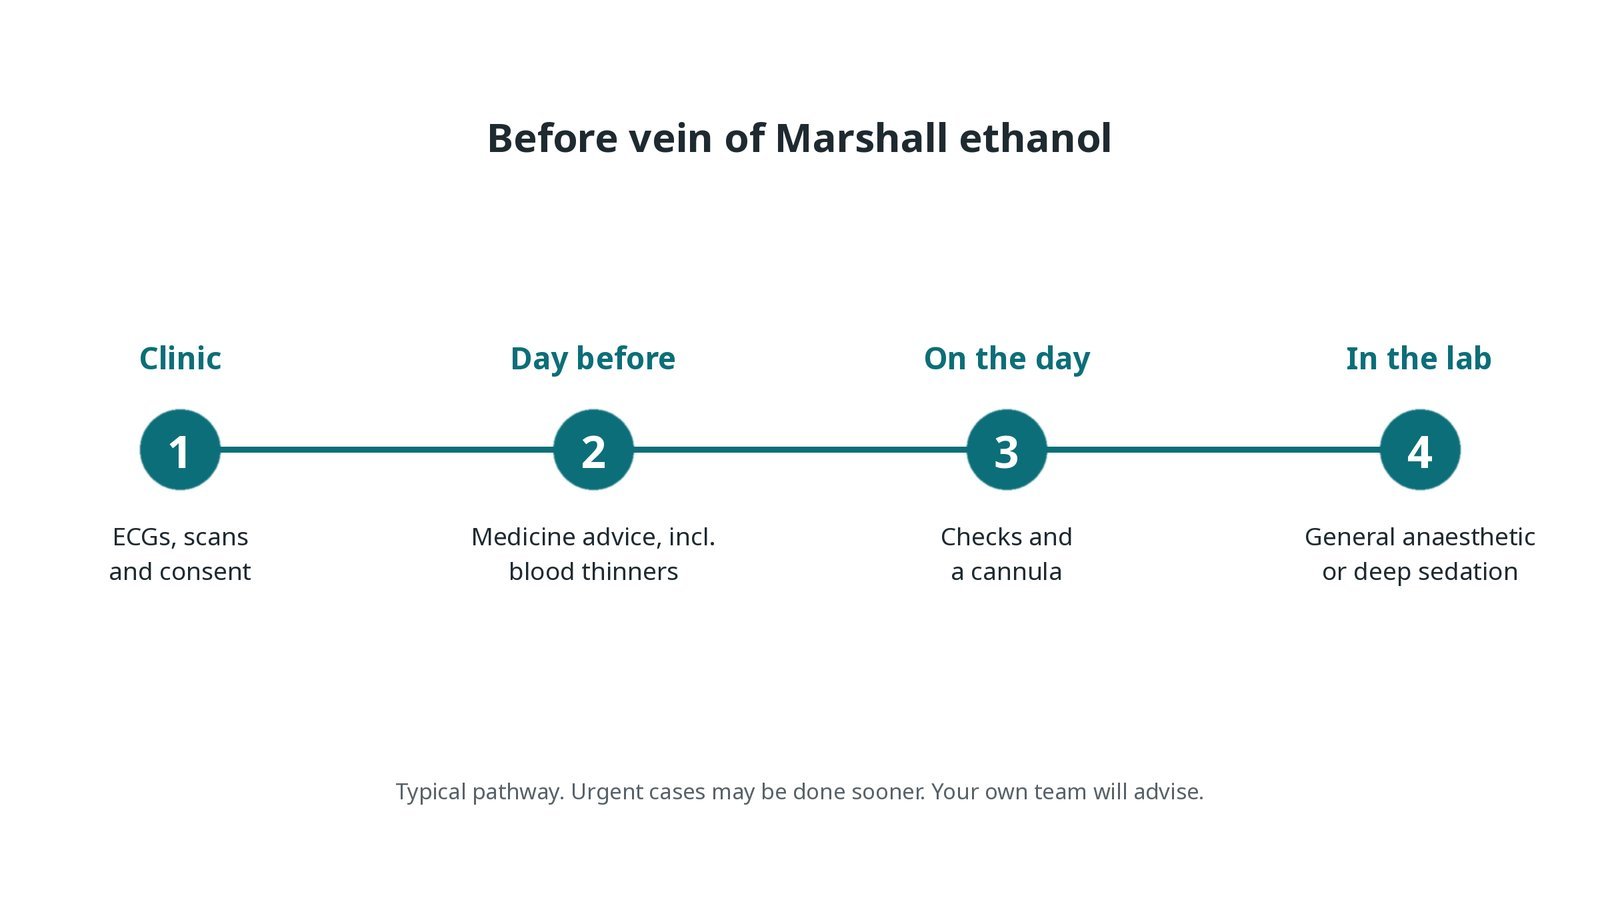
Before vein of Marshall ethanol: ECGs, scans and consent; medicine advice; checks on the day; general anaesthetic or deep sedation in the lab.
Step by step
1. Getting ready
You lie on the X-ray table. A general anaesthetic or deep sedation is used, as per centre protocol. ECG, blood pressure and oxygen are monitored, and an oesophageal temperature probe may be used. External pads are placed.
2. Access
Sheaths go in the femoral vein under ultrasound, sizes per device and operator. A guide catheter is passed into the coronary sinus; some operators use a neck vein for this. A transseptal puncture gives the ablation catheter access to the left atrium, and heparin is given, as per centre protocol.
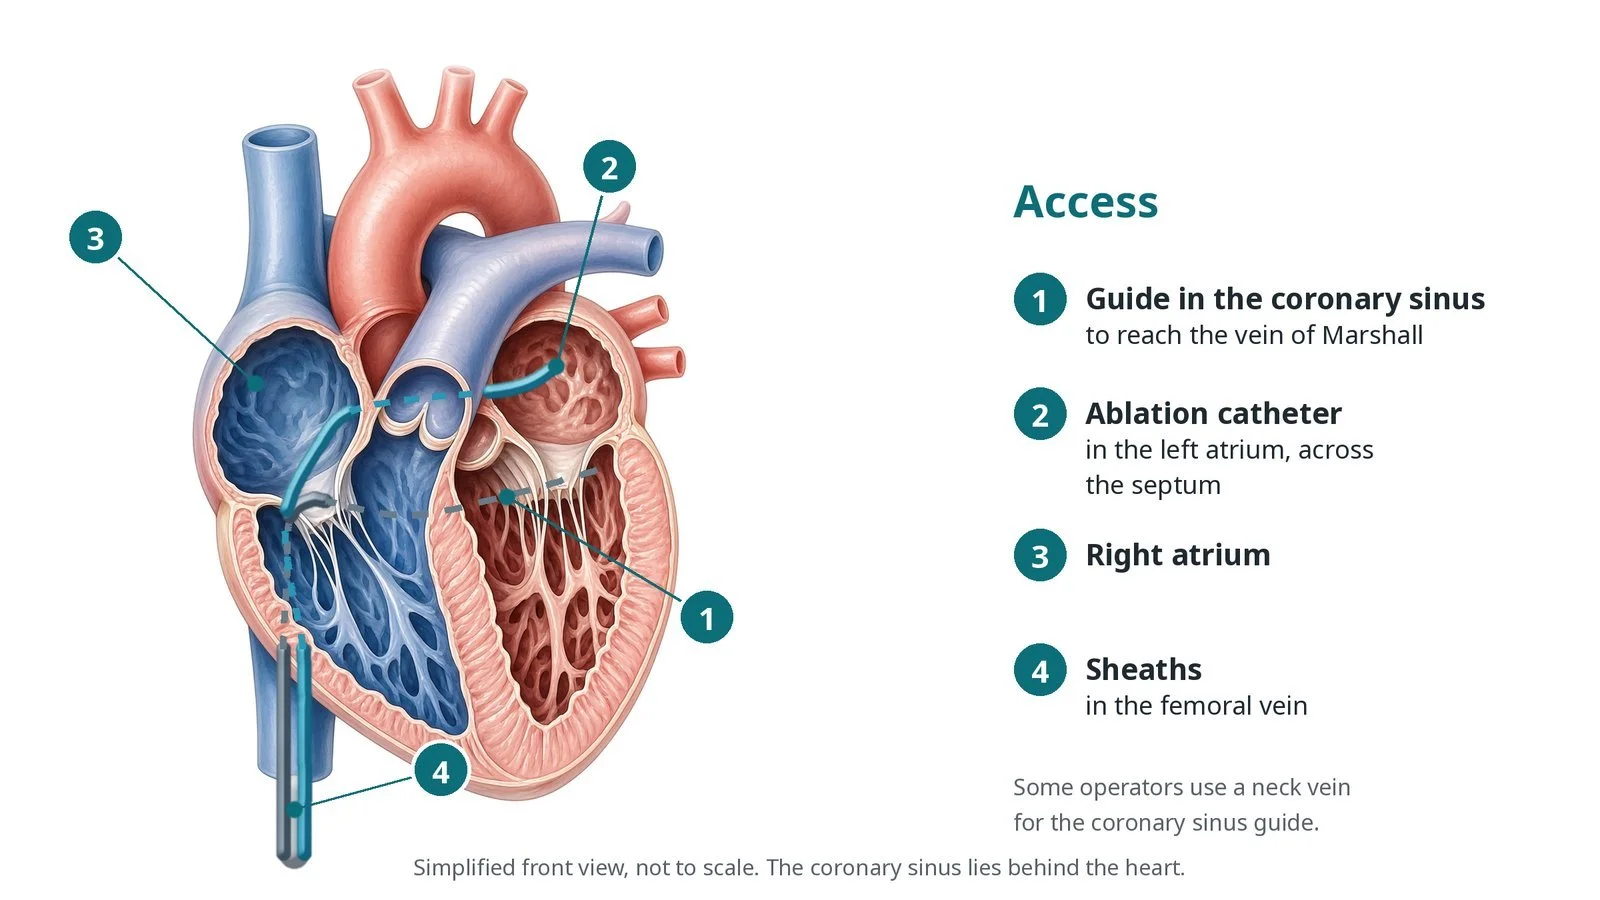
Access: (1) guide in the coronary sinus to reach the vein of Marshall; (2) ablation catheter in the left atrium, across the septum; (3) right atrium; (4) sheaths in the femoral vein.
3. Ethanol infusion
A. Venogram. A balloon-tipped catheter blocks the coronary sinus and contrast is injected to show its branches, including the vein of Marshall.
B. Cannulate. A fine angioplasty-type wire is steered into the vein, and a small over-the-wire balloon is advanced over it.
C. Ethanol. The balloon is inflated to block the vein and ethanol is infused slowly in small amounts, per operator. Contrast injections in between show the treated tissue.
D. RF lines. Radiofrequency ablation from inside the left atrium completes the planned lines, such as the mitral isthmus line, and block across them is checked.
Watch: Falling blood pressure, or contrast spreading outside the vein: think coronary sinus or vein injury and tamponade. Tell the operator and get the echo ready.
4. Finishing
The catheters and sheaths are removed and the groin is closed with pressure or a stitch, per operator. You wake up in recovery.
5. After the procedure
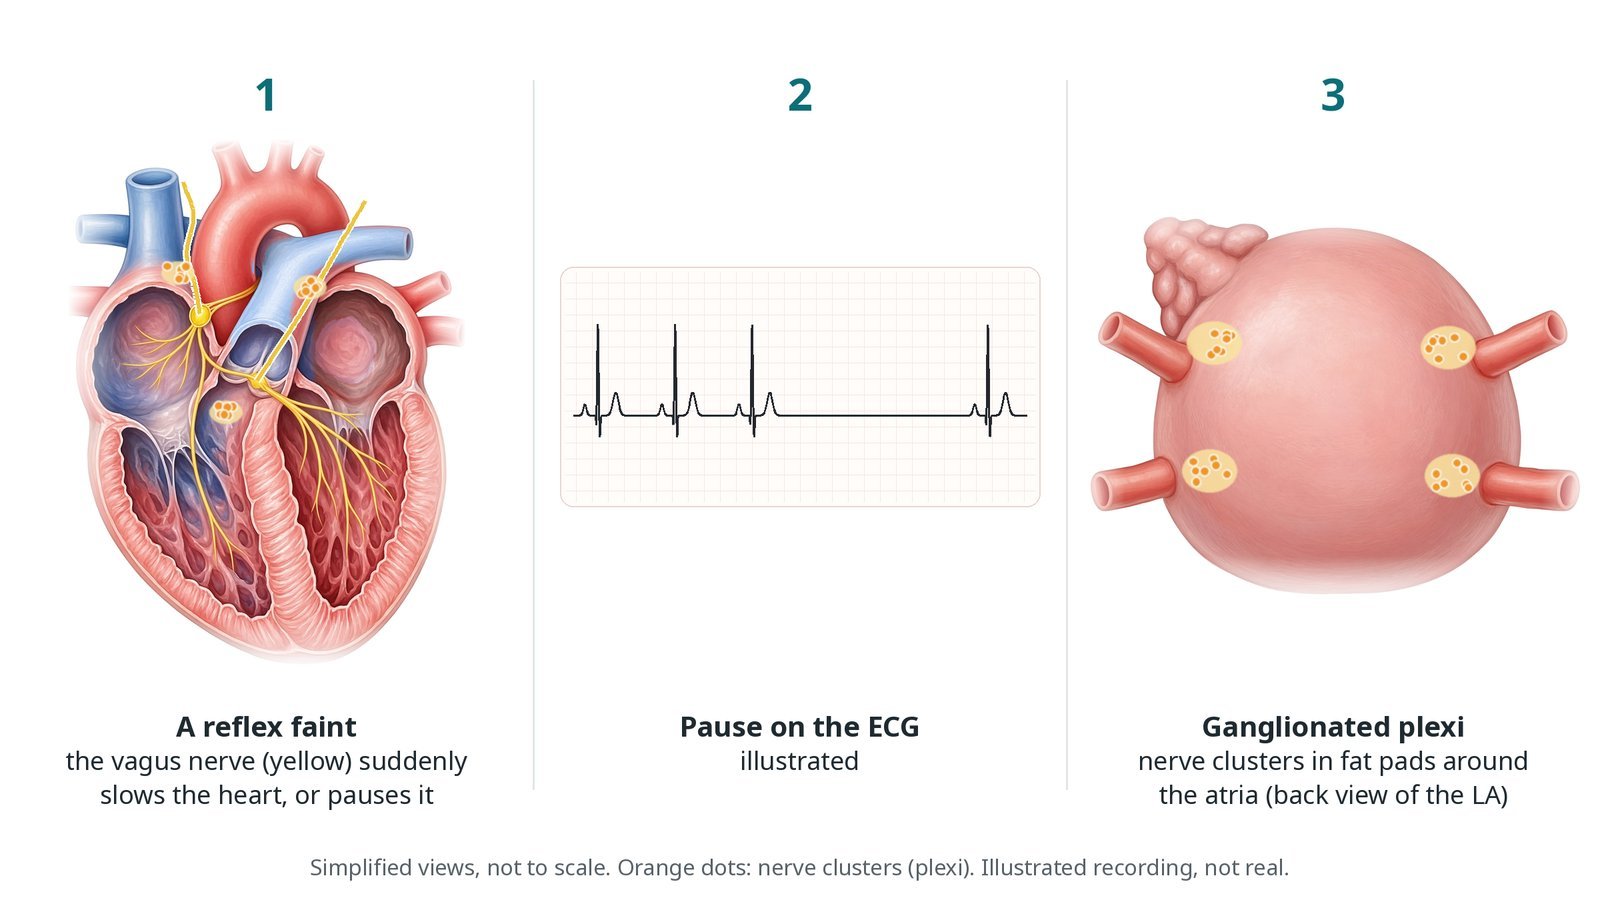
You are monitored for a few hours or overnight. Chest discomfort for a day or two is common. Tell the team if it is severe or worse when lying flat, which can be inflammation around the heart (pericarditis).
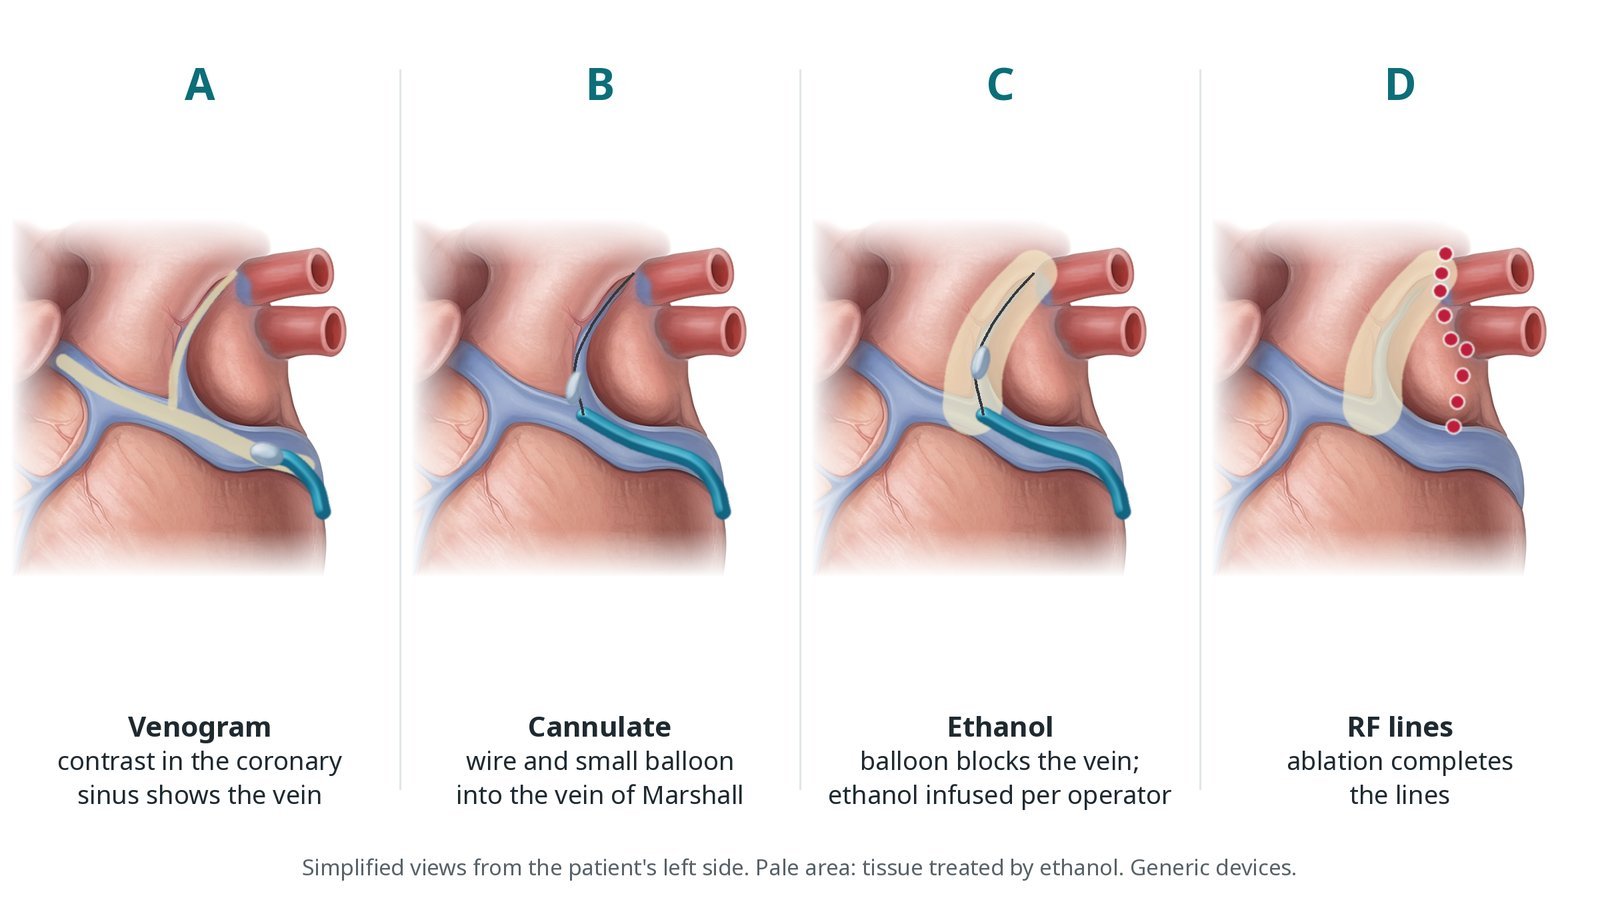
A: a coronary sinus venogram shows the vein. B: a wire and small balloon go into the vein of Marshall. C: the balloon blocks the vein and ethanol is infused. D: RF ablation completes the lines.
Recovery and aftercare
First hours: bed rest while the groin settles; checks of the groin, rhythm and blood pressure, as per centre protocol.
Going home: often the same or next day.
Activity: avoid heavy lifting and strenuous exercise for about a week.
Medicines: keep taking blood thinners and rhythm medicines exactly as advised; pain relief for chest discomfort if needed.
Driving: DVLA rules depend on the rhythm and your symptoms; ask your team.
Follow-up: clinic review, often with an ECG or heart monitor, after a healing period of a few months.
Call 999 if you have severe or worsening chest pain, breathlessness, fainting, signs of a stroke, or heavy bleeding at the groin.
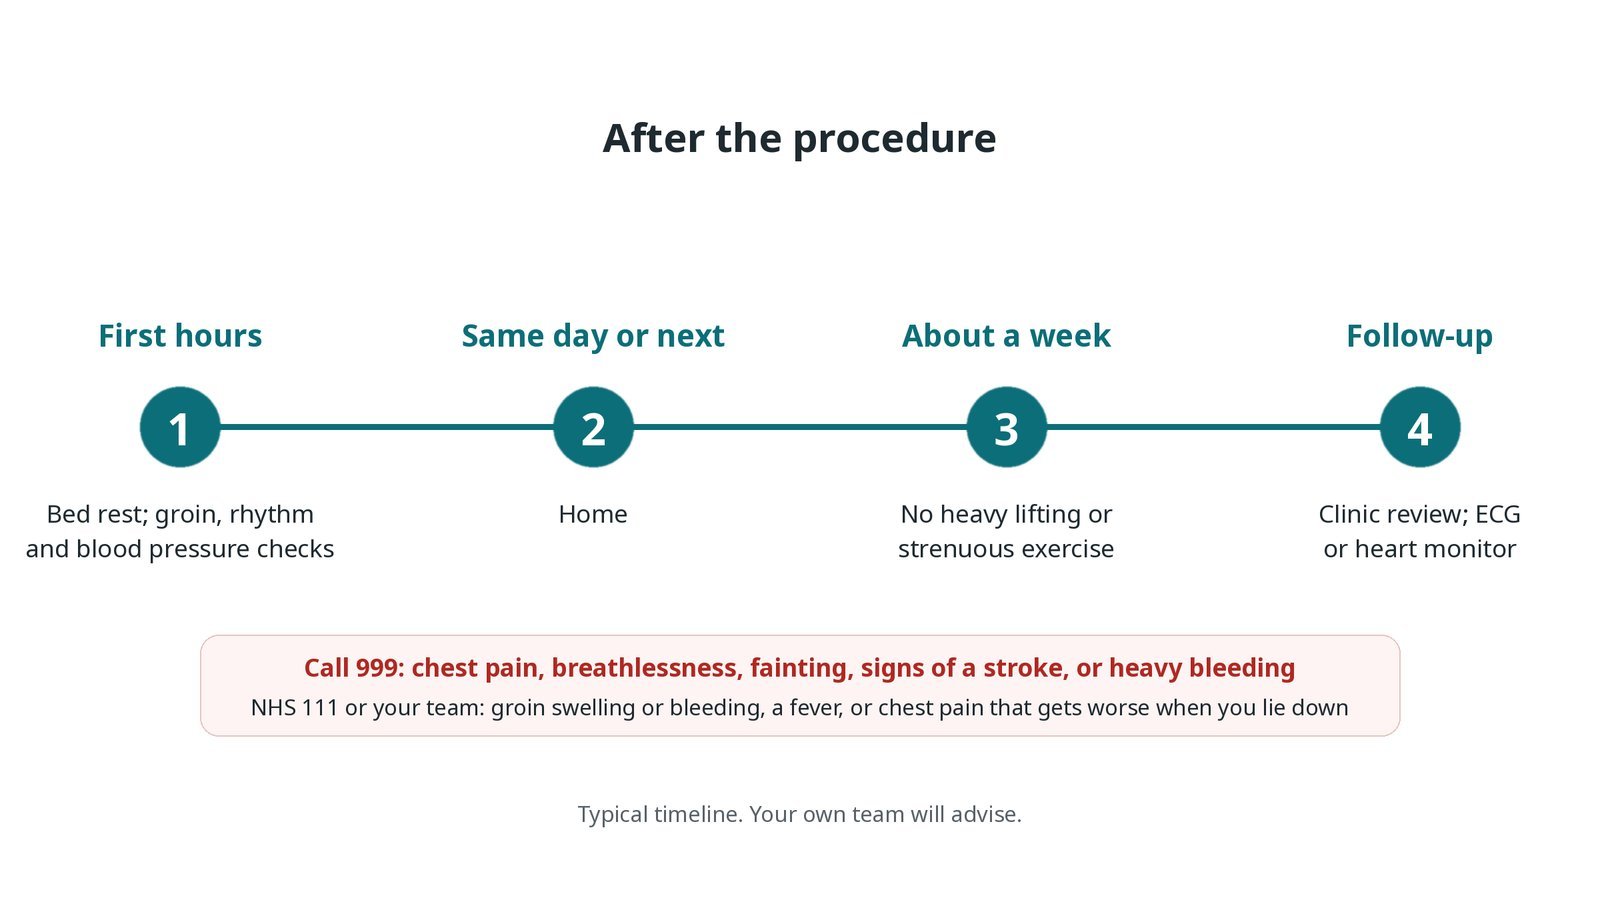
After the procedure: (1) bed rest and checks; (2) home the same day or next morning; (3) no heavy lifting for about a week; (4) clinic review with an ECG or heart monitor.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
Bruising or bleeding at the groin
Fluid or bleeding around the heart (tamponade) (uncommon)
Injury to the coronary sinus or the vein of Marshall (uncommon)
Inflammation around the heart (pericarditis) causing chest pain (uncommon)
Stroke or a clot (rare)
Ethanol affecting nearby tissue outside the target area (rare)
AF or flutter coming back: Some people need a repeat procedure.
Cath lab kit list (printable)
Barts example kit list
An example from one UK centre, written generically. Every lab has its own protocol, and sizes and doses vary.
femoral venous sheaths, sizes per device and operator
ultrasound for vein access
coronary sinus guide catheter, per operator
balloon-tipped catheter for the coronary sinus venogram
angioplasty guidewire and small over-the-wire balloon, per operator
dehydrated alcohol (ethanol) and labelled syringes, as per centre protocol
contrast
transseptal needle and steerable sheath
ablation catheter and radiofrequency generator
3D mapping system and skin patches
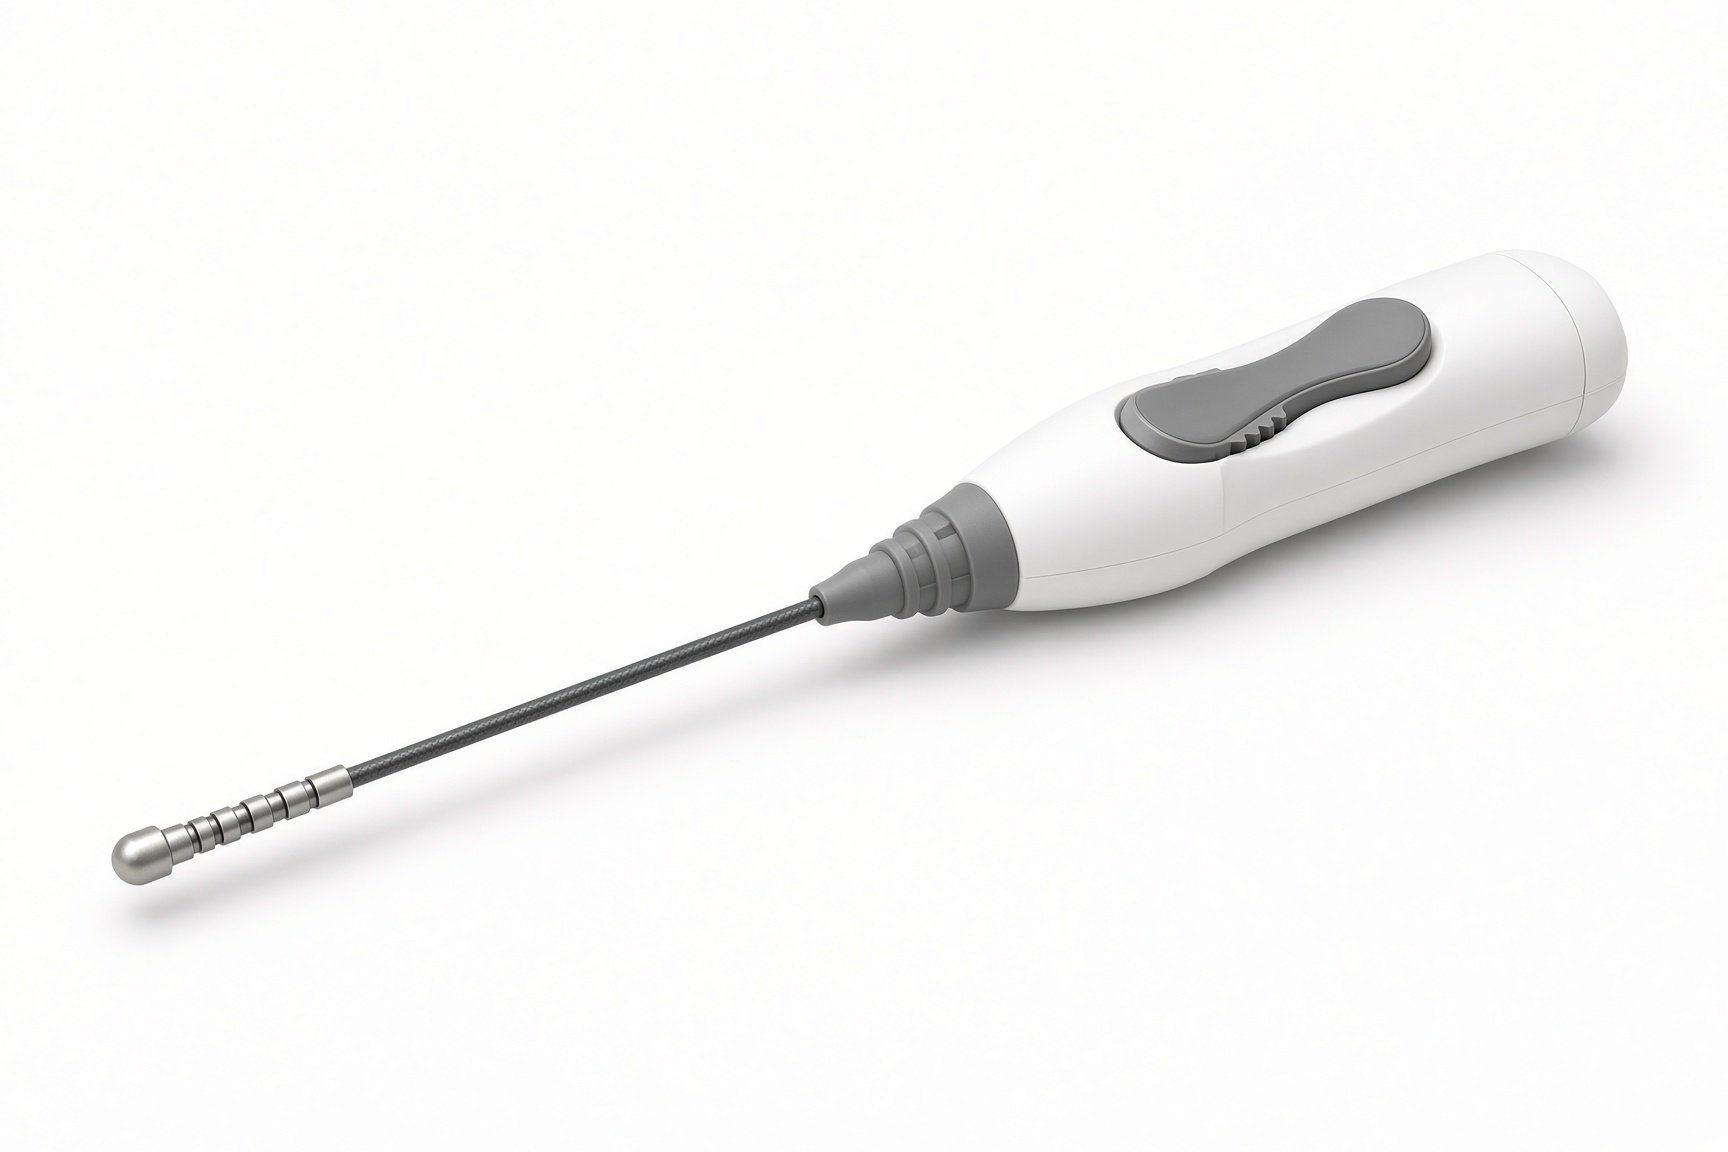
Ablation catheter.
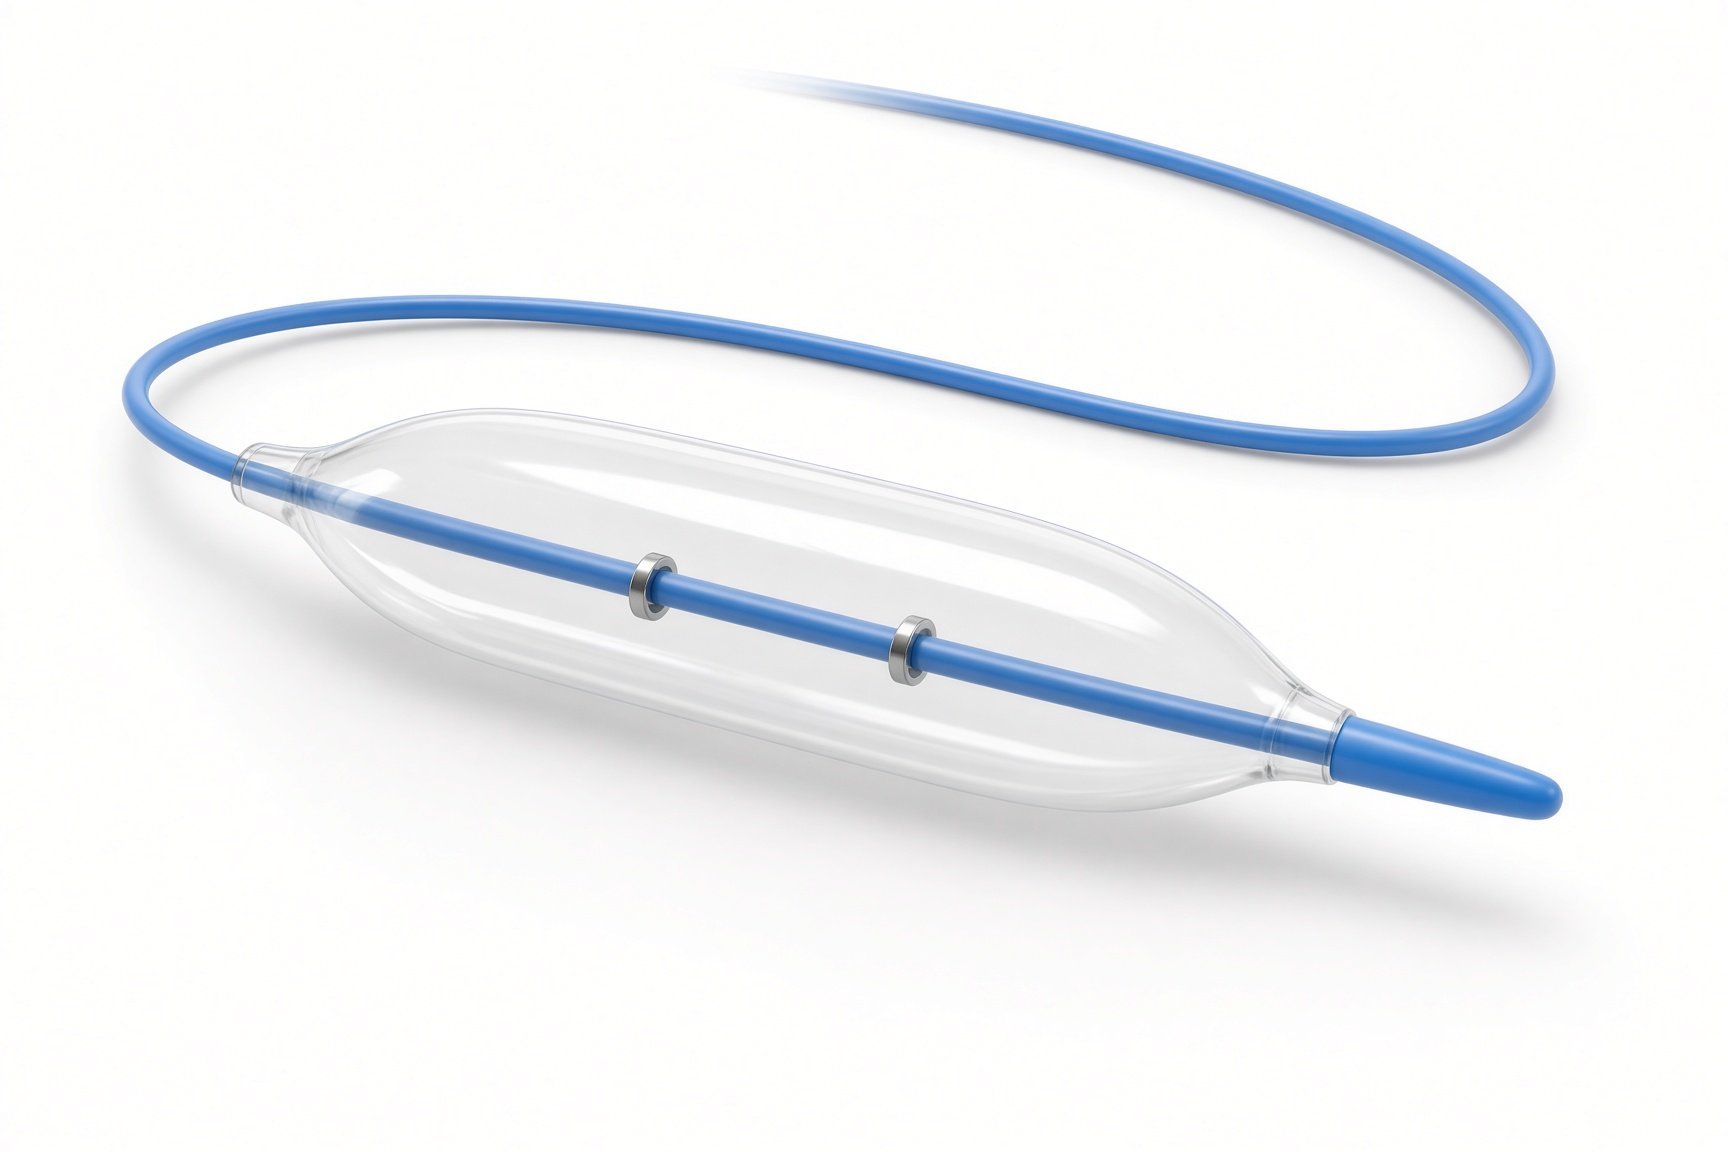
Over-the-wire balloon catheter.

Over-the-wire balloon catheter.
3D mapping system.
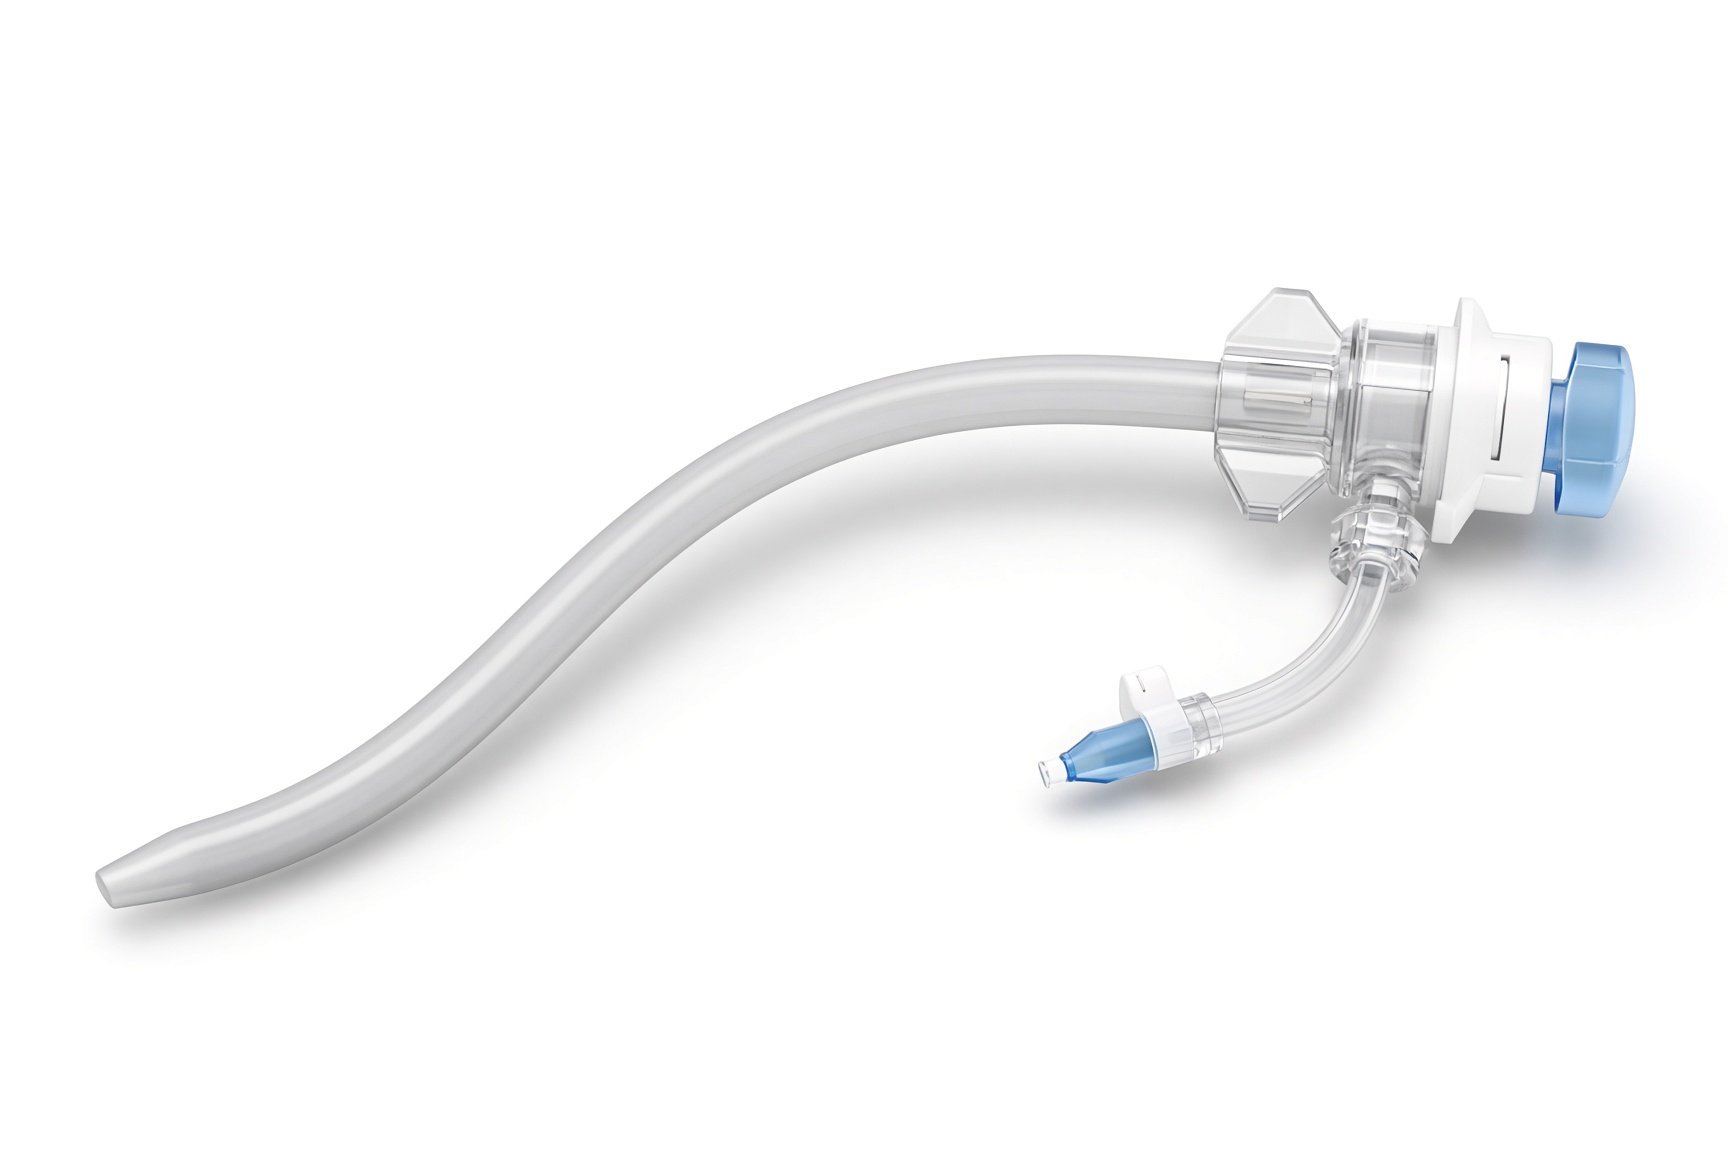
Coronary sinus guide catheter.
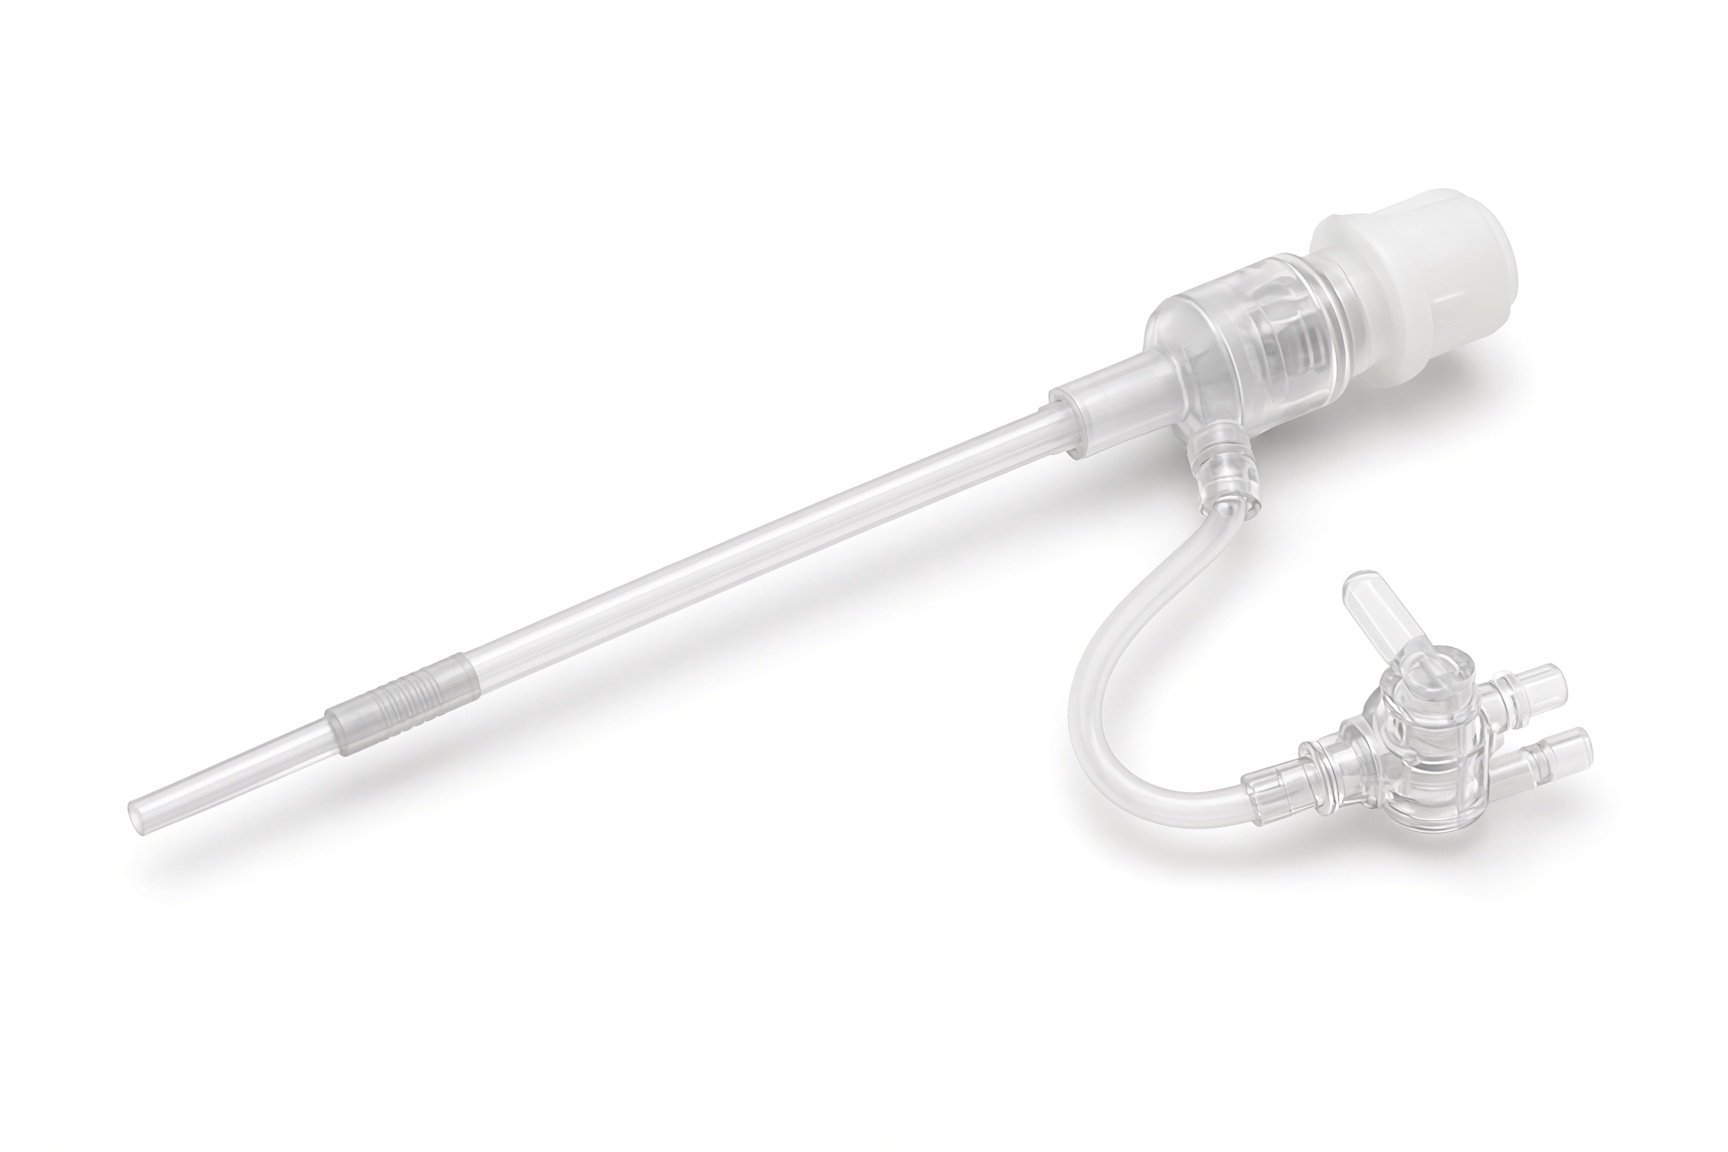
Steerable transseptal sheath.
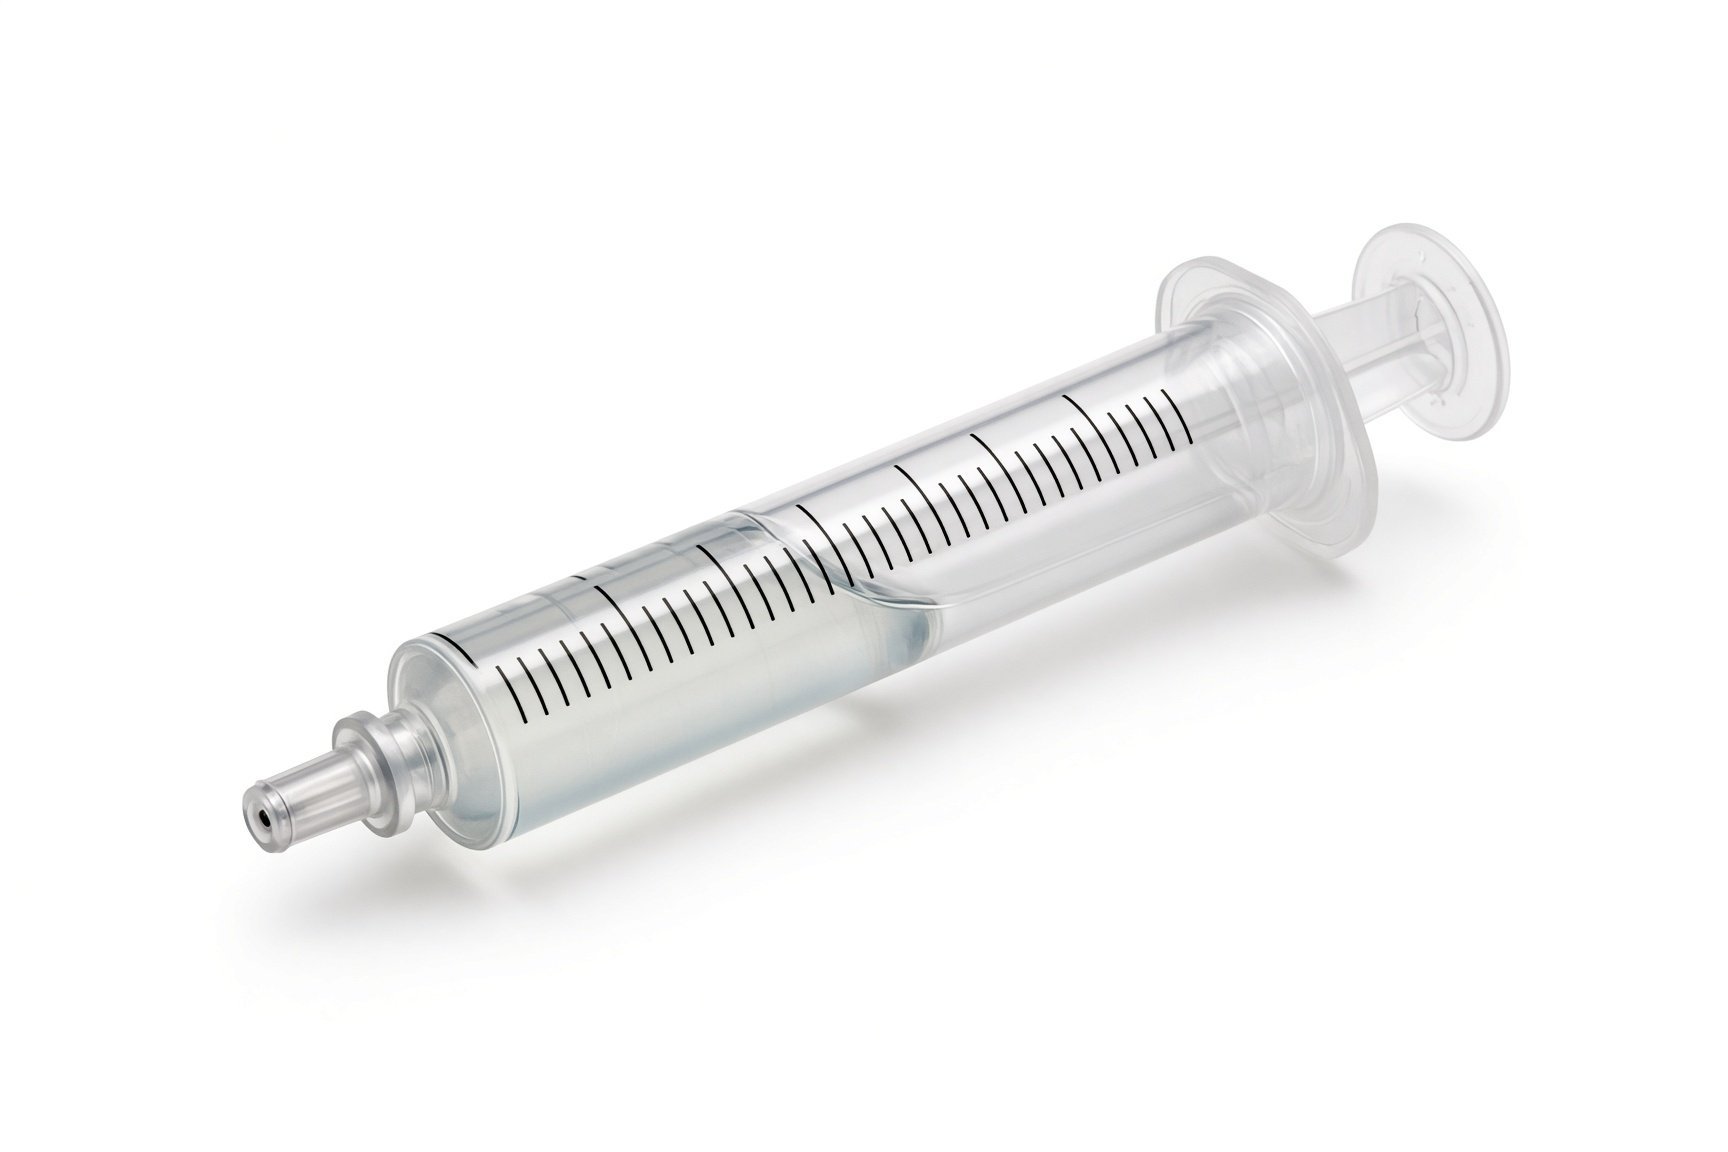
Contrast and syringes.

Dehydrated alcohol.

Angioplasty guidewire.
Procedural steps (Barts example)
Getting ready
Access
Ethanol infusion
Finishing
After the procedure
First time in the cath lab?
Know your syringes. Ethanol, contrast and saline can look alike. Label every syringe and keep the ethanol separate.
Coronary sinus first. Most of the work depends on a stable coronary sinus guide; have the different guide shapes ready.
Be patient. Finding and entering a small vein can take time, and sometimes it cannot be done. That is not a failure of the case.
Watch for pericarditis later. Chest pain that is worse lying flat after the case may be inflammation; report it.
Label the ethanol syringe clearly and keep it apart from the saline and contrast syringes on the trolley.
FAQ
Is the alcohol dangerous?
A small amount is given slowly into a blocked vein, so it stays in the target area. The amount is decided by the operator.
Why not just use heat?
The tissue around this vein is hard to reach from inside the heart. Treating it from the vein helps the lines last.
What if the vein cannot be found?
Some people do not have a suitable vein. The ablation then carries on with heat alone.
Will I feel it?
You will have a general anaesthetic or deep sedation. Some people have chest discomfort for a day or two.
Related Cath Lab 101 guides
Sources
All checked on 12 November 2026. Each page's own date is shown where it gives one.
Valderrábano M, et al. Effect of catheter ablation with vein of Marshall ethanol infusion vs catheter ablation alone on persistent atrial fibrillation: the VENUS randomized clinical trial. JAMA 2020.
Van Gelder IC, et al. 2024 ESC Guidelines for the management of atrial fibrillation. Eur Heart J 2024;45(36):3314–3414. PubMed 39210723
StatPearls (NCBI Bookshelf), search: atrial fibrillation. ncbi.nlm.nih.gov/books
Disclaimer
Education only. This page is for general education for healthcare students, cath lab staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, heart team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a heart emergency, call 999.
Disclosure: I work for a company that makes a device used in this procedure. This page is independent education, isn't sponsored or reviewed by any company, and doesn't recommend any product.
All diagrams on this page are original illustrations created for rodnieoro.com.