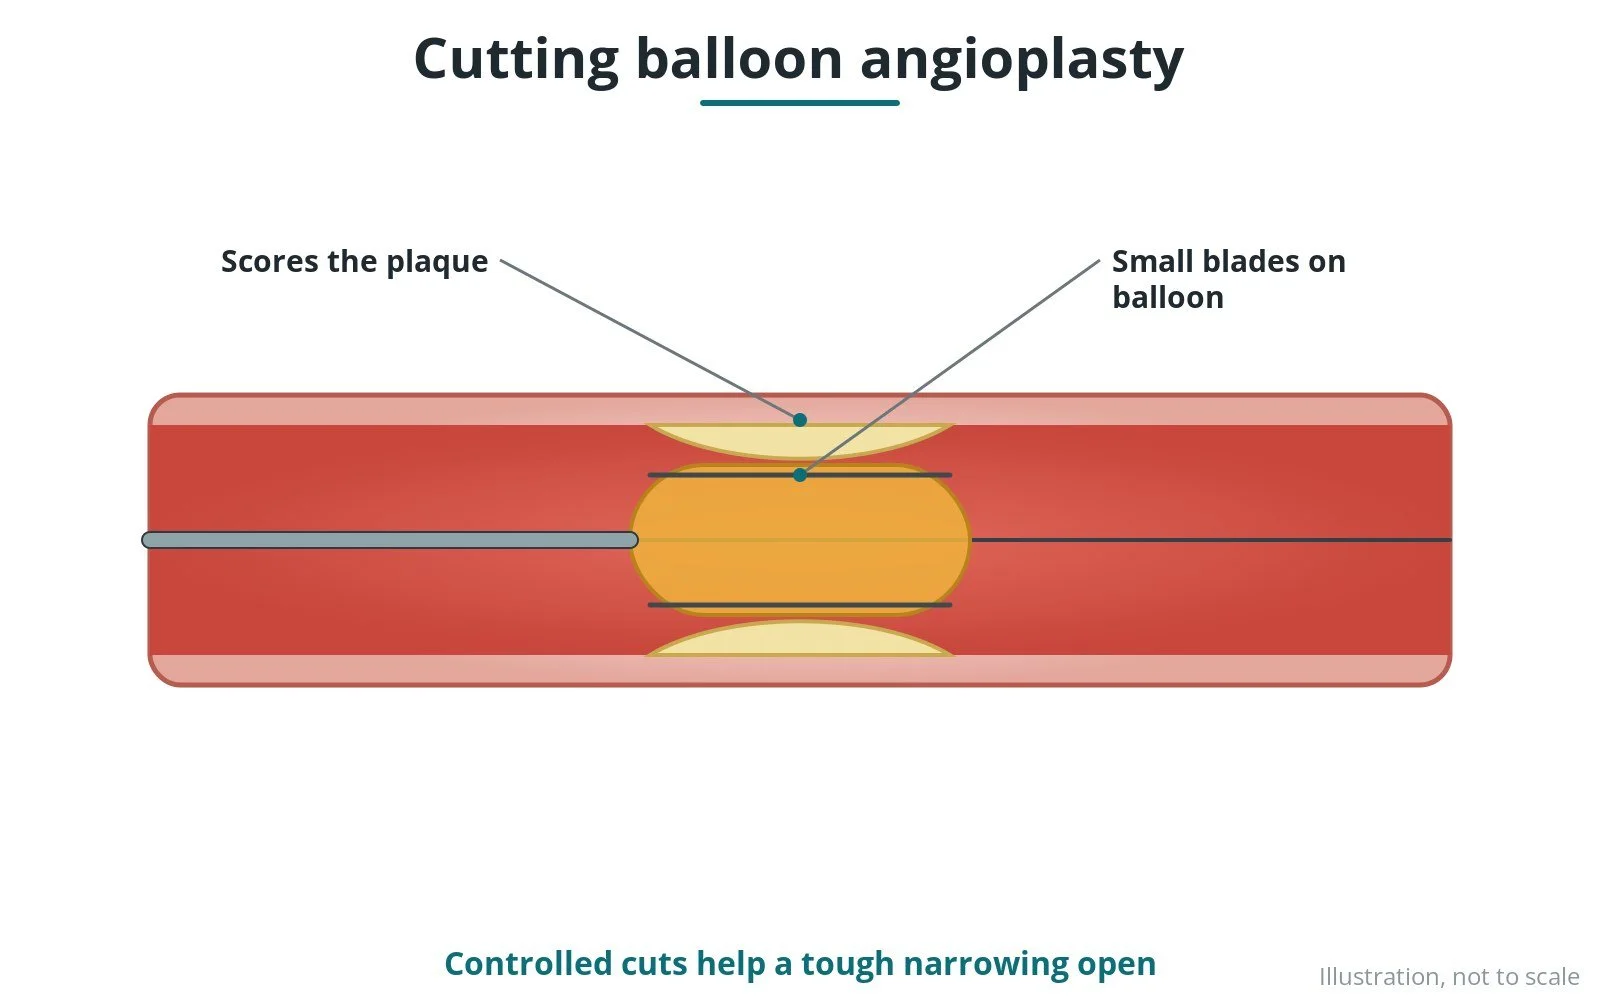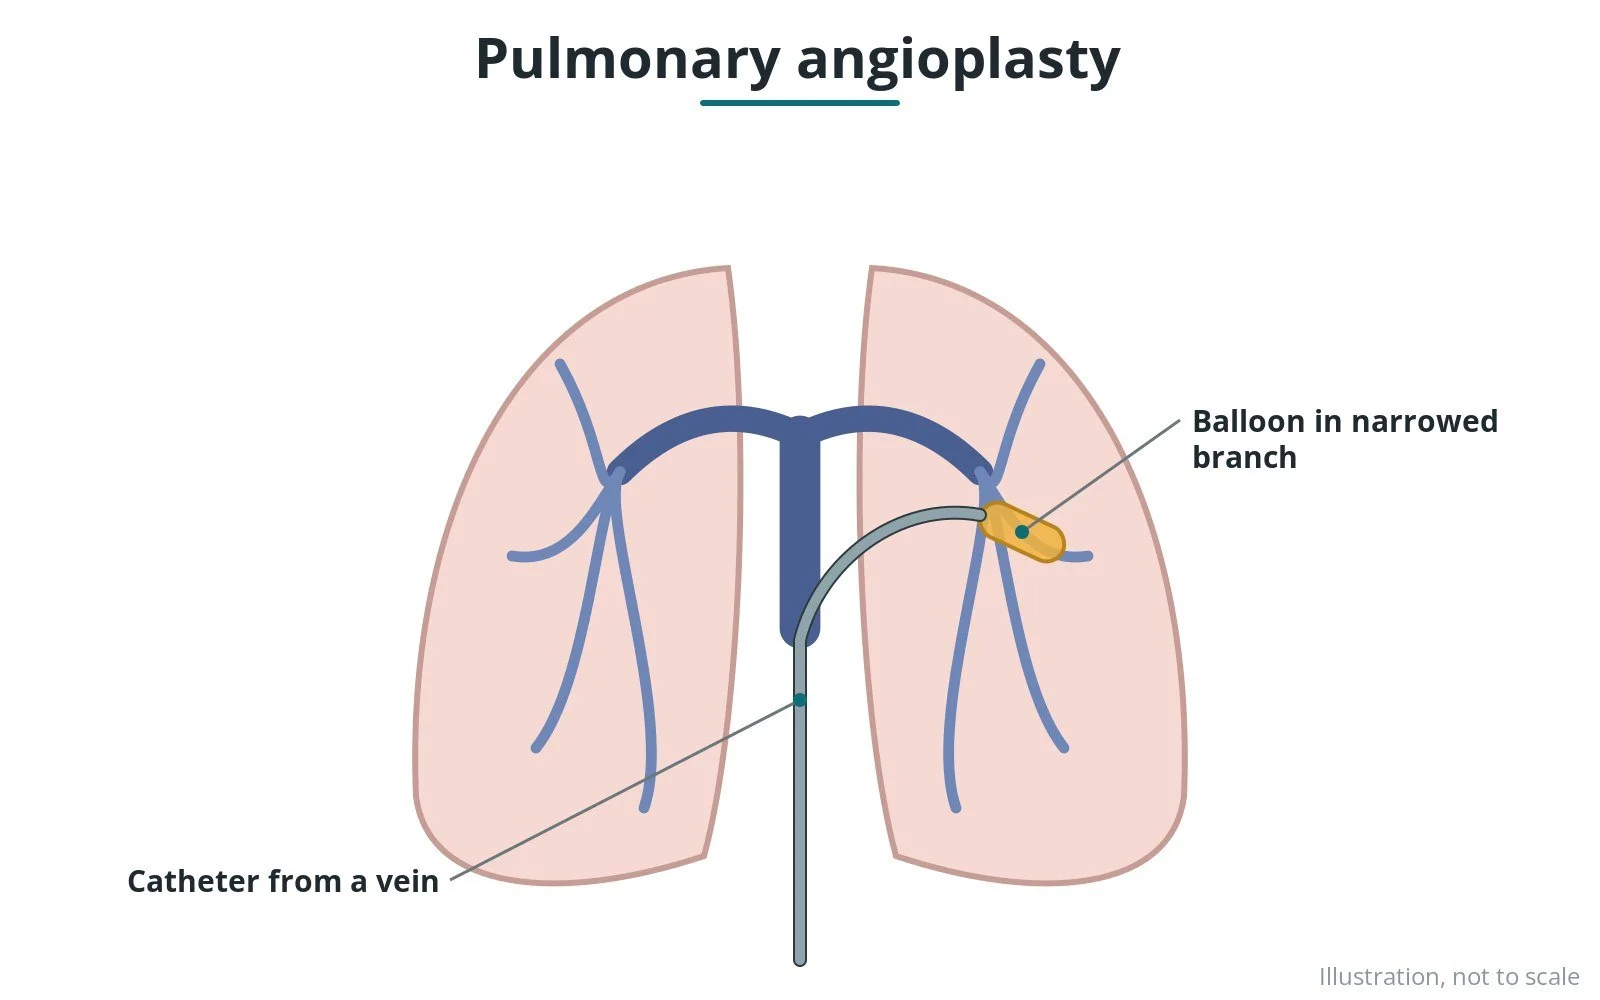
Pulmonary artery balloon angioplasty: a Cath Lab 101 guide
Reviewed by Rodnie Oro, cath lab charge nurse · Last reviewed: October 2026 · Education only, not medical advice
Pulmonary artery angioplasty in one minute
What it is: widening narrowed arteries in the lungs with a balloon, sometimes with a stent, through a catheter from a vein.
Who it is for: people with chronic clots in the lung arteries (CTEPH) who are not suitable for surgery, and people with congenital narrowings of the pulmonary arteries.
Main risks: injury to a lung artery causing coughing up blood, fluid on the lung in the treated area, rhythm problems and bruising at the access site.
Usually: in a specialist centre, under local anaesthetic or general anaesthetic, often in several sessions.
On this page: What is pulmonary artery balloon angioplasty? · Who is it for? · When is it done? · Step by step · Recovery · Risks · Kit list · First time in the lab? · FAQ
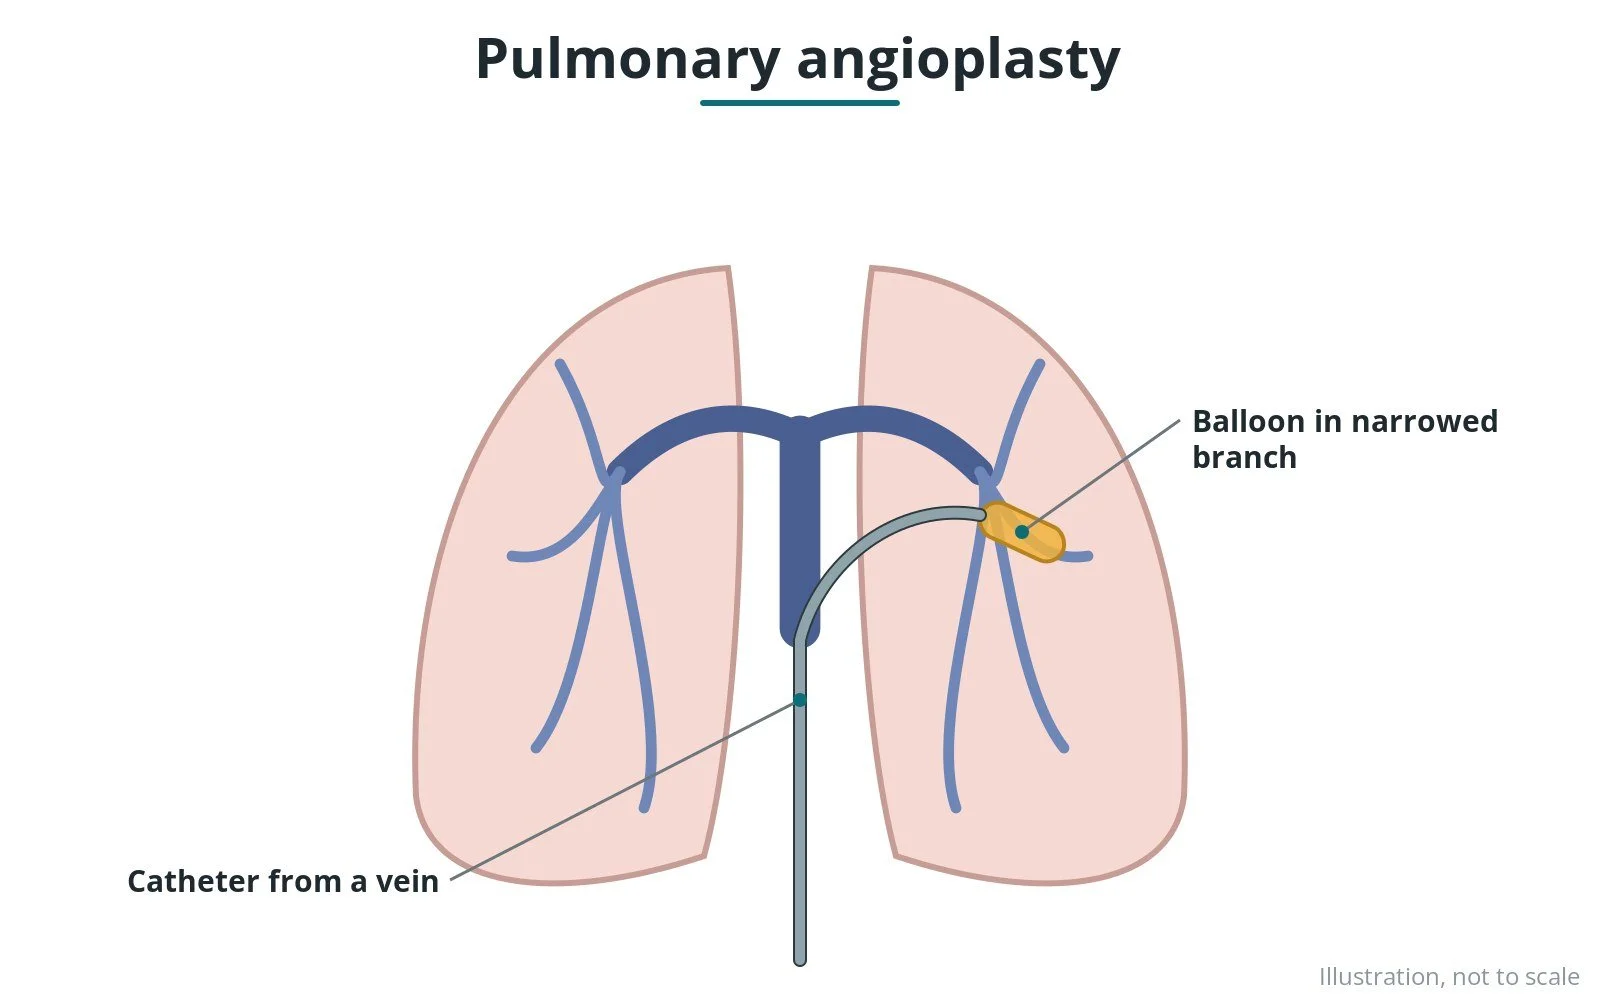
What is pulmonary artery balloon angioplasty?
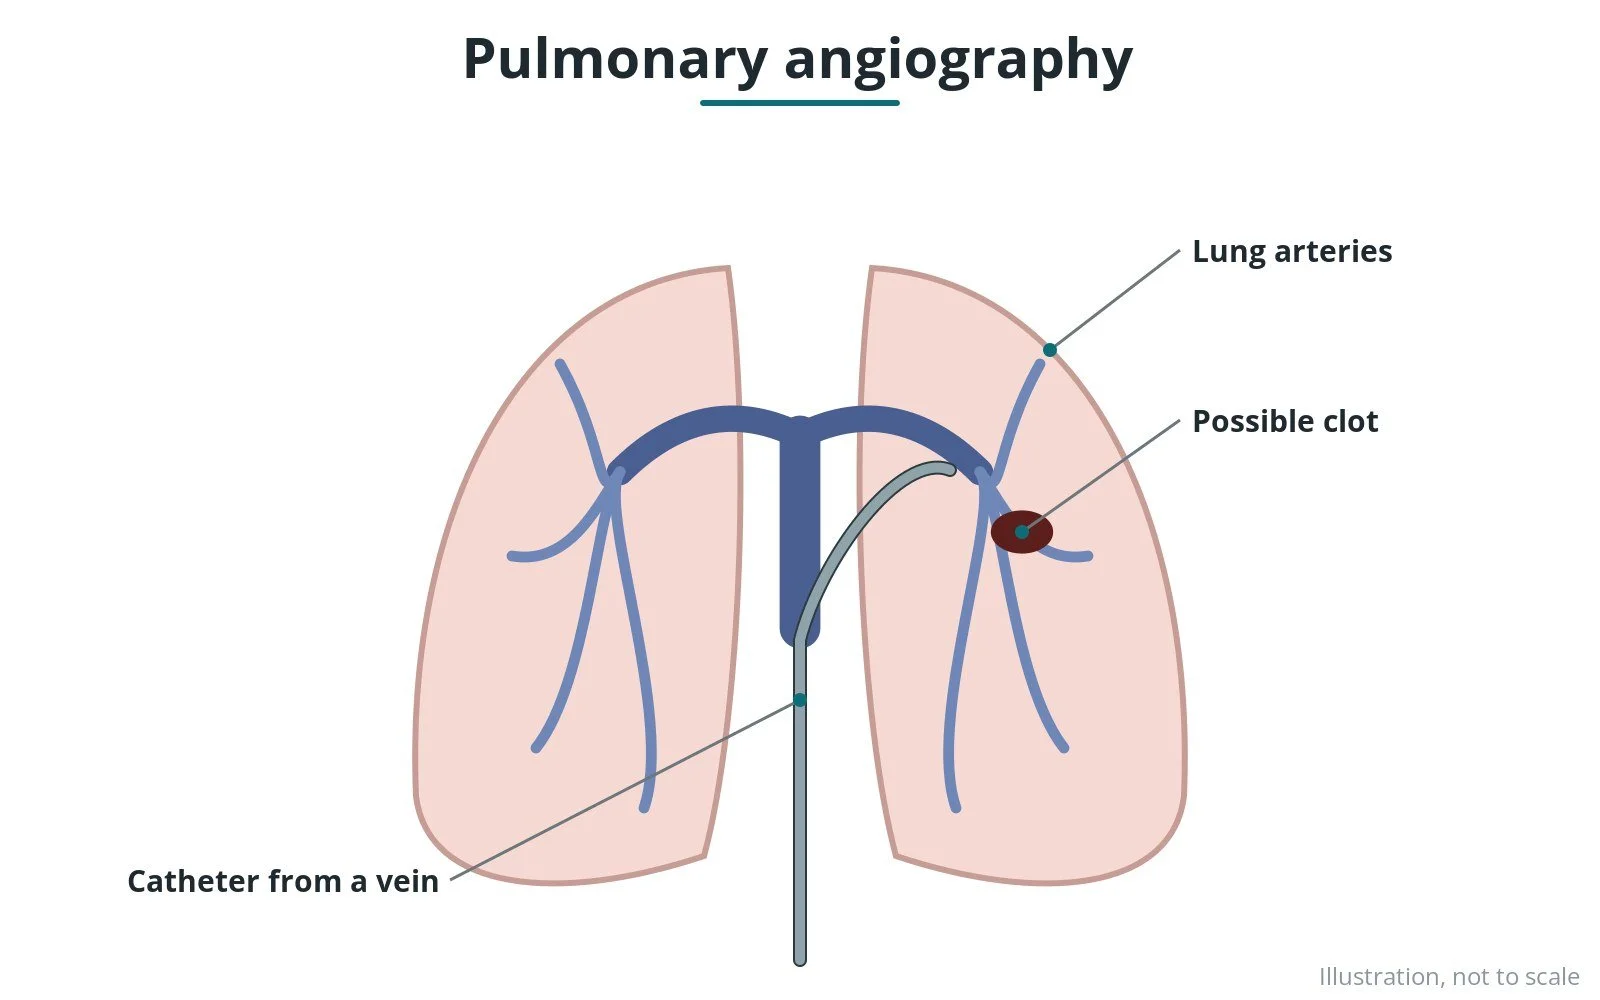
The pulmonary arteries carry blood to the lungs. Narrowings raise the pressure in the lungs and strain the right ventricle.
- in CTEPH, old clots leave webs and narrowings in small lung arteries; balloon pulmonary angioplasty (BPA) treats a few areas at a time, over several sessions
- in congenital heart disease, narrowings of the main or branch pulmonary arteries may be ballooned and often stented
This is different from the pulmonary vein venoplasty guide, which treats veins.
New to the acronyms? See the Cath Lab Abbreviations A–Z.
Who is it for?
It may be considered for people with:
- CTEPH not suitable for surgery, or with remaining disease after surgery
- congenital branch pulmonary artery narrowings
- narrowings after earlier heart surgery
The decision is made by your heart team, who will talk through the reasons, the alternatives and the risks with you.
When is it done?
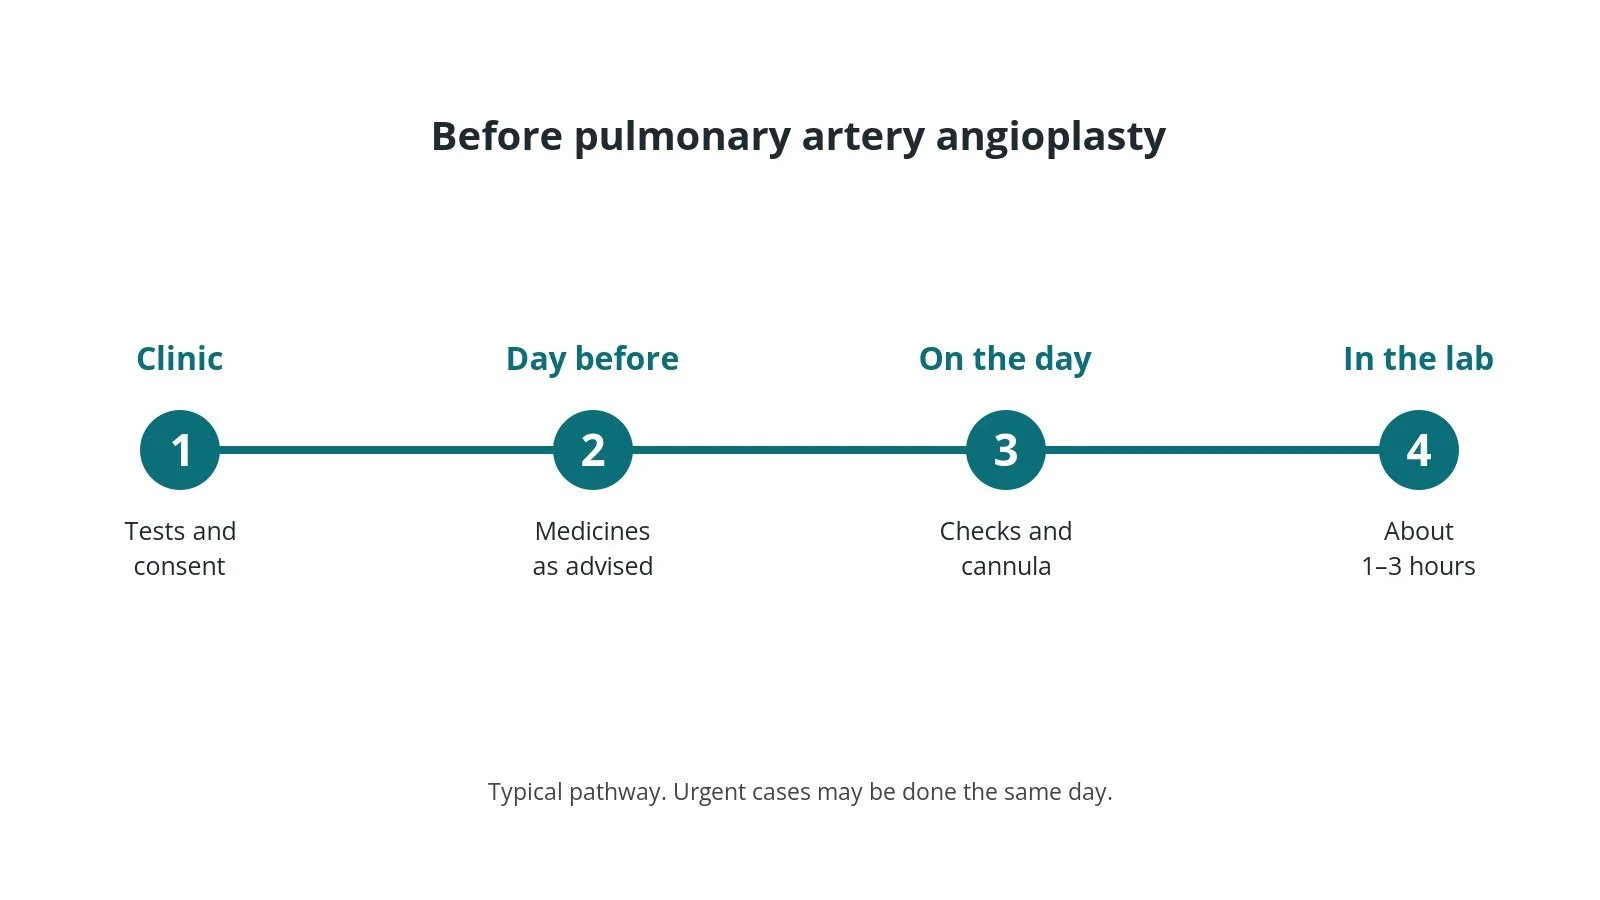
It can be planned in advance or done urgently. Before it, you usually have:
- blood tests, including kidney function and blood count
- an ECG, and often an echo or other scan
- a review of your medicines, especially blood thinners and diabetes medicines, as per centre protocol
- a chance to ask questions and give consent
Step by step
1. Getting ready
You lie on the X-ray table. ECG, blood pressure and oxygen levels are monitored. The skin over the access site is cleaned and numbed with local anaesthetic; some people also have light sedation, as per centre protocol.
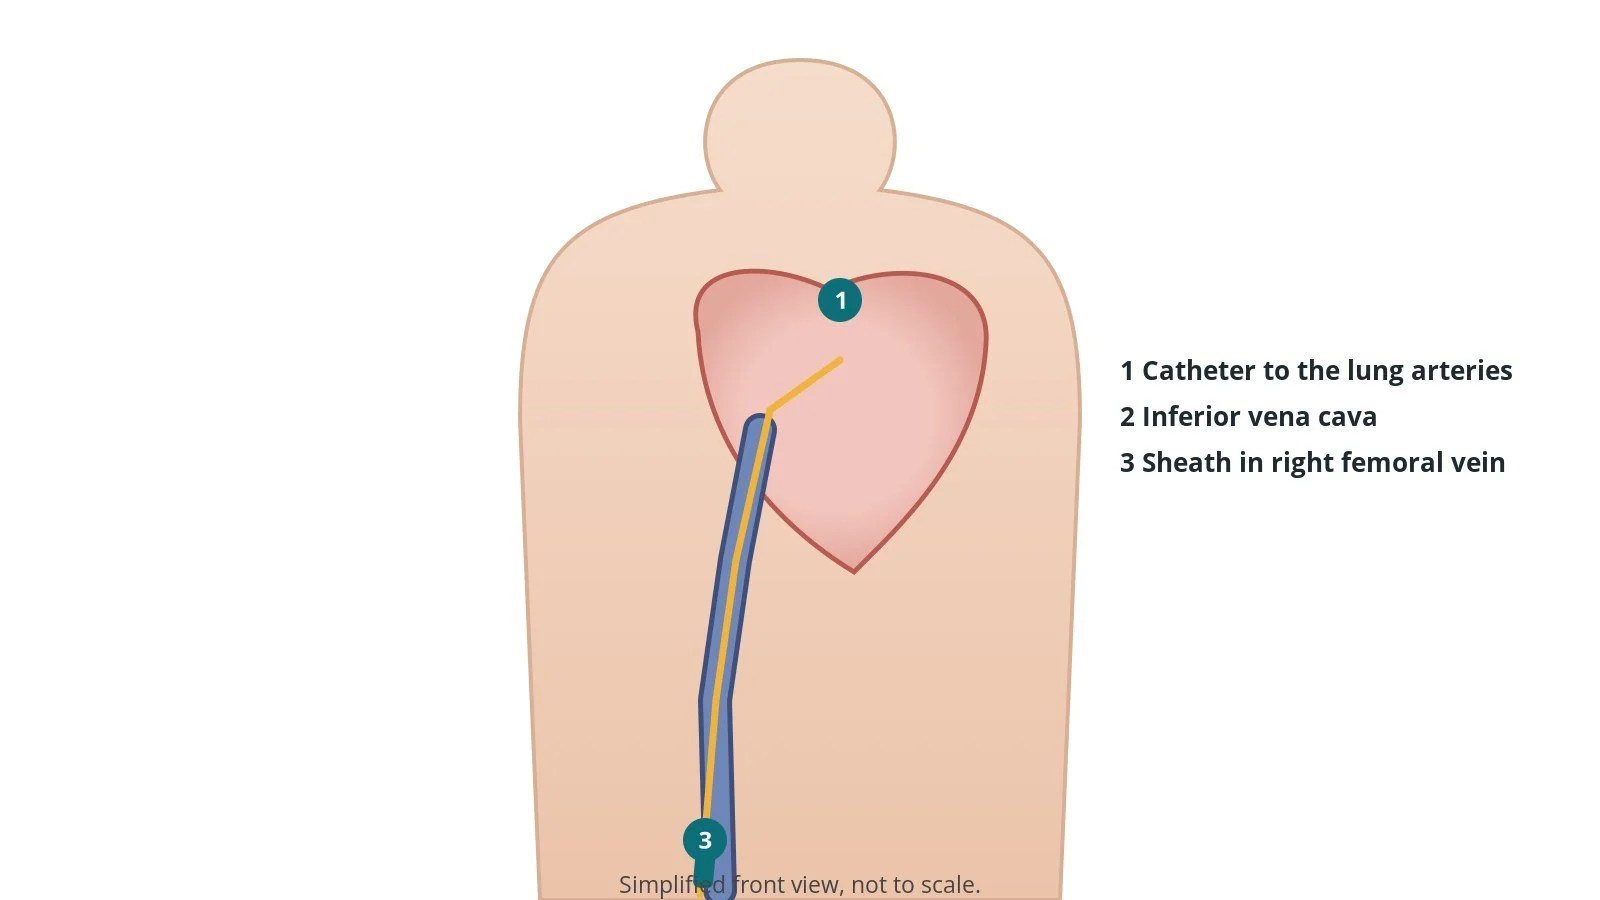
2. Access
A sheath is placed in the femoral vein (or jugular vein), sizes per device and operator. Right heart pressures are measured, and heparin given as per centre protocol.
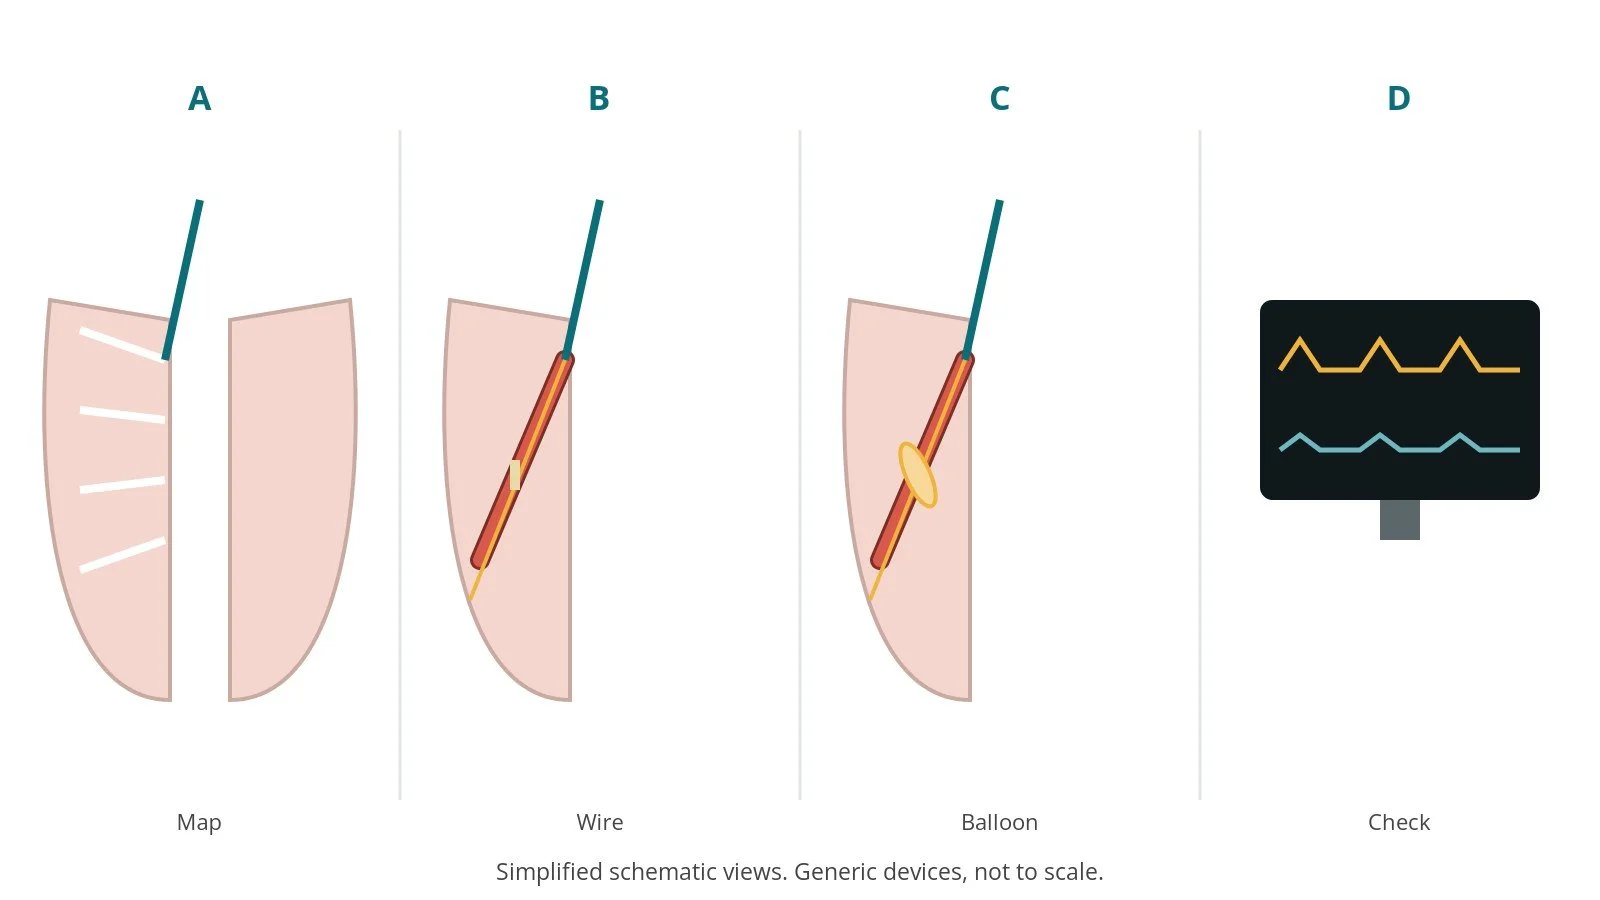
3. Angioplasty
- A. Map. Pulmonary angiograms show the narrowed vessels.
- B. Wire. A guidewire crosses the narrowing.
- C. Balloon. A balloon is inflated, size per device and operator.
- D. Check. Angiograms and pressures check the result; a stent may be placed.
4. Finishing
The catheters and sheath are removed and pressure applied.
Recovery and aftercare
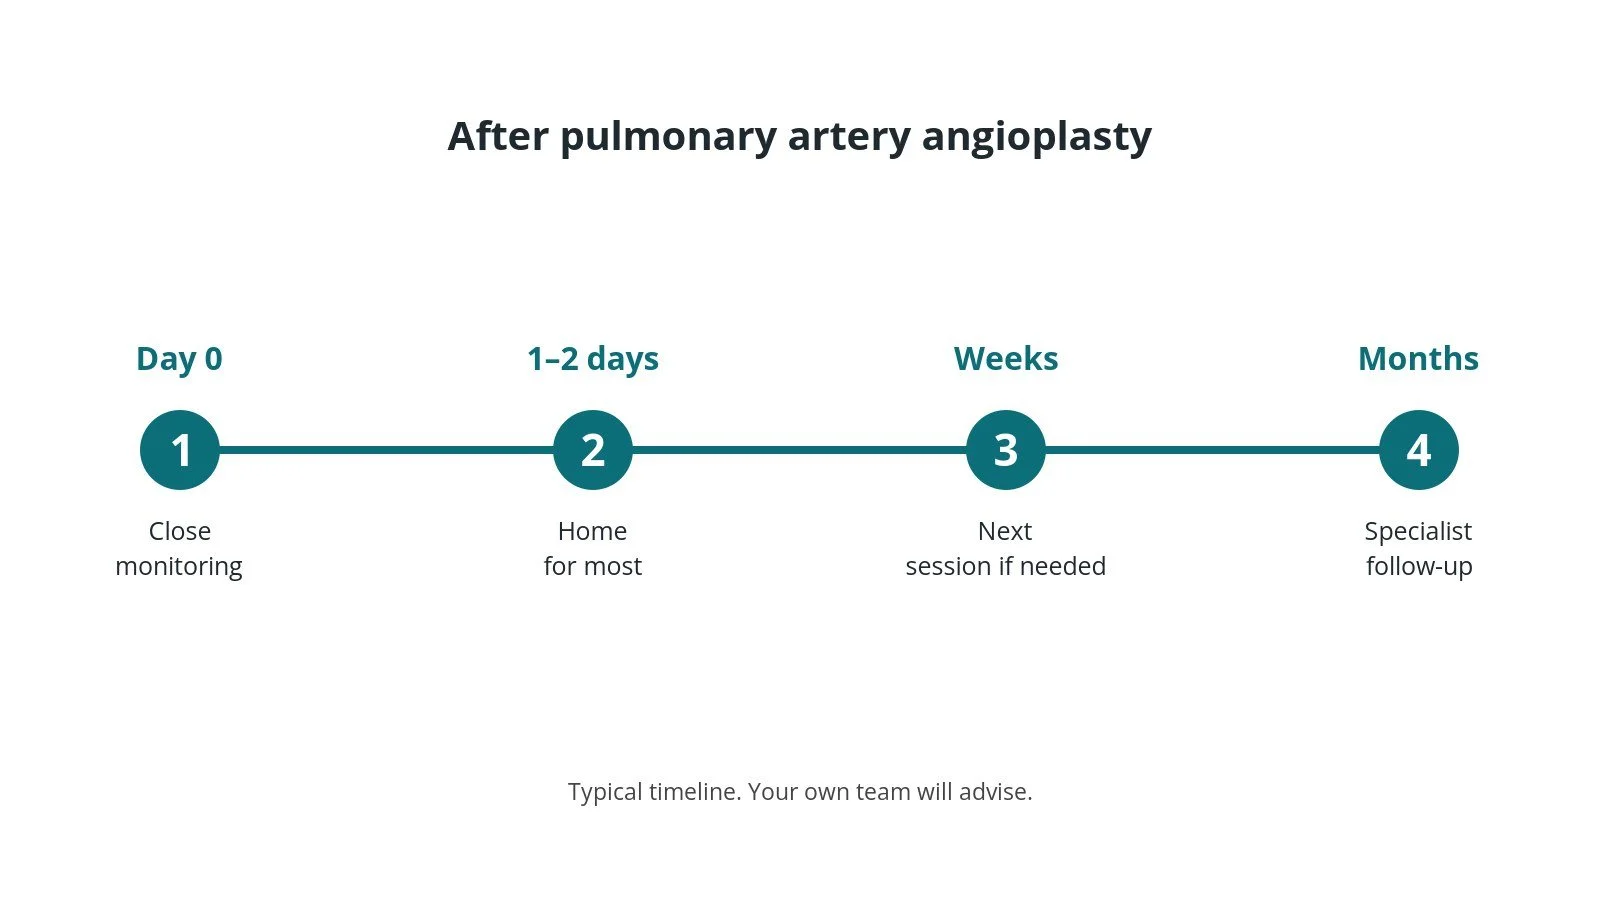
- First hours: checks of oxygen, breathing, rhythm and the access site.
- Hospital stay: often a night or more after BPA, as per centre protocol.
- Further sessions: CTEPH often needs several sessions weeks apart.
- Follow-up: with the pulmonary hypertension or congenital team.
Call 999 if you have chest pain, breathlessness, fainting, signs of a stroke, or heavy bleeding or swelling at the access site.
Risks and complications
Your team will explain the risks that apply to you. Possible problems include:
- injury to a lung artery, causing coughing up blood
- fluid in the treated lung area (reperfusion injury)
- heart rhythm problems
- bruising at the access site
- contrast reactions or kidney effects
- stent problems in congenital cases
Cath lab kit list (printable)
Barts example kit list
An example from one UK centre, written generically. Every lab has its own protocol, and sizes and doses vary.
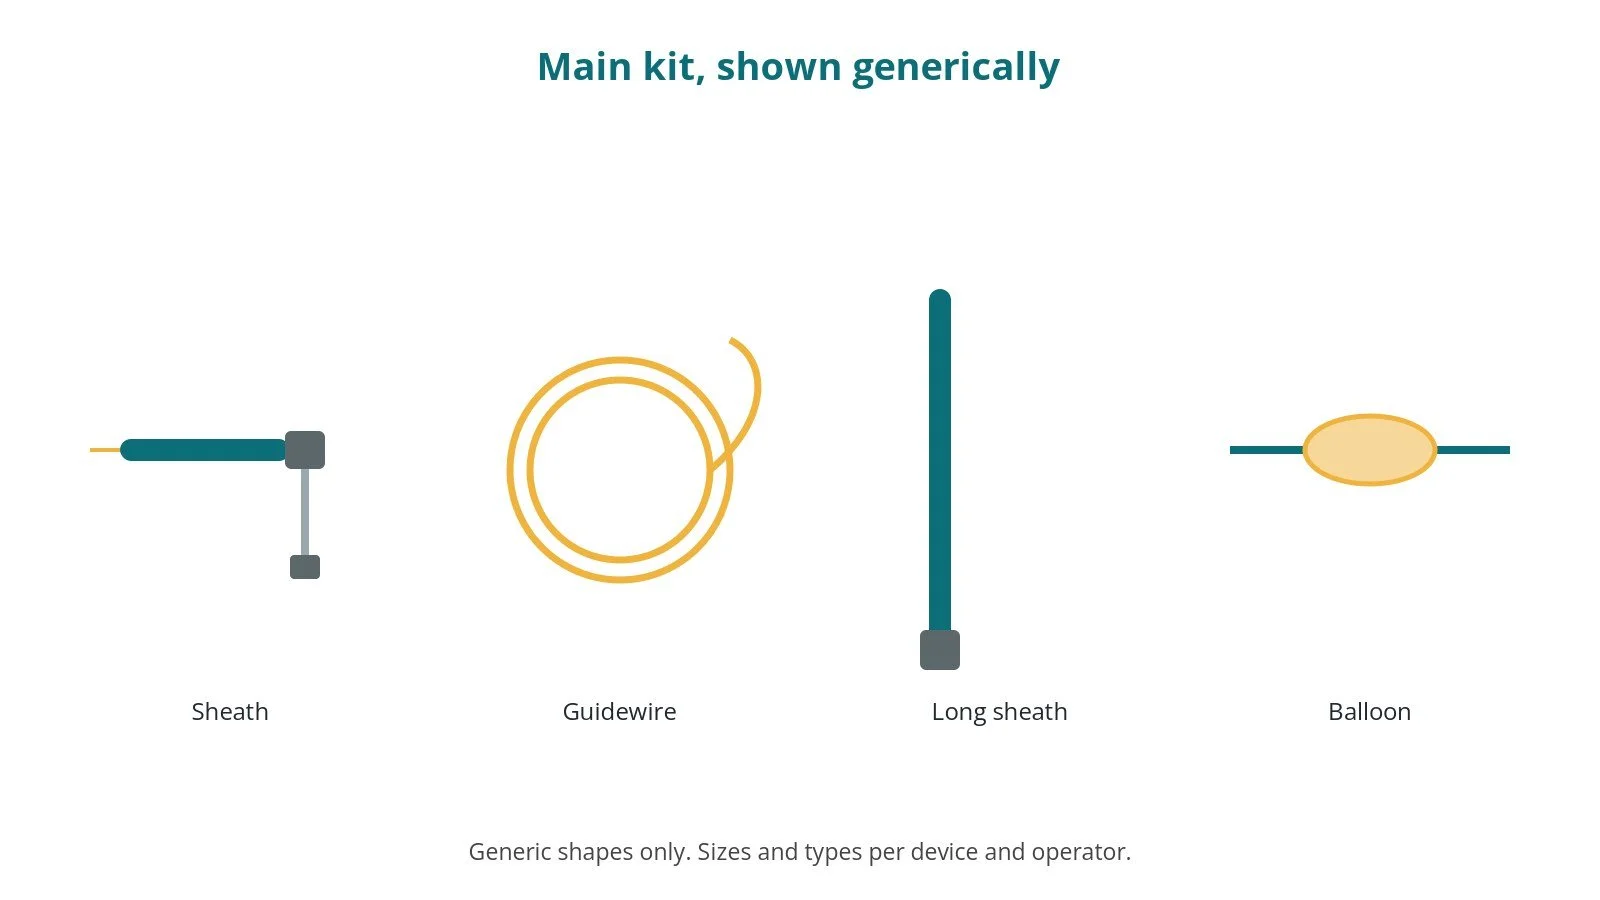
- venous sheath, size per device and operator
- long sheath or guide catheter, per operator
- guidewires, per operator
- balloons, sizes per device and operator
- stents for congenital cases, per device and operator
- pressure transducer
- heparin, as per centre protocol
Procedural steps (Barts example)
- Venous access; right heart pressures
- Pulmonary angiography
- Guide to the target vessel; wire across
- Balloon dilatation; check
- Stent if needed; final pressures
First time in the cath lab?
💡 First-time tip
- Watch oxygen. A drop may mean lung injury.
- Cough = tell. Report any coughing up of blood straight away.
- Pressures before and after. Record both.
- Multiple sessions. Track which vessels were treated.
FAQ
Is this the same as surgery for CTEPH?
No. It is an alternative for some people.
How many sessions?
It varies; your team will plan it.
Will I stay in hospital?
Often for at least a night.
Related Cath Lab 101 guides
- PPVI (percutaneous pulmonary valve implantation)
- TCPC (Fontan) ballooning and stenting
- Cath Lab Abbreviations A–Z
Sources
All checked on 10 October 2026. Each page's own date is shown where it gives one.
- Baumgartner H, et al. 2020 ESC Guidelines for the management of adult congenital heart disease. Eur Heart J 2021;42(6):563–645. PubMed 32860028
- StatPearls (NCBI Bookshelf), search: balloon pulmonary angioplasty. ncbi.nlm.nih.gov/books
Disclaimer
Education only. This page is for general education for healthcare students, cath lab staff and curious readers. It isn't medical advice and doesn't replace advice from your own doctor, heart team or local unit protocols. Equipment and medicines are described generically. No product or manufacturer is recommended. If you think someone is having a heart emergency, call 999.
Disclosure: I work for a company that makes a device used in this procedure. This page is independent education, isn't sponsored or reviewed by any company, and doesn't recommend any product.
All diagrams on this page are original illustrations created for rodnieoro.com.